Related Experiment Video
Updated: Sep 10, 2025
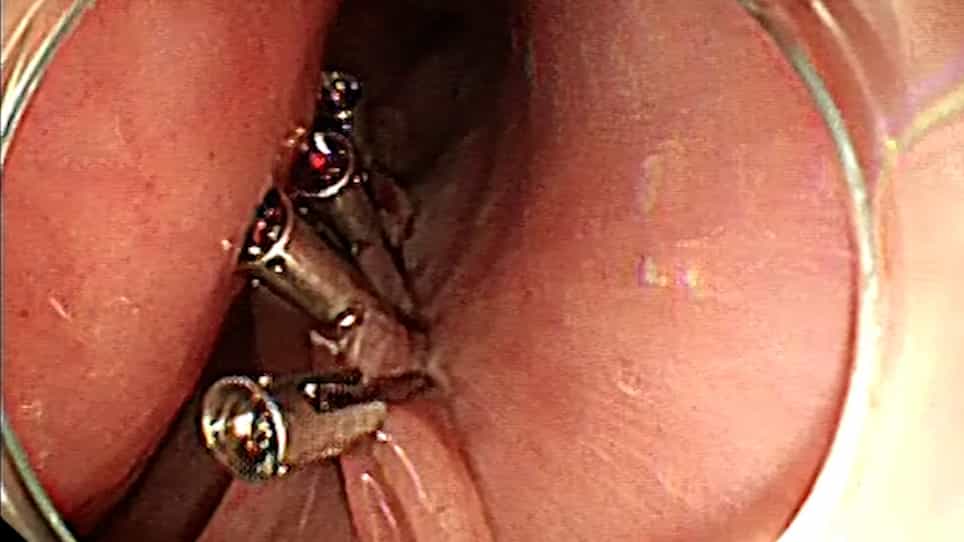

Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Clinical Characteristics and Influencing Factors of Postoperative Pain in Patients Undergoing Gastric Endoscopic
Fen Deng1, Liru Pan1, Lei Tao2
1Department of Gastroenterology First Medical Center of Chinese PLA General Hospital Beijing China.

Background:
To comprehensively analyze the clinical characteristics of patients who underwent gastric endoscopic submucosal dissection (ESD) and explore the incidence and influencing factors of postoperative pain.
Methods:
The clinical data of patients who underwent gastric ESD at our center from 2009 to 2024 were retrospectively analyzed. Pain severity was assessed using a visual analogue scale, with a score ≥ 4 defined as postoperative pain. Based on the presence or absence of postoperative pain, patients were divided into a pain group and a control group. Independent factors influencing postoperative pain were identified using multivariate logistic regression analysis. To control for confounding bias, patients in the case and control groups were matched by sex and lesion size, and the matched participants were further analyzed using a conditional logistic regression model.
Results:
In total, 993 patients were analyzed. The incidence of postoperative pain was 9.1% (95% confidence interval [CI], 7.3-11.1). In the univariate analysis, sex, operation duration, anesthesia method, intraoperative electrocoagulation, nasogastric tube placement, and postoperative vomiting were significantly associated with postoperative pain. Multivariate analysis identified eight independent factors: male sex (odds ratio [OR], 0.61; 95% CI, 0.37-0.97; p = 0.04), operation duration (OR, 1.29; 95% CI, 1.03-1.63; p = 0.02), protuberant lesions (OR, 0.43; 95% CI, 0.26-0.71; p < 0.01), antral lesions (OR, 1.84; 95% CI, 1.10-3.05; p = 0.01), intubation general anesthesia (OR, 0.40; 95% CI, 0.22-0.72; p = 0.002), intraoperative electrocoagulation (OR, 0.32; 95% CI, 0.19-0.55; p < 0.01), nasogastric tube placement (OR, 2.005; 95% CI, 1.12-3.57; p = 0.01), and postoperative vomiting (OR, 3.24; 95% CI, 1.40-7.47; p = 0.005). Conditional logistic regression analysis further identified diabetes mellitus (OR, 2.50; 95% CI, 1.03-6.06; p = 0.04).
Conclusion:
Female sex, diabetes mellitus, concave-type lesions, lesions in the gastric antrum, non-intubation general anesthesia, absence of intraoperative electrocoagulation, prolonged operation duration, nasogastric tube placement, and postoperative vomiting were independent factors associated with moderate to severe pain after gastric ESD. For patients at increased risk of postoperative pain, appropriate prophylactic and therapeutic measures during the perioperative period may effectively alleviate pain following gastric ESD.

Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management