Related Experiment Video
Updated: Sep 10, 2025


Cutoff Value of Phase Angle by Bioelectrical Impedance Analysis at Admission as a Prognostic Factor in Patients with Acute Heart Failure
Published on: June 10, 2025
Electrocardiogram abnormalities and cardiovascular risk prediction in older Chinese: the Guangzhou Biobank Cohort
Wen Bo Tian1, Wei Sen Zhang2, Chao Qiang Jiang2
1School of Public Health, Sun Yat-sen University, Guangzhou, Guangdong, China.

Insights
Multiple minor electrocardiogram abnormalities (EA) and major abnormalities increase cardiovascular disease (CVD) and mortality risk in older adults. However, an electrocardiogram abnormality score offers limited improvement for predicting CVD risk.
Area of Science:
- Cardiology
- Gerontology
- Public Health
Background:
- Limited evidence exists on the association between multiple minor electrocardiogram abnormalities (EA) and cardiovascular disease (CVD) risk in older populations.
- The predictive value of a weighted EA score compared to single EA severity for CVD risk is not well-established.
Purpose of the Study:
- To investigate the association of electrocardiogram abnormalities (EA) severity and a weighted EA score with incident cardiovascular disease (CVD) events and mortality in older Chinese adults.
- To assess the incremental predictive value of EA severity and score for CVD risk.
Main Methods:
- Analysis of 26,846 Chinese individuals aged 50+ from the Guangzhou Biobank Cohort Study (GBCS) without baseline CVD.
- Classification of minor and major EAs using the Minnesota Code Manual, defining EA severity (normal, one minor, two+ minor, major).
- Development of an EA score using Cox regression with backward stepwise selection; examination of associations with CVD events, all-cause, and CVD mortality using Cox regression; assessment of predictive improvement using C-index and Net Reclassification Index (NRI).
Main Results:
- During 15.3 years of follow-up, higher EA severity (one minor, two+ minor, major) was associated with increased risk of incident CVD events (adjusted HRs 1.12-1.46).
- A significant dose-response relationship was observed for the EA score, with higher scores indicating substantially increased risk for CVD events and mortality (e.g., ≥60 points: HR 3.16).
- Adding the EA score improved CVD risk prediction (C-index change 0.011 at 3 years, NRI 0.016 for 10-year risk), but the improvement was limited and diminished over time.
Conclusions:
- Major EA and multiple minor EAs are linked to elevated risks of CVD events and mortality in older adults.
- While an EA score demonstrates a dose-response relationship and shows some improvement in risk prediction, its overall utility in enhancing CVD risk prediction is limited.
Background:
Evidence on the associations of multiple minor ECG abnormalities (EA) with cardiovascular disease (CVD) and mortality in older populations is limited, particularly whether a weighted EA score better predicts CVD risk than a single EA severity.
Methods:
We analysed 26 846 Chinese aged 50+ years from Guangzhou Biobank Cohort Study (GBCS), without CVD at baseline. Minor and major EAs were classified based on the Minnesota Code Manual. EA severity was defined as normal, one minor, two or more minor and major abnormalities. Cox regression with backward stepwise selection was conducted to develop EA score. Cox regression was used to examine the associations of EA (severity/score) with incident CVD events, all-cause mortality and CVD mortality. C-index and Net Reclassification Index (NRI) were used to assess the improvement in CVD risk prediction after adding EA (severity/score) to the GBCS model variables.
Results:
During an average follow-up of 15.3 (SD=3.5) years, 6232 CVD events and 5960 deaths occurred. Compared with normal ECG, one minor (adjusted HR 1.12, 95% CI 1.05 to 1.19), two or more minor (1.20, 95% CI 1.11 to 1.29) and major abnormalities (1.46, 95% CI 1.31 to 1.63) were associated with a higher risk of incident CVD events. The EA score showed a strong dose-response relationship (0 point as reference): 1-29 points (1.12, 95% CI 1.05 to 1.19), 30-59 points (1.56, 95% CI 1.38 to 1.77), ≥60 points (3.16, 95% CI 2.56 to 3.91) (p value for trend <0.001). Similar findings were observed for all-cause and CVD mortality. Adding EA score improved the C-index for incident CVD events, but the improvement diminished over time (change in C-index: 0.011 (95% CI 0.002 to 0.022) at 3 years to 0.003 (95% CI 0.002 to 0.004) at 15 years). The NRI for 10-year risk was 0.016 (95% CI 0.007 to 0.024), indicating limited utility.
Conclusions:
Major EA and multiple minor EAs were associated with higher risks of CVD events and mortality, but the value in improving CVD risk prediction is limited.

Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:28
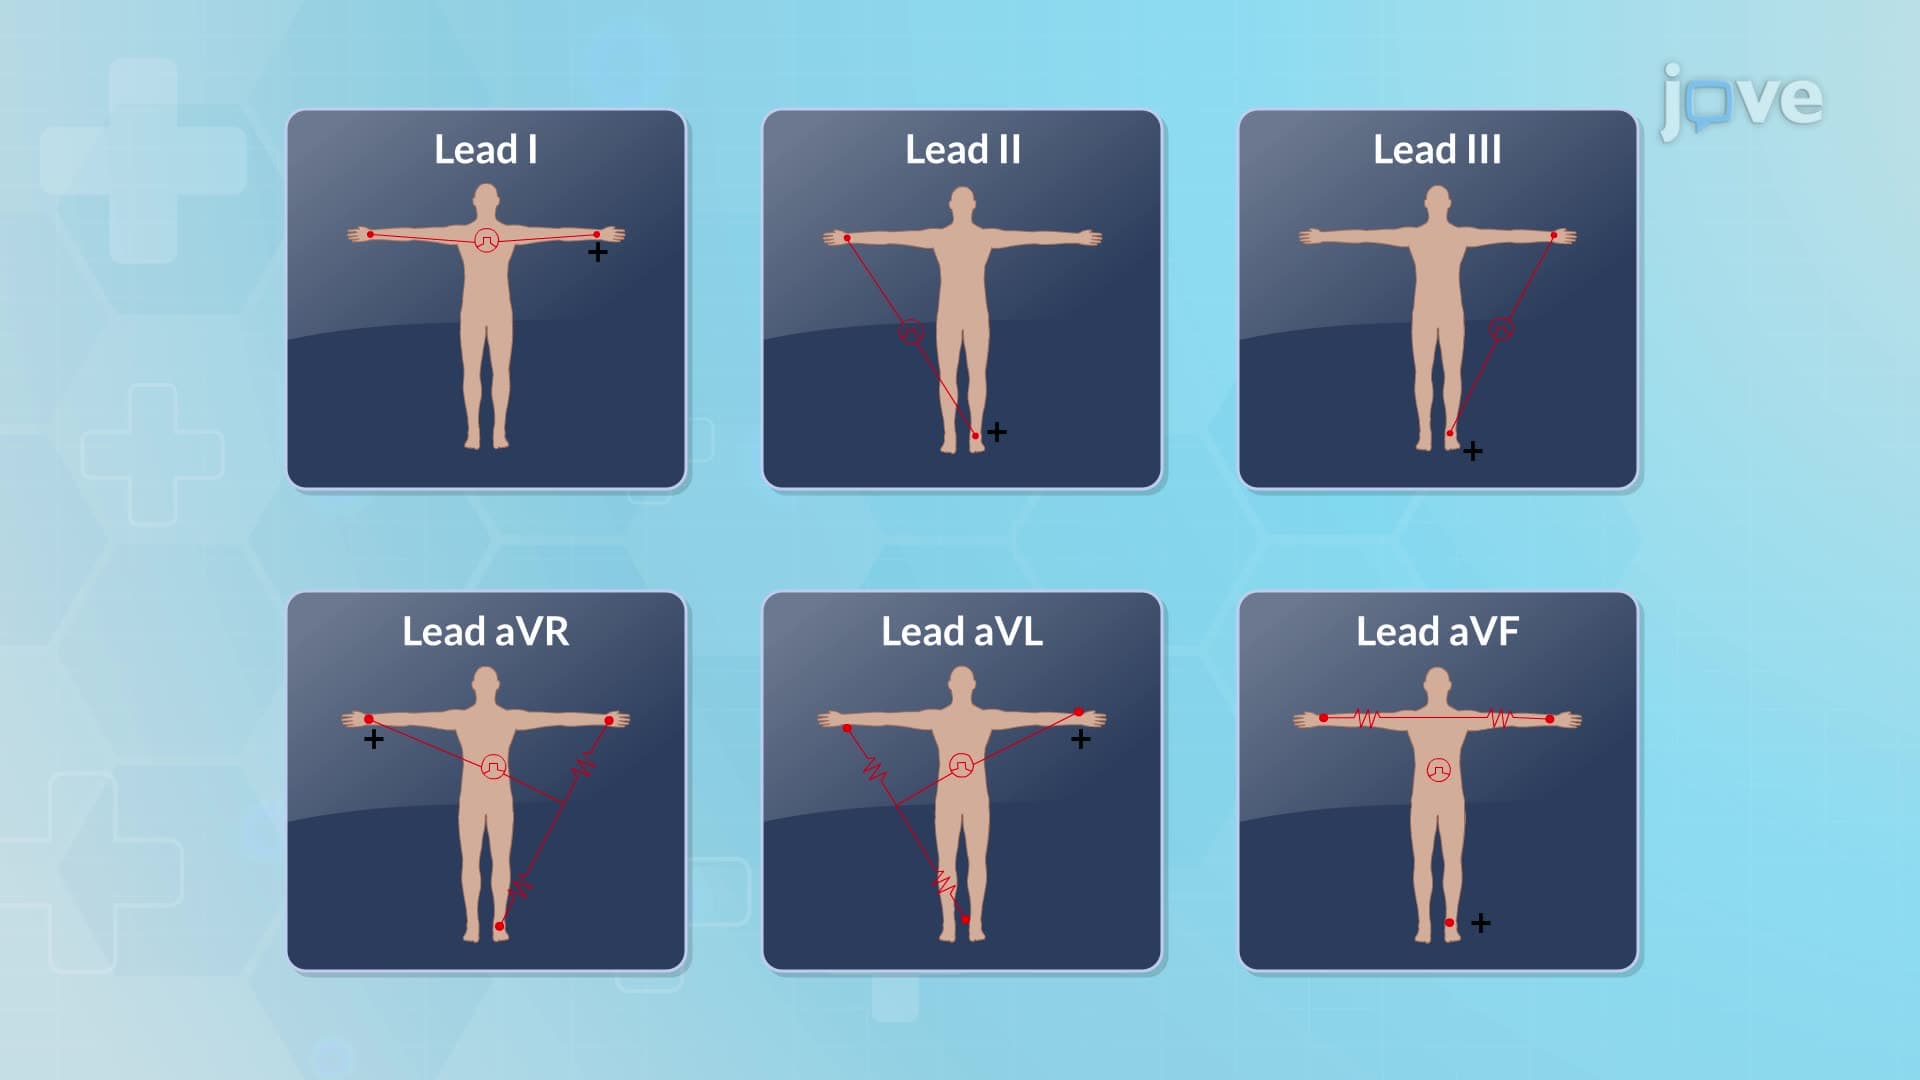
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:26
Coronary Artery Disease IV: Preventive Measures