Related Experiment Video
Updated: Sep 9, 2025
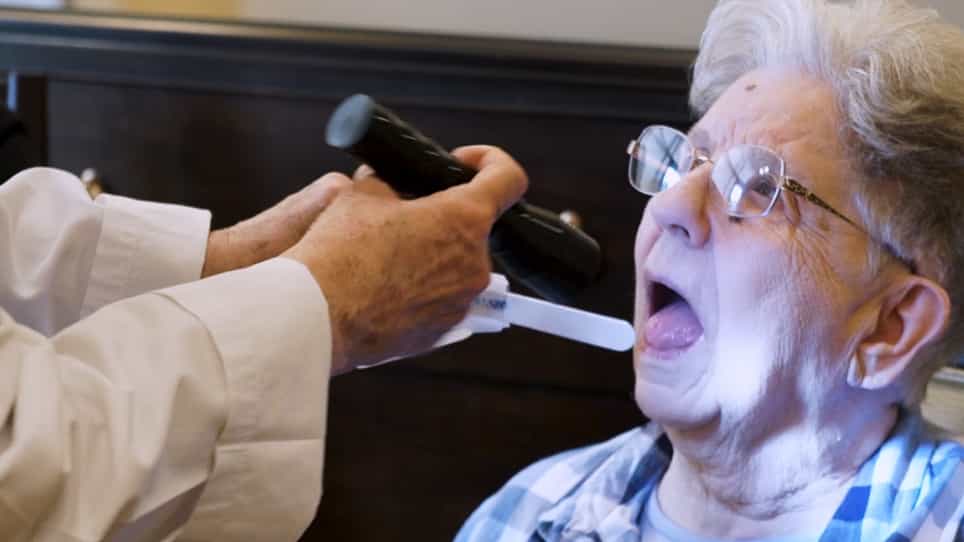

Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Provider and Organizational Factors Impacting Routine Cancer Screening Among Older Medicaid Enrollees
Adriana Corredor-Waldron1, Ann M Nguyen2, Jose Nova2
1Department of Economics, North Carolina State University, Raleigh, North Carolina, USA.

Objective:
To analyze the conditional association between provider and organizational factors and routine cancer screening for older Medicaid enrollees before and during the COVID-19 pandemic.
Study Setting And Design:
This study analyzed pre-pandemic (2018/2019; n = 110,882) and pandemic (2020/2021; n = 107,451) cohorts of New Jersey (NJ) Medicaid enrollees aged 50-75. Using linear probability models, we evaluated how provider and organizational characteristics, including interactions with pandemic years, influenced screening for breast, cervical, colorectal, and lung cancers. Models controlled for enrollees' demographic and clinical characteristics and geographic factors.
Data Sources And Analytic Sample:
Claims data from the 2016-2021 NJ Medicaid Management Information System were linked to Medicare Provider and Specialty files. The sample included Medicaid enrollees with an assigned primary care provider and no prior cancer diagnosis.
Principal Findings:
Higher patient panel sizes were consistently associated with increased screening for breast (20.4%, 95% confidence interval (CI): 13.9%-26.8%), cervical (24.1%, 95% CI: 16.6%-31.5%), and lung cancer (63.1%; 95% CI: 17.4%-108.6%) during the pandemic. Obstetrician-gynecologist providers were linked to higher screening rates for breast (50.6%, 95% CI: 41.6%-59.5%) and cervical cancers (70.5%, 95% CI: 52.3%-88.9%), even during the pandemic. Female providers improved screening rates for breast (7.6%, 95% CI: 2.8%-12.3%), cervical (3.8%, 95% CI: 0.10%-7.5%), and colorectal cancer (5.8%, 95% CI: -2.7%-14.4%) among female enrollees. Provider age was unrelated to breast, cervical, or colorectal screening; however, in 2021, lung cancer screening was 23% lower for patients of clinicians aged 62 and above.
Conclusions:
Large group practices effectively maintained breast and cervical cancer screening during the pandemic while exhibiting mixed results for colorectal and lung cancers. Provider characteristics such as gender and specialty also significantly impacted screening rates. Supporting large practices and addressing barriers in smaller practices are key to improving cancer prevention, especially during crises.


Related Concept Videos
 01:30
Preventive Healthcare Services
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:27
Nursing Ethical Principles II
Consider the following scenario, which illustrates how these principles are applied in the care of Mr. John, a fifty-year-old teacher diagnosed with metastatic liver cancer.
Initially, Mr. John's...
 01:22
Standards of Care I
 01:18
Introduction To Health Care Delivery System
The Institute of Medicine (IOM) advocates for a patient-centered, effective, safe, timely, equitable, and effective healthcare system. The National Priorities...
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...