Related Experiment Video
Updated: Sep 9, 2025

Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Impact of Transcatheter Aortic Valve Replacement Volume on Outcomes in Patients With End-Stage Renal Disease
Esteban Aguayo1, Oh Jin Kwon1, Mitchell Won1
1Cardiovascular Outcomes Research Laboratories (CORELAB), David Geffen School of Medicine, University of California, Los Angeles, Los Angeles, California.

Background:
Patients with end-stage renal disease (ESRD) are at increased risk for calcific aortic stenosis. Given limited data on the efficacy of transcatheter aortic valve replacement (TAVR) in this population, the present study examined acute mortality, complications, and 30-day nonelective readmissions in a national cohort of patients with ESRD.
Methods:
The 2016 to 2021 National Readmissions Database was queried to identify all TAVR admissions (in patients aged ≥18 years). Patients were stratified into ESRD and non-ESRD cohorts. Primary outcomes included in-hospital mortality and 30-day readmissions, whereas perioperative complications, length of stay, and hospitalization costs were secondarily assessed. Multivariable logistic regression and Nelson-Aalen cumulative hazard analysis were used to evaluate factors associated with mortality and readmissions, stratified by institutional TAVR volume. Low-volume and high-volume hospitals were defined by quartiles of annual procedural volume.
Results:
Among 411,311 patients undergoing TAVR, 7.3% had ESRD. After risk adjustment, ESRD remained associated with higher mortality (adjusted odds ratio, 1.79; 95% CI, 1.59-2.00) and readmissions (adjusted odds ratio, 1.87; 95% CI, 1.78-1.96). Additionally, ESRD was linked to increased length of stay (β, +1.3 days; 95% CI, 1.1-1.5) and costs (β, +$1.0K; 95% CI, 0.5K-1.5K). After accounting for TAVR volume, non-ESRD was associated with a lower risk of mortality and readmission at high-volume hospitals compared with low-volume hospitals, whereas ESRD was associated with similar risks regardless of institutional volume.
Conclusions:
Patients with ESRD are at increased risk for postoperative mortality, hospital resource use, and readmissions. This association was not mitigated at high-TAVR volume centers. Given the increased risk of mortality and readmission, careful patient selection and optimization are crucial for patients with ESRD who are undergoing TAVR.


Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:25
Aortic Regurgitation III: Medical Management
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:06
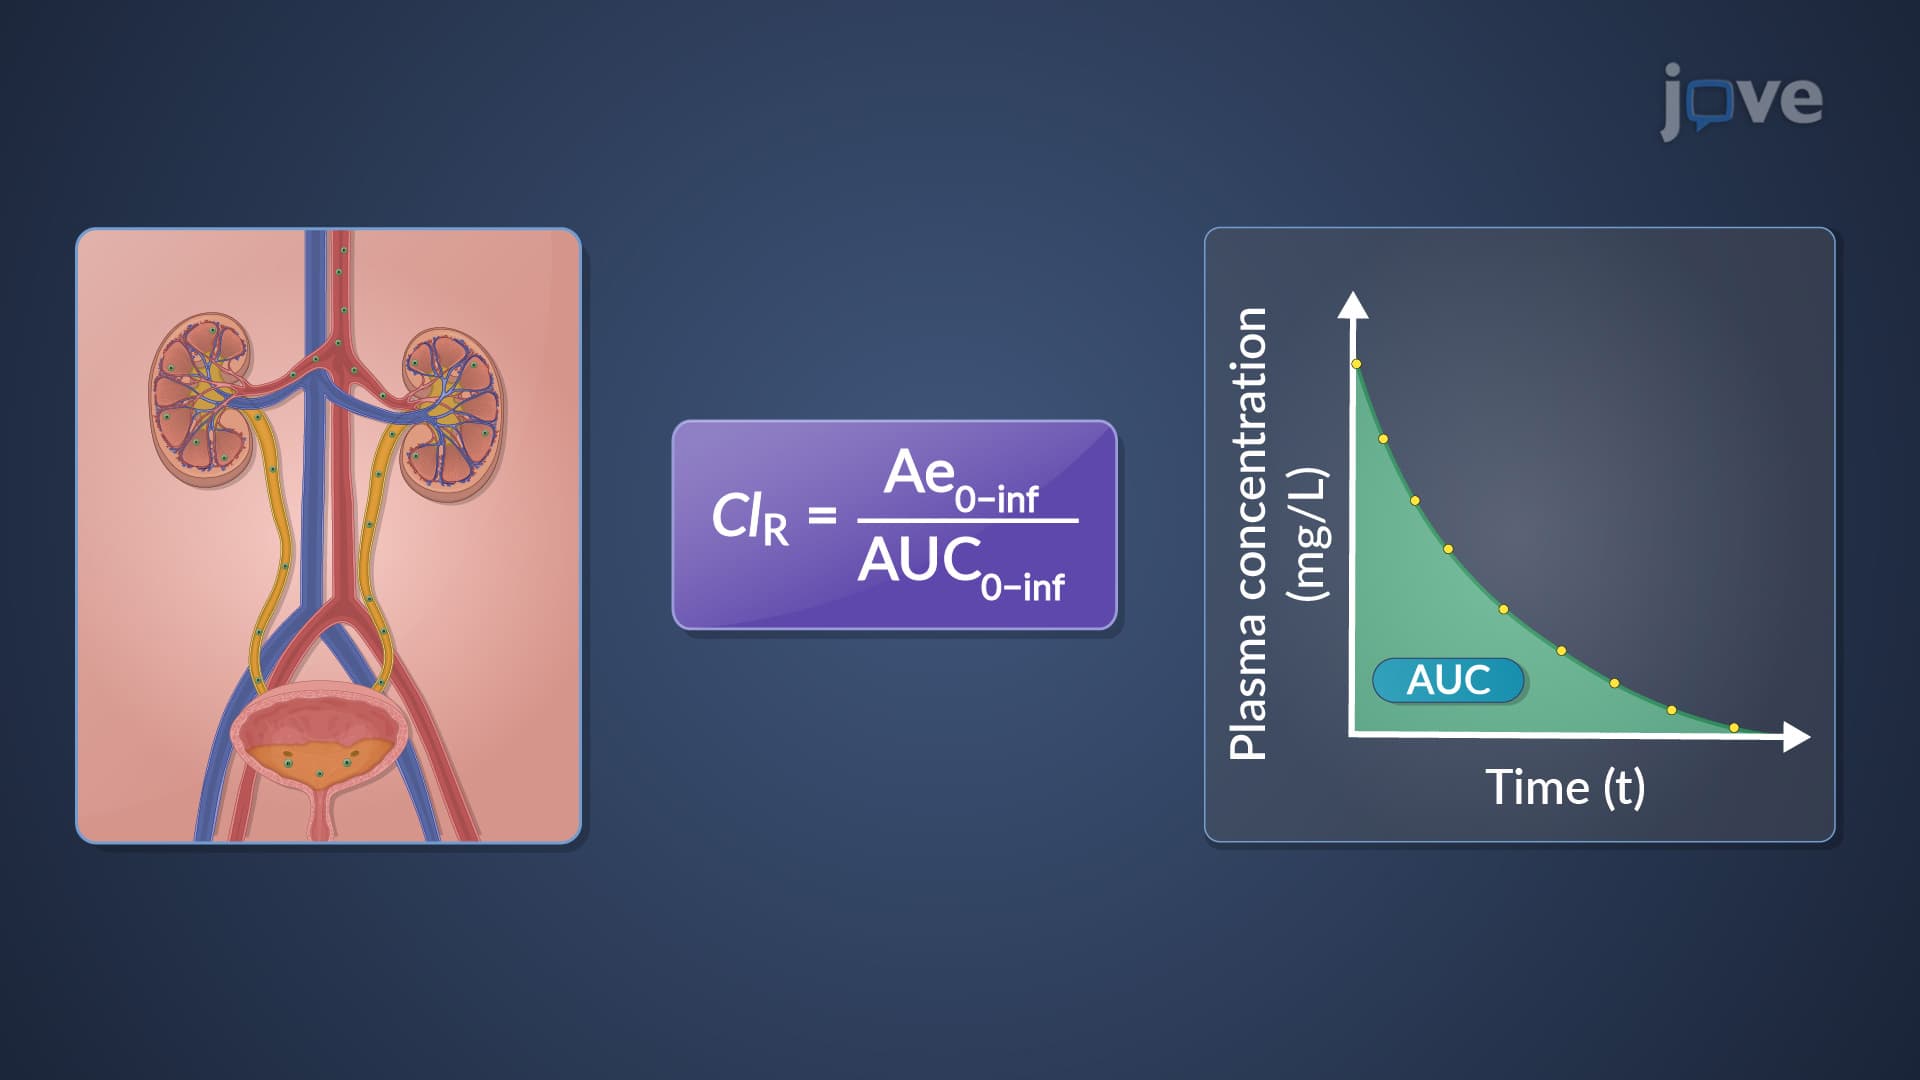
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention