Related Experiment Video
Updated: Sep 9, 2025
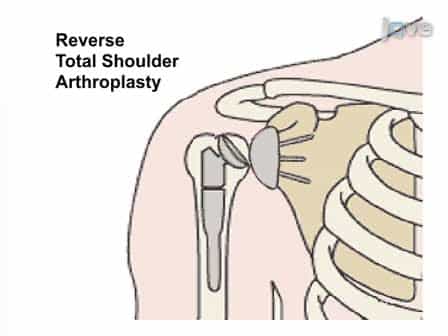
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Disruptive Bleeding and Comorbidity Burden in Total Knee Arthroplasty: Associations With Costs, Lengths of Stay, and
Mitchell K Ng1, Michael A Mont2, Mosadoluwa Afolabi3
1Department of Orthopaedic Surgery, Rothman Orthopaedic Institute, Thomas Jefferson University Hospital, Philadelphia, Pennsylvania.

Background:
Total knee arthroplasty (TKA) is a widely performed procedure for end-stage knee osteoarthritis, with over 1.2 million annual cases projected by 2025. While generally successful, TKA can lead to perioperative complications, including disruptive bleeding or hemorrhagic events requiring medical intervention. This study aimed to (1) quantify the incidence of disruptive bleeding; (2) identify patient demographics and the Elixhauser comorbidity burden associated with disruptive bleeding; and (3) quantify the effects of disruptive bleeding on health care utilization (length of stay, 90-day readmission rates, and costs).
Methods:
This was a cohort study analyzing adult patients undergoing primary TKA in 2019 using a large national health care database. After identifying baseline patient demographics, the Elixhauser comorbidity index (ECI) was categorized from 0 to ≥ 6 and analyzed for association with disruptive bleeding using multivariable logistic regressions. Odds ratios (ORs) and 95% confidence intervals (CIs) were calculated to assess bleeding risk by ECI category. Generalized linear models evaluated the impact of disruptive bleeding on hospital stays, costs, and readmissions, adjusting for demographics.
Results:
Among 175,384 TKA patients, 8,991 (5.1%) experienced disruptive bleeding. African American race and Medicare insurance status were associated with increased disruptive bleeding (P < 0.05), while age and sex were not. The odds of disruptive bleeding increased with comorbidity burden, from OR = 1.20 (95% CI 1.06 to 1.36) for ECI = 1 to OR = 2.39 (95% CI 1.82 to 3.12) for ECI ≥ 6. Disruptive bleeding was associated with longer hospital stays (mean increase: 2.4 days, P < 0.001), higher costs ($18,700 versus $17,600, P < 0.001), and greater 90-day readmission risks (7.4 versus 5.3%, P < 0.001).
Conclusions:
Disruptive bleeding in TKA is associated with a higher comorbidity burden, leading to prolonged hospitalizations, increased costs, and greater readmission risks. Improved risk stratification and perioperative management strategies are needed to reduce complications and optimize patient outcomes.


Related Concept Videos
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care