Related Experiment Video
Updated: Jun 20, 2026


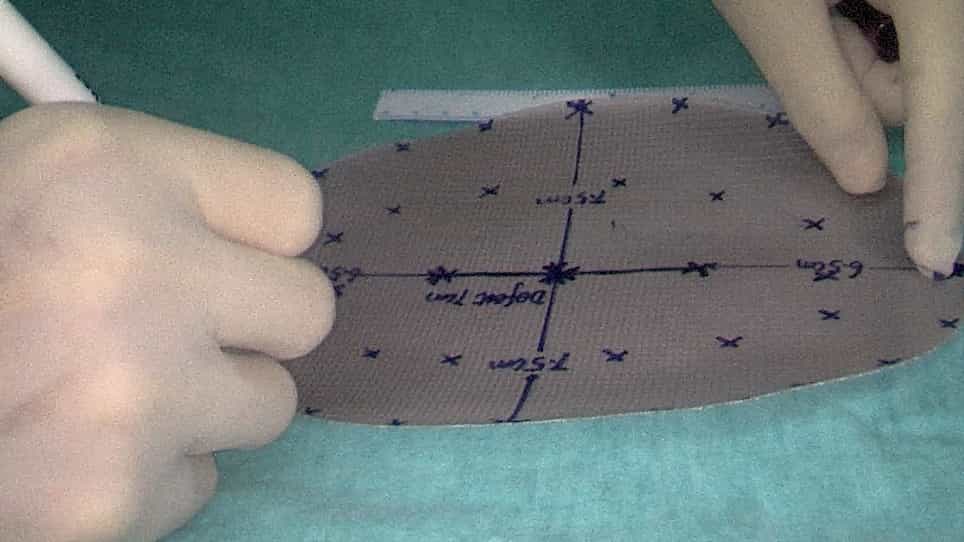
Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Recurrence rate and mesh bulging are reduced with primary fascial closure in ventral hernia repair: the PROSECO
Mikael Lindmark1,2, Jael Tall3,4, Bahman Darkahi5
1Department of Diagnostic and Intervention, Umeå University, Umeå, Sweden.

Background:
Laparoscopic intraperitoneal onlay mesh repair using a bridging technique has shown high rates of hernia site complications. Primary fascial closure before mesh placement has been utilized to address this. This randomized, parallel, double-blind, multicentre controlled trial investigated whether primary fascial closure reduces hernia site complications.
Methods:
Adults undergoing laparoscopic intraperitoneal onlay mesh repair for a midline hernia were randomized to primary fascial closure or bridging. Clinical assessment and the Ventral Hernia Pain Questionnaire were completed preoperatively and at 3 and 12 months post-surgery. CT scans were performed pre- and 12 months post-surgery. It was hypothesized that non-resorbable suture closure would reduce complication rates from 30% to 13% at 12 months, requiring 180 patients for 80% power and 95% significance.
Results:
One hundred and ninety-two patients were randomized (97 closure, 95 bridging), with 173 (90%) completing 1-year follow-up. At 12 months, overall hernia site complication rates showed no significant difference clinically (18% versus 20%, P = 0.85) or on CT (25% versus 28%, P = 0.50). However, recurrence and mesh bulging were significantly lower with fascial closure (4% versus 20%, P = 0.006). This group also reported significantly less pain at 12 months.
Conclusion:
Although there was no difference in the primary endpoint, fascial closure resulted in significantly lower rates of recurrence and mesh bulging, along with reduced postoperative pain. These findings suggest that primary fascial closure should be recommended alongside intraperitoneal onlay mesh repair in midline hernias.
Trial Registration:
The trial was registered at the ISRCTN at the start of the trial (ISRCTN51495042).
More Related Videos

Related Concept Videos
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications