Related Experiment Video
Updated: May 2, 2026

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Understanding late-onset neurological deficit in severe rigid Scoliosis: A comprehensive review
Siddharth S Sethy1, Nikhil Goyal2, Aakash Jain3
1Spine Surgery, Department of Orthopaedics, Kalinga Institute of Medical Sciences, Bhubaneswar, India.

Abstract:
A neurological deficit (ND) is one of the dreaded complications of spinal deformity. While most are associated with the corrective procedure itself, neurological deficits can also be present preoperatively. Postoperatively, these deficits can manifest either immediately as a perioperative new-onset neuro deficit (PNND) or emerge later as a delayed-onset postoperative neuro deficit (DPND). DPND remains one of the most severe and poorly understood complications following scoliosis surgery. In the setting of severe rigid scoliosis (SRS), DPND is an even rarer occurrence. Despite its clinical significance, the underlying pathophysiological mechanisms contributing to the development of DPND remain poorly understood. Their clinical manifestation may vary from mild sensory weakness to profound paraplegia. In most instances, DPND usually manifests at the site of deformity after correction. However, in some cases, the site of injury may be marked at a cranial level, leading to quadriparesis or quadriplegia. The pathophysiology of ND development depends on a complex interplay between mechanical, vascular, and iatrogenic factors that vary with the time of occurrence. The pathophysiology of DPND is multifactorial, stemming from a combination of direct mechanical oppression, vascular insufficiency, and iatrogenic injury, all of which are exacerbated in the presence of a pre-compromised or "sick" spinal cord. It is also noteworthy that, even in the absence of conventional developmental intraspinal anomalies, the tethering effect can persist. Somatosensory evoked potential (SSEP) evaluation can help in detecting tethering by establishing a conduction block or conduction delay. Effective management hinges on utilizing advanced risk stratification tools such as the deformity angular ratio (DAR)/deformity angular distance ratio (DADR) and MRI-based spinal cord shape classifications (SCSCS). Preoperative traction and gradual correction techniques are essential to a risk-reduction strategy. In the presence of preexisting neurological dysfunction with a sick cord requires circumferential decompression, and shortening procedures are beneficial to distress the cord with increased available space and avoiding further insult. While IONM is an indispensable safeguard, it does not eliminate the risk of delayed neurological deficits. A proactive approach, including hemodynamic optimization and a high index of suspicion in the postoperative period, is paramount. When deficits occur, prompt investigation to diagnose the offending pathology and early introduction of steroid protocol are critical to maximizing the potential for neurological recovery. An immediate post-operative CT scan can rule out any screw malposition that compresses the cord or nerve roots. An MRI scan of the area can reveal signal intensity changes within the cord levels consistent with ischemic changes. An early targeted decompression can thereby improve the likelihood of a favorable neurological outcome.
More Related Videos
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
Related Concept Videos
 01:14
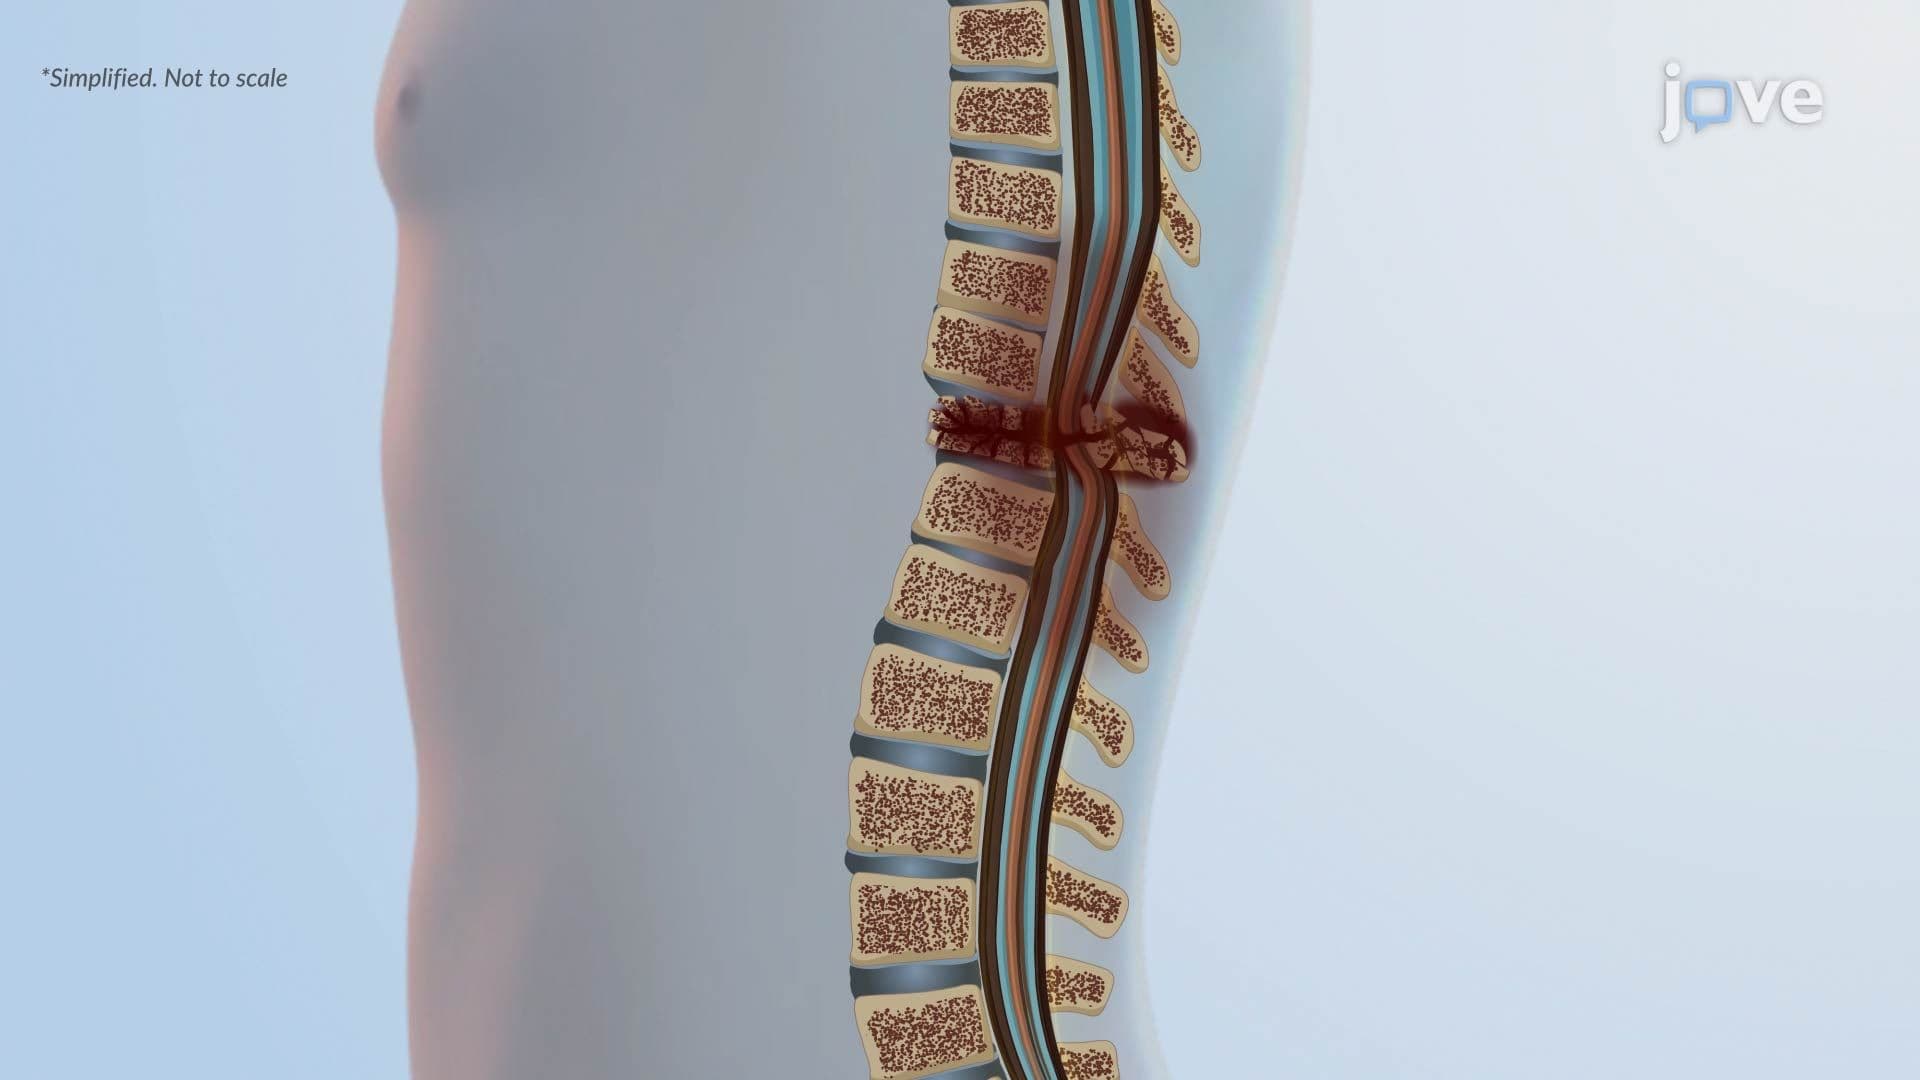
Spinal Cord Injury ll: Pathophysiology
 01:29
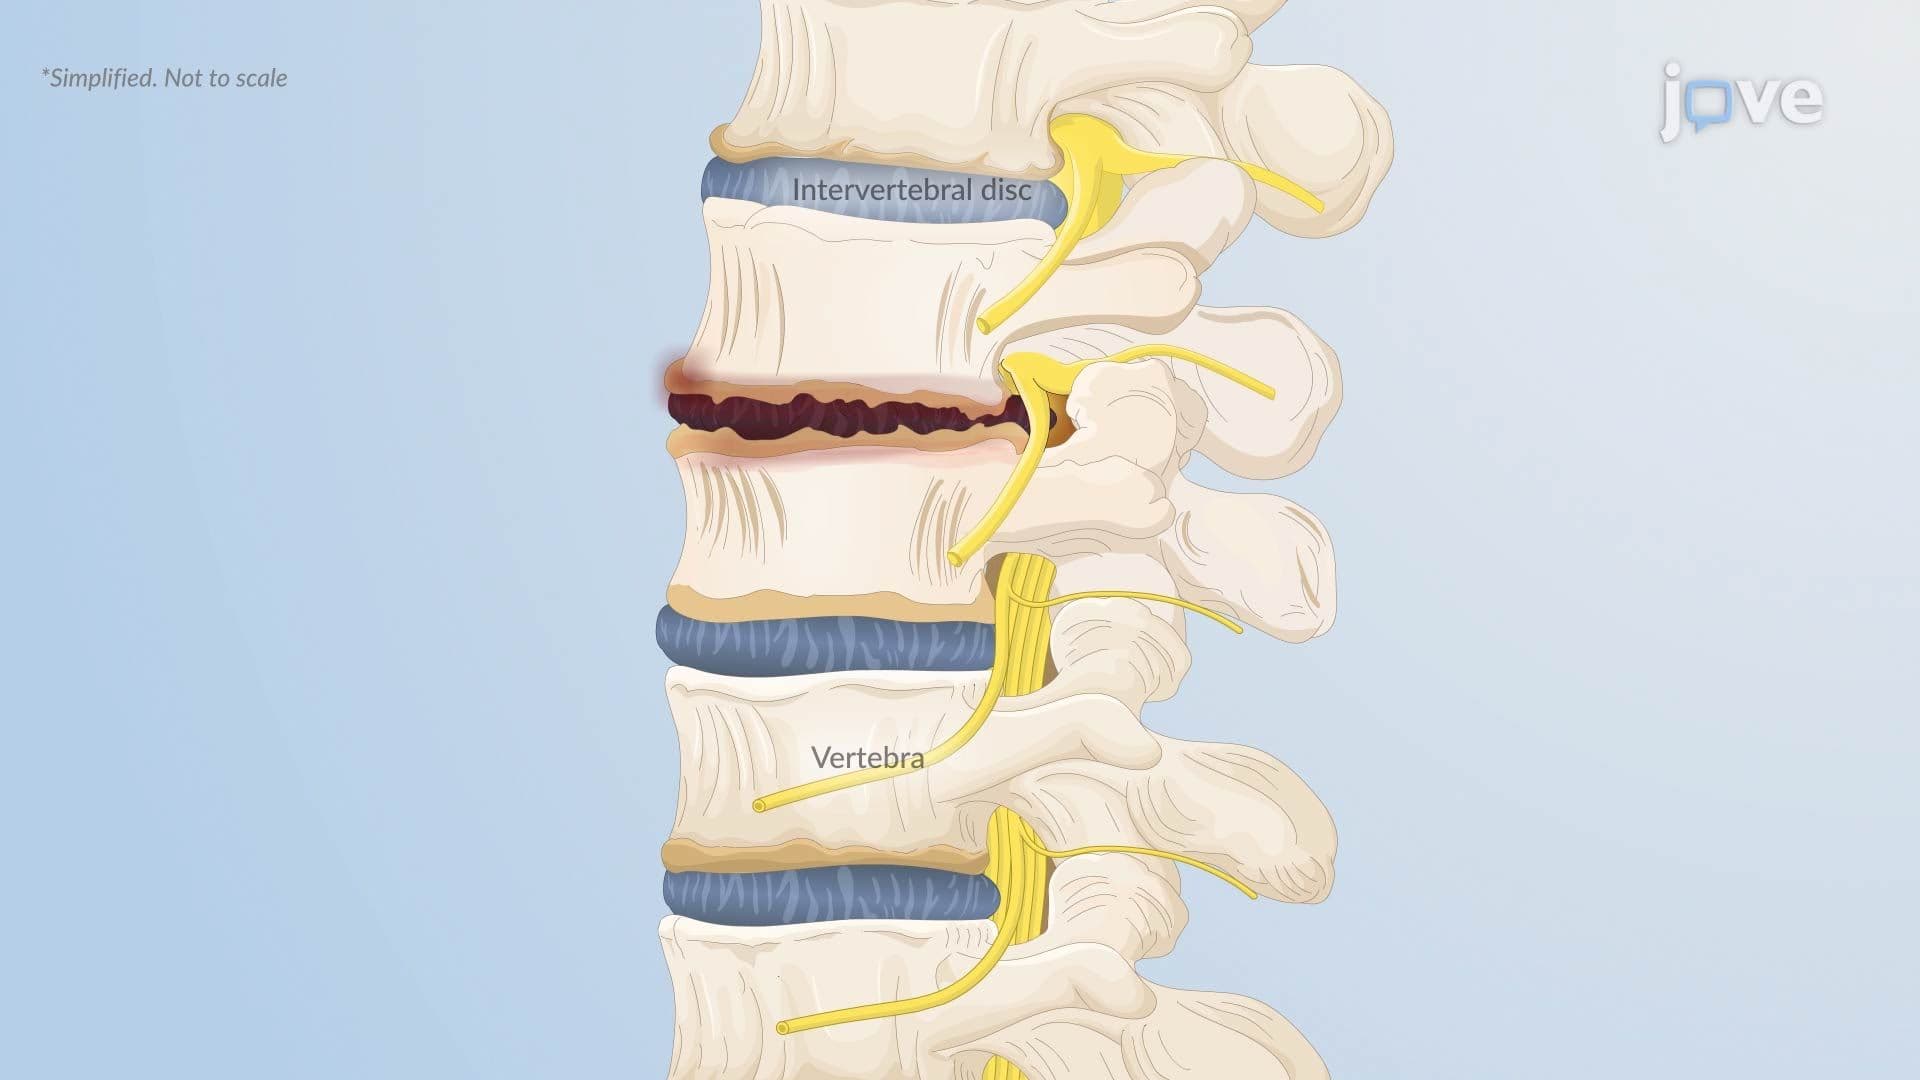
Herniated Intervertebral Disc l: Introduction
 01:27
Degenerative Disc Disease I: Introduction
 01:23
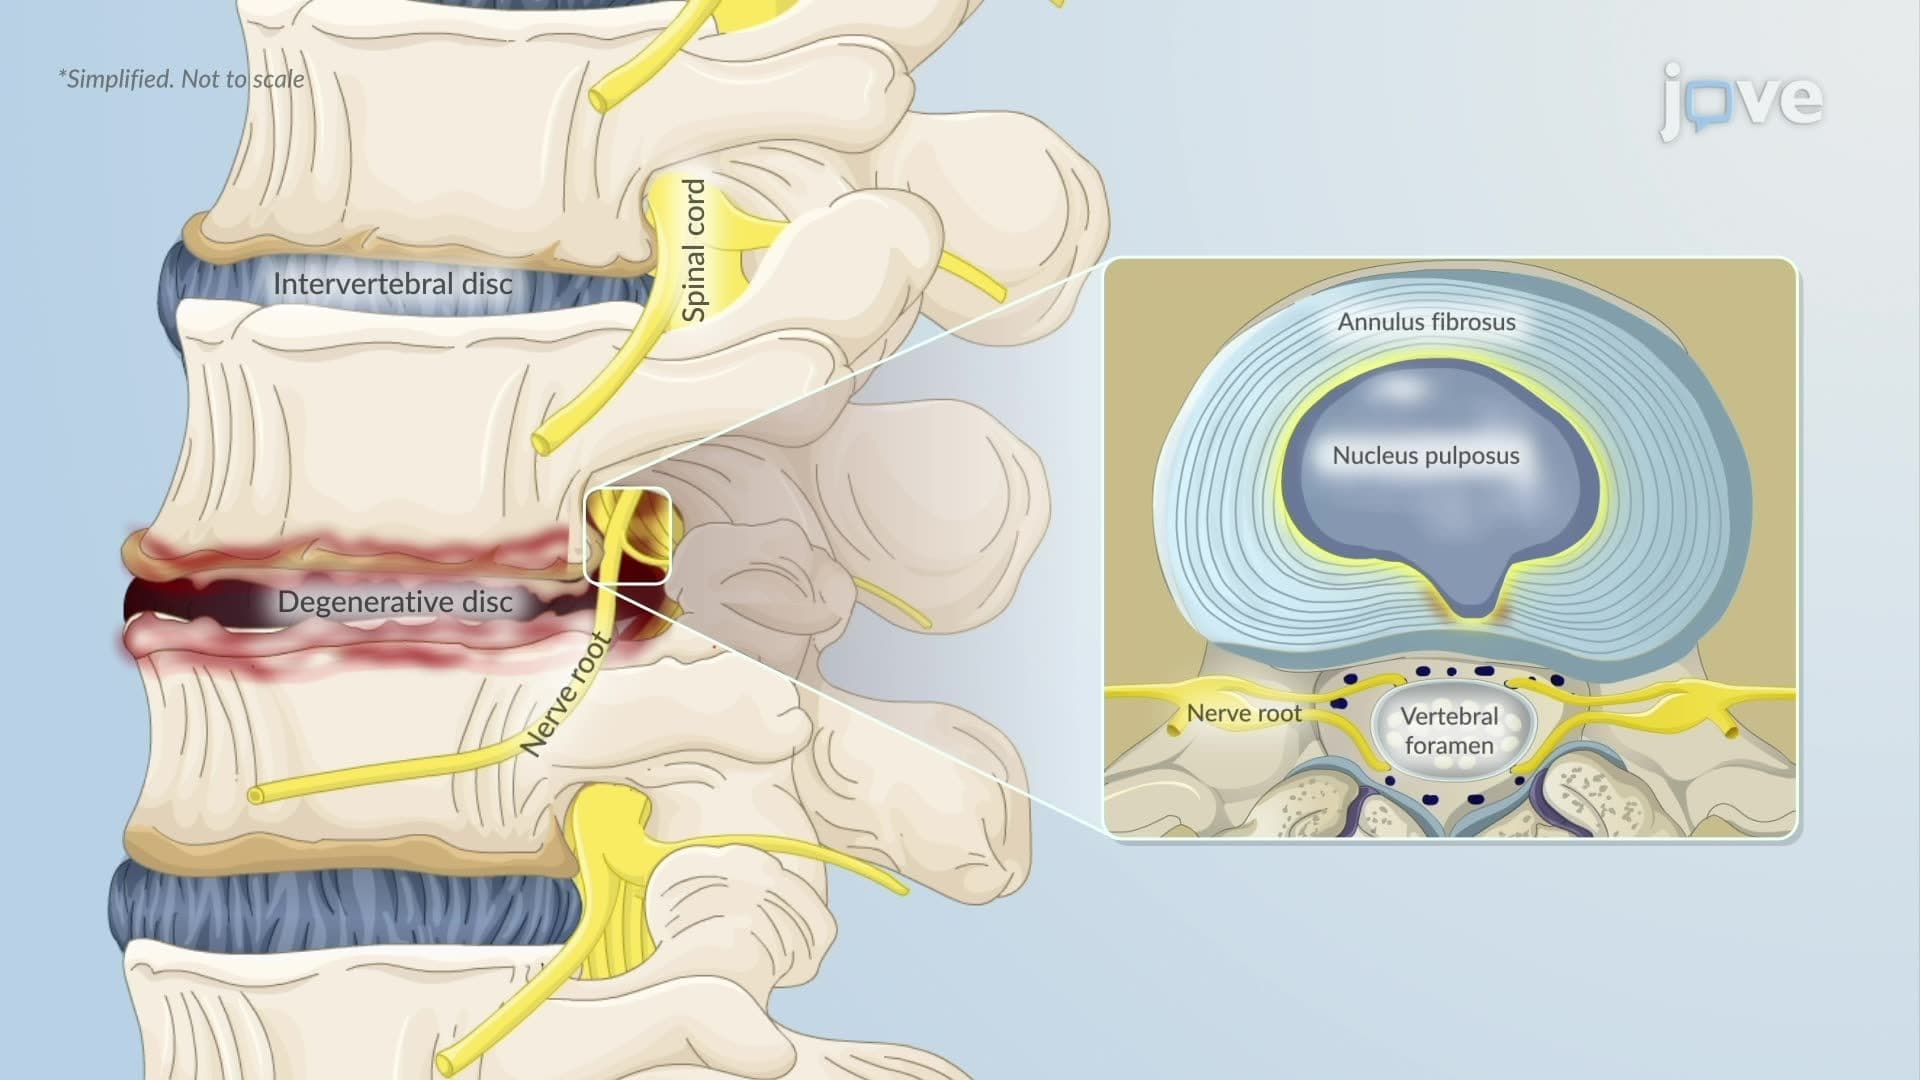
Degenerative Disc Disease ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology