Related Experiment Video
Updated: May 6, 2026

Surgical Retrieval, Isolation and In vitro Expansion of Human Anterior Cruciate Ligament-derived Cells for Tissue Engineering Applications
Published on: April 30, 2014
Medial Patellofemoral Ligament Reconstruction Using the Anterior Half of the Peroneus Longus Tendon Graft
Bruno Butturi Varone1, André Giardino Moreira da Silva1, Fernando Loureiro Miranda1
1Hospital das Clínicas da Faculdade de Medicina da USP, São Paulo-SP, Brazil.

Background:
Medial patellofemoral ligament (MPFL) reconstruction is the main procedure performed for recurrent patellar instability. Choosing wisely between graft options is particularly important in this specific population, who often lacks neuromuscular control. The gracilis, semitendinosus, and quadriceps tendons are the most frequently used autografts, but harvesting can lead to reduced thigh muscle strength and poorer balance control. Studies have demonstrated safety and efficacy in harvesting only the anterior half of the peroneus longus tendon (AHPLT), with low morbidity and satisfactory functional outcomes. The AHPLT can be a convenient option for MPFL reconstruction, as it provides a solid graft without compromising muscle balance around the knee and maintains the biomechanical functions of the tendon in the foot and ankle. The objective of this article is to describe the step-by-step technique of MPFL reconstruction using the AHPLT graft.
Indications:
Suitable indications for AHPLT harvesting are patients with previously harvested hamstrings or poor muscle control in patellar instability, avoiding strength imbalance in the thigh when allograft availability is limited.
Technique Description:
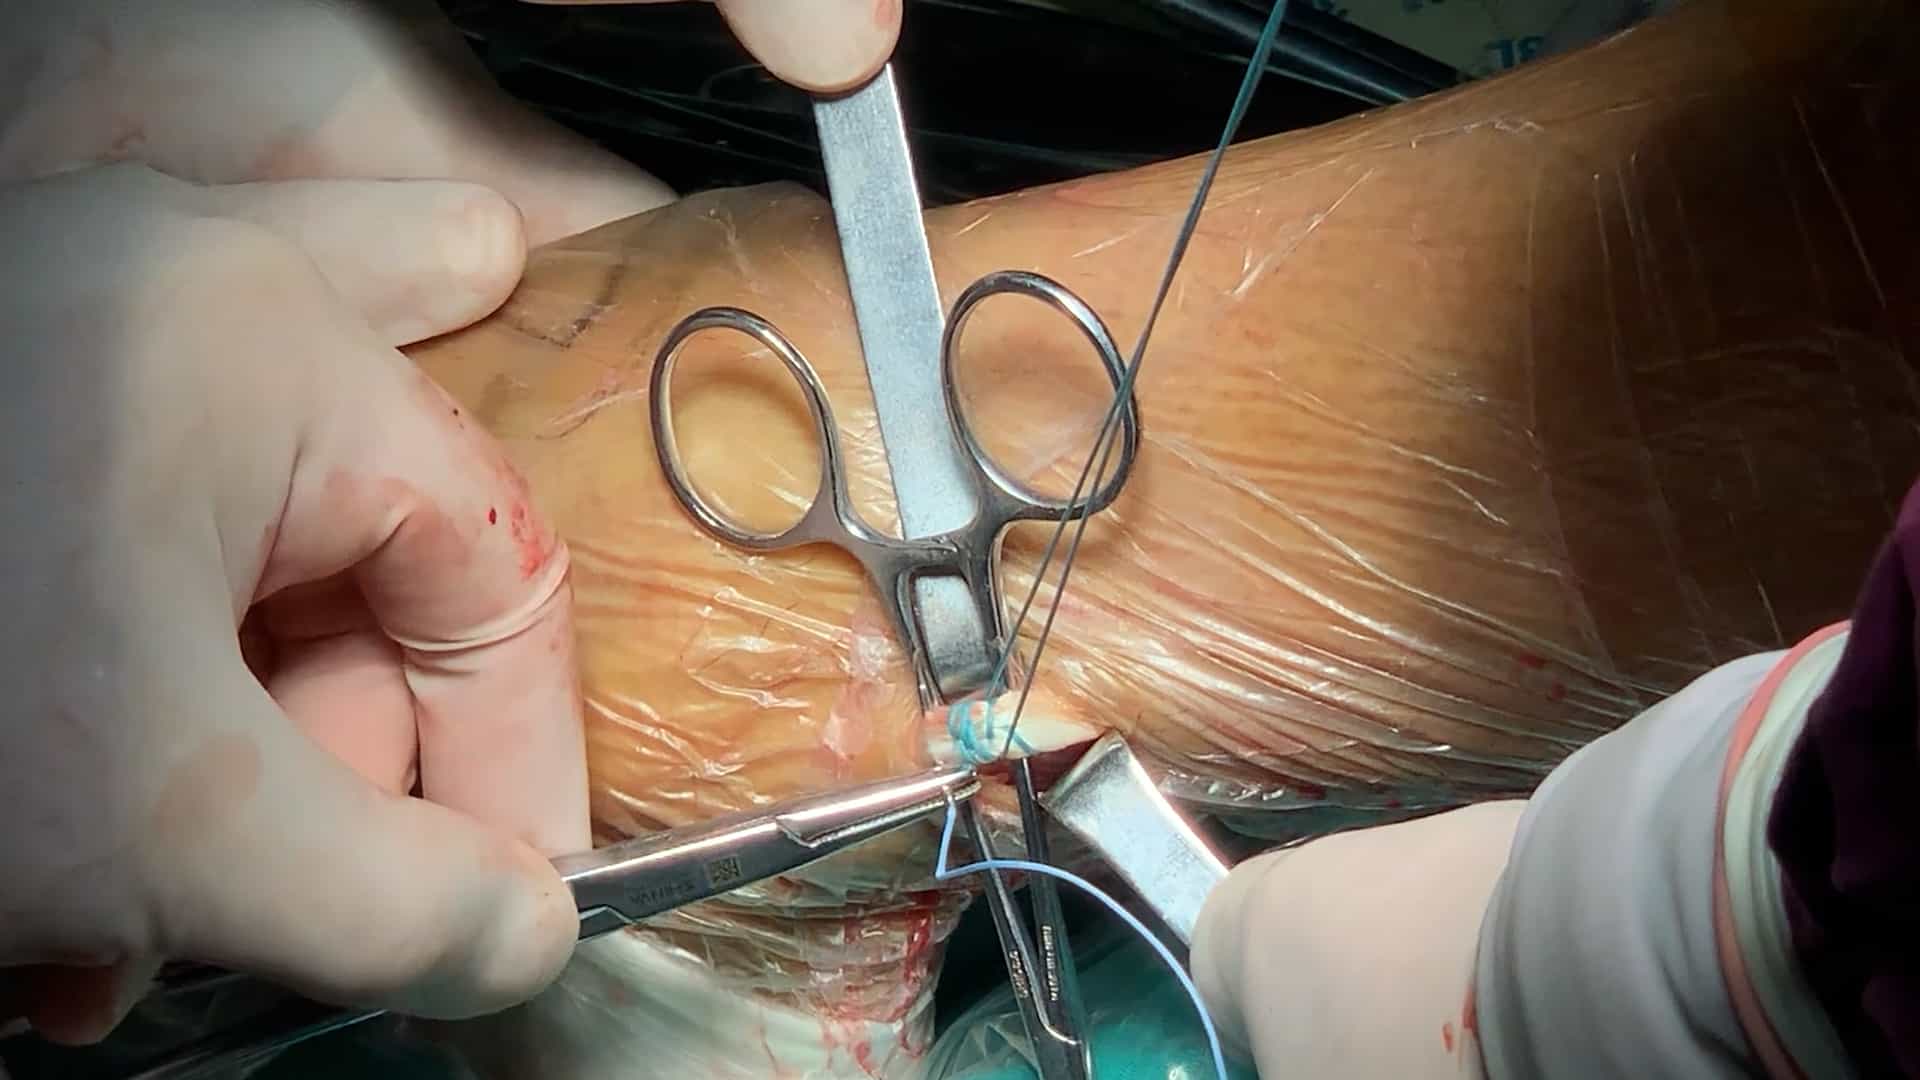
A longitudinal incision is made 2 cm proximal and posterior to the lateral malleolus. The peroneal tendons are identified, and the AHPLT is tagged with a 1-Vicryl suture. The peroneus longus tendon is divided in half with a No. 11 blade, and its anterior half is sectioned anteriorly. The AHPLT is harvested through a tendon stripper. Standard knee incisions are made in the patella's medial border and the femur's medial epicondyle. The graft is passed through the interval between the second and third layers of the medial retinaculum. At 30° of flexion, the graft is fixed to the femur in the MPFL origin point and in the superomedial aspect of the patella.
Results:
A prospective study harvesting the AHPLT graft showed no significant differences between the pre- and postoperative American Orthopaedic Foot & Ankle Society scores (99.4 ± 1.14 vs 99.1 ± 1.40) after a minimum 2-year follow-up and no serious instability, pain, and muscle force decline in the ankle.
Discussion/Conclusion:
The AHPLT provides a consistent, easy-to-harvest, low-morbidity graft for MPFL reconstructions, avoiding an imbalance in the thigh in patients with poor muscular control.
Patient Consent Disclosure Statement:
The author(s) attests that consent has been obtained from any patient(s) appearing in this publication. If the individual may be identifiable, the author(s) has included a statement of release or other written form of approval from the patient(s) with this submission for publication.