Related Experiment Video
Updated: Sep 9, 2025

A High-throughput Method for Measurement of Glomerular Filtration Rate in Conscious Mice
Published on: May 10, 2013
Decline in glomerular filtration rate as an endpoint in heart failure clinical trials: challenges and solutions
Lesley A Inker1, Brendon L Neuen2, Wendy McCallum1
1Division of Nephrology, Tufts Medical Center, 800 Washington Street, Box #391, Boston 02111, MA, USA.

Insights
Assessing chronic kidney disease (CKD) progression in heart failure patients requires understanding glomerular filtration rate (GFR) changes. Early CKD progression endpoints are crucial for trials, but interpreting immediate GFR drops versus long-term benefits is key.
Area of Science:
- Nephrology and Cardiology
- Cardiovascular-Kidney-Metabolic Syndrome
- Clinical Trial Endpoints
Background:
- Chronic kidney disease (CKD) and cardiovascular disease (CVD) share common pathophysiological mechanisms, forming the cardiovascular-kidney-metabolic syndrome.
- CKD and heart failure (HF) frequently coexist, with overlapping therapeutic strategies.
- Accurate assessment of CKD progression in HF patients is vital for individual management and clinical trial evaluation.
Purpose of the Study:
- To explore methods for assessing CKD progression in HF patients, focusing on early surrogate endpoints.
- To evaluate the utility of glomerular filtration rate (GFR) changes as endpoints in HF outcome trials.
- To address challenges in interpreting GFR fluctuations in the context of HF treatments.
Main Methods:
- Review of existing literature on CKD progression and HF outcome measures.
- Analysis of surrogate endpoints for CKD progression, including GFR slope and threshold declines.
- Discussion of challenges and potential solutions for using GFR as an endpoint in HF trials, supported by case studies.
Main Results:
- Glomerular filtration rate (GFR) decline, measured by slope or percentage reduction, is an accepted surrogate endpoint for CKD progression in trials.
- Immediate GFR reduction can occur with guideline-directed HF therapy, complicating long-term benefit assessment.
- Careful interpretation of GFR changes is critical for evaluating HF trial endpoints and patient management.
Conclusions:
- GFR changes offer valuable early endpoints for CKD progression in HF outcome trials.
- Distinguishing transient GFR dips from sustained declines is essential for accurate assessment.
- Standardized interpretation of GFR endpoints will advance both HF patient care and clinical trial design.
Abstract:
Chronic kidney disease (CKD) and cardiovascular disease are tightly interconnected, with common mechanisms that underlie the development and progression of both diseases, recently articulated into the framework of the cardiovascular-kidney-metabolic syndrome. CKD and heart failure commonly coexist in the same individual, with increasing evidence for common therapies in both disease states. It is valuable for patients, clinicians, and regulatory agencies to understand how to best assess CKD progression in patients with heart failure for evaluation of individual patients and as part of an endpoint for outcome trials. Given the relatively short duration of most heart failure outcome trials, early measures of CKD progression prior to the occurrence of clinical events of kidney replacement therapy would be desirable. Such surrogate measures include slowing of the decline in glomerular filtration rate (GFR) decline either computed as annualized mean change in GFR (GFR slope) or time to substantial declines in GFR by specified threshold percentages (40% or 50% GFR decline). Regulatory agencies accept these endpoints for full drug approval which has enabled progress in design and conduct of trials for CKD progression. Application of these endpoints in heart failure outcome trials has the potential for similar progress. However, an immediate reduction in GFR is common following initiation of several of the guideline directed therapy for heart failure. Understanding how to best interpret an immediate GFR reduction vs long term kidney benefit is critical to optimal assessment of endpoint in an outcome trial and in the use of these medications for management of patients with heart failure. Here, the intersection of heart failure and CKD is described, how GFR and its change over time are assessed in both individual patients and in interventional trials, the evidence supporting use of GFR changes as endpoints in CKD progression trials, and the challenges and possible solutions for the use of GFR as endpoint in heart failure outcome trials and for care of individual patients, guided by case studies to inform the discussion.

Related Concept Videos
 01:02
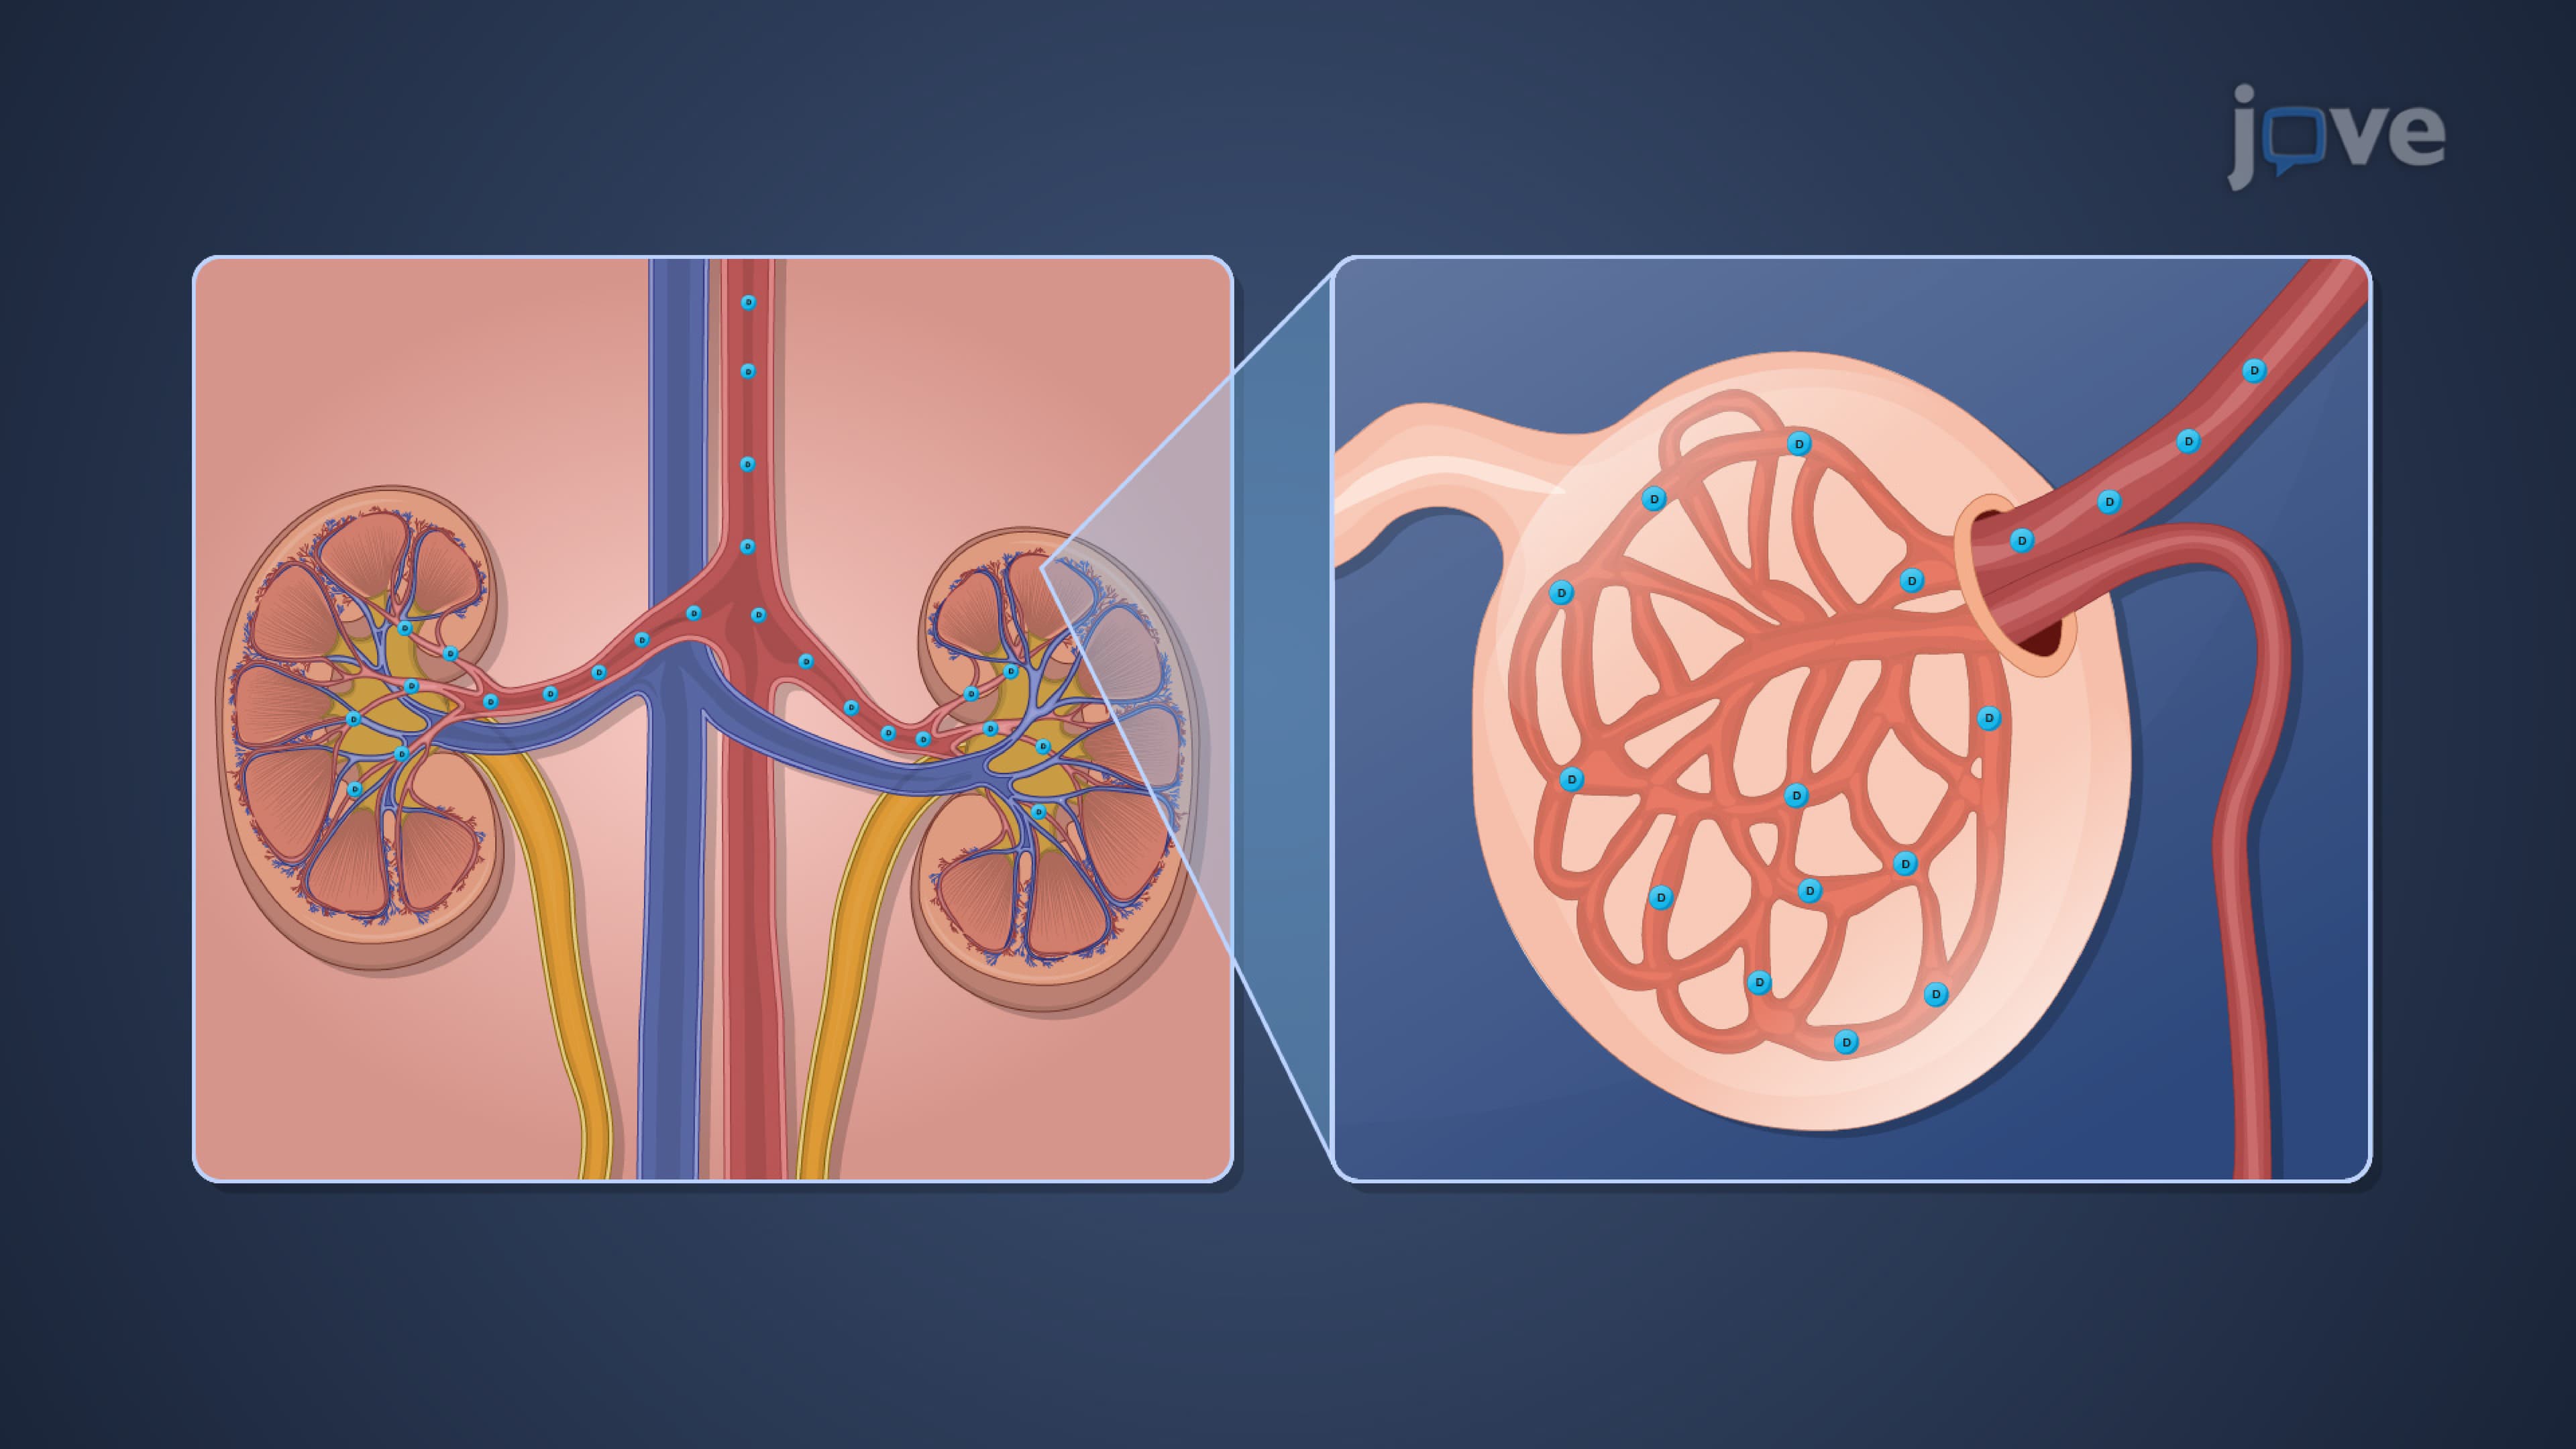
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Heart Failure V: Medical Management
 01:22
Heart Failure Drugs: Diuretics
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...