Related Experiment Video
Updated: Jun 7, 2026
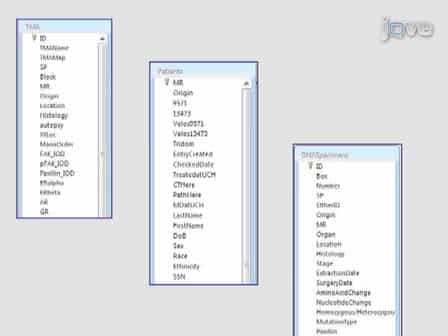

Generation of Comprehensive Thoracic Oncology Database - Tool for Translational Research
Published on: January 22, 2011
Implementing a Precision Medicine Thoracic Service Using In-House Reflex Testing in a Large Academic-Community
Debora S Bruno1, Matthew M Mirsky2, Andrea L Donner3
1Department of Medical Oncology, City of Hope Cancer Center, Atlanta, GA.

Background:
Broad genomic testing is necessary to treat patients with stage IV non-small cell lung cancer (NSCLC). This article describes a NSCLC precision medicine service at an academic-community practice and provides model-based estimates of the impact of a similar intervention.
Research Question:
Will implementation of a precision medicine service increase NSCLC next-generation sequencing (NGS) rates, improve testing turnaround times (TATs), and increase rates of actionable genomic alterations (AGAs)?
Study Design And Methods:
The Precision Medicine Thoracic (PREDICT) service consists of: (1) system-wide reflex testing of patients with stage IV NSCLC by in-house solid tumor NGS-focused assay and programmed cell death ligand 1 (PD-L1) testing; (2) nurse navigator oversight; (3) the molecular tumor board; and (4) an integrated information portal (OncoTracker) for real-time updates on sample processing, results, and treatment recommendations by the molecular tumor board. A decision analytic model compared 4 strategies: PREDICT vs standard care (send-out sequencing and PD-L1 testing), and sequencing of all patients with stage IV NSCLC vs patients with non-squamous histology findings only.
Results:
From January 2016 to December 2018, a total of 626 retrospective patients with stage IV NSCLC were eligible. In the 17 months following the launch of PREDICT, 290 prospective patients were identified. NGS testing rates increased significantly (91.3% vs 60.8%; P < .0001) after PREDICT, whereas TATs from biopsy date were significantly shorter for both NGS (12 vs 18 days; P < .0001) and PD-L1 (7 vs 10 days; P < .0001). AGAs were identified in 29.3% of prospective patients vs 22% of the retrospective cohort (P = .0172). Targeted therapy use increased from 6.8% to 10.6% (P = .048). The decision analytic model predicted superior survival with the PREDICT initiative across all patients, resulting in the highest rates of AGA identification and lowest chemotherapy utilization rates in the first-line setting.
Interpretation:
Implementation of a precision medicine service for stage IV NSCLC comprising reflex testing, nurse navigation, a molecular tumor board, and an information portal at a combined academic-community practice led to higher NGS testing rates and shorter TATs. The result was identification of more actionable mutations and higher rates of first-line targeted therapy utilization. Decision analytic modeling suggests the superiority of this initiative across all patients.
More Related Videos
 10:35
A Blood-based Test for the Detection of ROS1 and RET Fusion Transcripts from Circulating Ribonucleic Acid Using Digital Polymerase Chain Reaction
Published on: April 5, 2018
 07:59
Author Spotlight: Advancements in Molecular Biomarker Testing for Non-Squamous Non-Small Cell Lung Cancer
Published on: September 8, 2023
Related Concept Videos
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for:
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...