Related Experiment Video
Updated: Jan 18, 2026


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Development and validation of a nomogram for predicting the risk of intestinal barrier dysfunction in patients after
Qinghua Zou1, Ruotian Wang2, Yunfang Dong3
1Department of Gastrointestinal Surgery, The Second Affiliated Hospital of Kunming Medical University, Kunming, Yunnan, China.

Background:
Intestinal barrier dysfunction (IBDF) can lead to systemic inflammatory response syndrome and multiple organ failure, severely jeopardizing patient health. Preventing the occurrence of IBDF is crucial, but effective prediction and assessment tools are currently lacking. In this study, we aimed to construct and validate a nomogram for early prediction of the risk of IBDF in patients undergoing major abdominal surgery.
Methods:
A total of 684 patients undergoing major abdominal surgery were prospectively included, among whom patients from the Second Affiliated Hospital of Kunming Medical University and Kunming Haikou Hospital were assigned to the training (n = 480) and external validation (n = 204) cohorts, respectively. Univariate and multivariate logistic regression analyses were performed to screen for independent predictors of IBDF. Based on these factors, the nomogram was constructed to predict IBDF occurrence. The area under the receiver operating characteristic curve (AUC), calibration plot, decision curve analysis (DCA), and clinical impact curve (CIC) were used to evaluate the predictive performance and clinical utility of the model.
Results:
In the training and validation cohorts, 28.3 and 26.9% of patients experienced IBDF, respectively. The multivariate logistic regression analysis showed that surgical method, operative time, blood loss, infusion volume, albumin, interleukin-6, neutrophil-to-lymphocyte ratio, and opioid use were independent predictors of IBDF. The AUC of the IBDF nomogram based on these eight variables was 0.946 (95% CI: 0.921-0.970) and 0.944 (95% CI: 0.907-0.981) in the training and validation cohorts, respectively. The calibration curves showed good consistency, and the DCA and CIC results showed that the constructed model has good clinical applicability.
Conclusion:
We established and validated an IBDF-nomogram for the first time to predict the risk of IBDF in patients after major abdominal surgery. This model provides a practical tool for clinicians to identify high-risk patients with IBDF in the early stage, which may have significance in guiding clinical treatment decisions.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:23
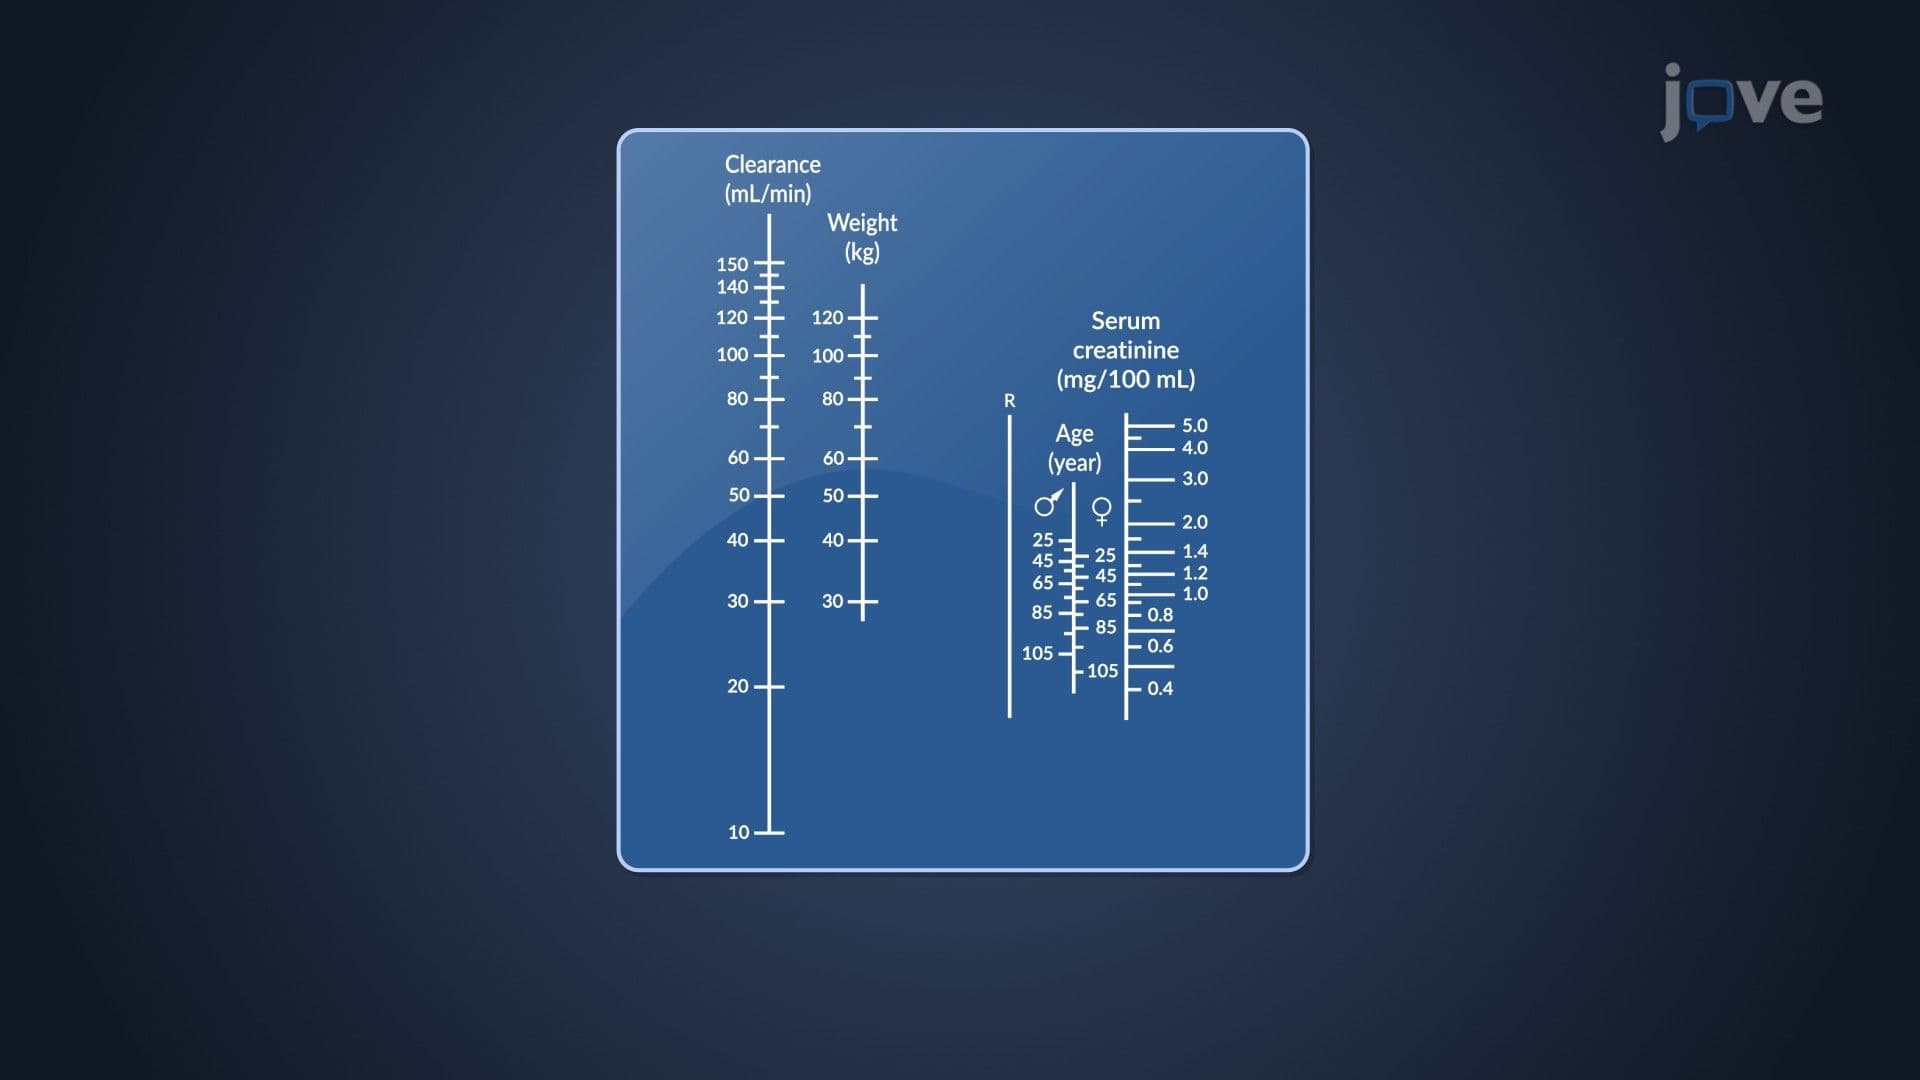
Dosage Regimen Designs: Nomograms and Tabulations