Related Experiment Video
Updated: Jan 18, 2026


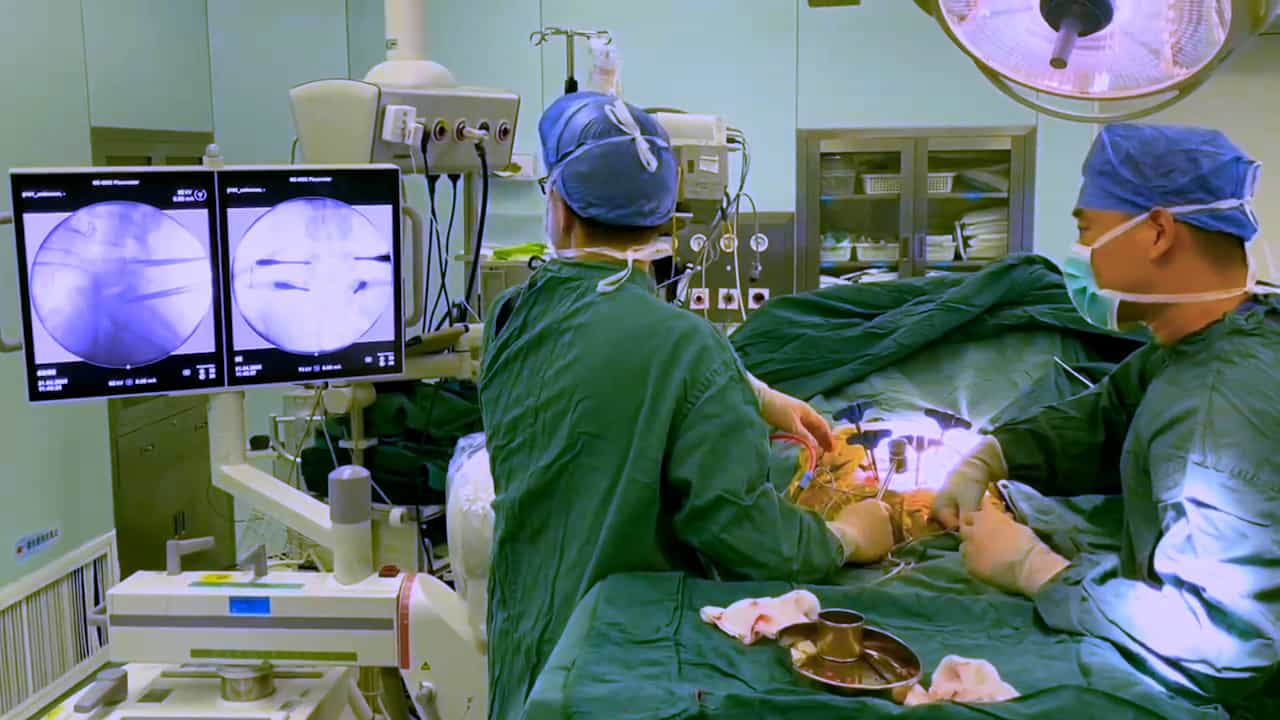
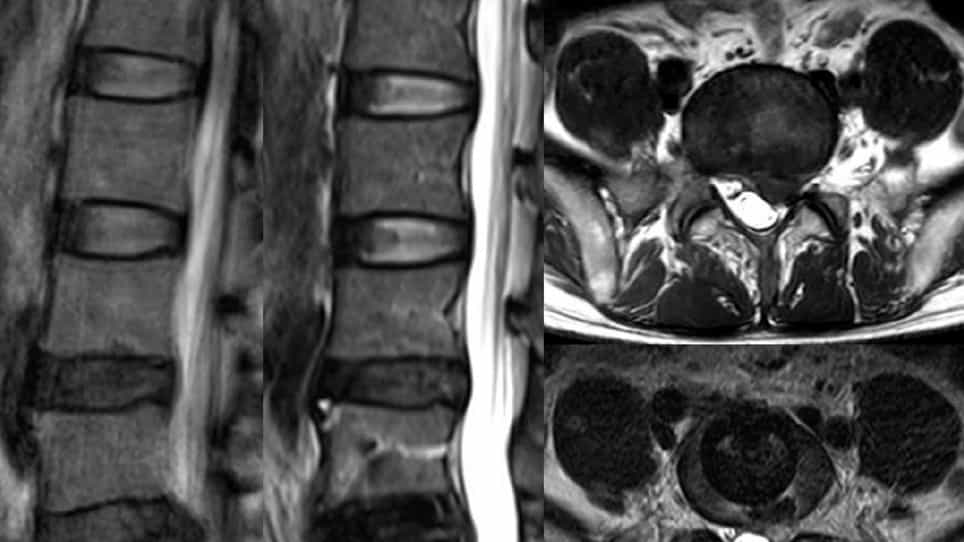
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Minimally Invasive vs Open Surgery for Thoracolumbar Fractures in Patients With Ankylosing Spinal Diseases: A
Mohammad Daher1, Marven Aoun, Ethan J Cottrill
1From the Department of Orthopedic Surgery (Daher, Aoun, Sebaaly), Hotel Dieu de France Hospital, Beirut, LEBANON, the Department of Orthopedic Surgery (Daher, Diebo, Daniels), Brown University, Providence, RI, the Department of Orthopedic Surgery (Daher, Cottrill, Passias), Duke University, Durham, NC, the Department of Orthopedic Surgery (Hurley), San Antonio Military Medical Center, San Antonio, TX, and the Orthopedic Surgery (Lavelle), State University of New York Upstate Medical University, Syracuse, NY.

Background:
Surgical management of thoracolumbar fractures in patients with ankylosing spinal disorders such as ankylosing spondylitis (AS) and diffuse idiopathic skeletal hyperostosis remains debated. Although several studies have compared minimally invasive surgery to open fixation of thoracolumbar fractures in this patient population, a meta-analysis compiling the literature on this topic is lacking.
Methods:
Following the PRISMA guidelines, PubMed, Cochrane, and Google Scholar (pages 1 to 20) were accessed and explored until October 2024. The extracted data consisted of complications, mortality, surgery-related parameters, postoperative back pain, and postoperative Cobb angle. Across all studies, mean differences with 95% confidence intervals were used for continuous data, whereas odds ratio was used for dichotomous data.
Results:
Eight retrospective articles were included in the meta-analysis, including 295 patients, with 164 in the MIS group and 131 in the open group. Patients undergoing minimally invasive fixation were found to have lower rates of overall complications (OR = 0.43; 95% CI, 0.25-0.75, P = 0.003), shorter surgical time (MD = -67.79; 95% CI, -91.61 to -43.96, P < 0.001) and hospital stay (MD = -14.08; 95% CI, -25.95 to -2.21, P = 0.02), and less blood loss (MD = -1.52; 95% CI, -2.70 to -0.33, P = 0.01). However, there was no difference in postoperative back pain or Cobb angle between the two groups.
Conclusion:
Patients undergoing MIS treatment of fractures through ankylosed spines had lower rates of complications, less EBL, and shorter surgical time and LOS, highlighting the potential benefits of minimally invasive fixation of thoracolumbar fractures. However, studies with longer-term follow-up to assess the longevity of MIS fixation are needed, and furthermore some injury patterns may not be amenable to MIS fixation. Also, some institutions may not have resources to provide MIS techniques, and open fixation remains a safe and reliable option for treatment.