
Follow-up of patients with mild COVID-19 using subjective, acoustic, and aerodynamic measurements
Zhi-Xue Xiao1,2, Qing-Yi Ren1, Wei-Qing Liang1
1Department of Otolaryngology, Guangdong Provincial People's Hospital (Guangdong Academy of Medical Sciences) Southern Medical University Guangzhou China.

Objectives:
To gain a comprehensive understanding of the vocal repercussions experienced by mild COVID-19 infection, as well as the duration and underlying factors contributing to these effects.
Methods:
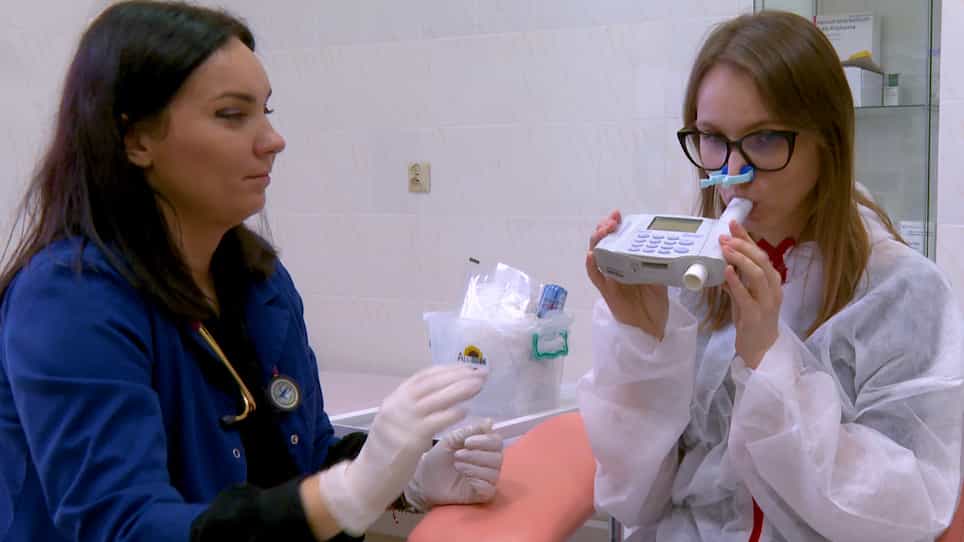
Ten participants with mild COVID-19 infection were included as the experimental group to evaluate the voice metrics changes at 15 days (D15), 30 days (D30), and 60 days (D60) after mild COVID-19 infection, and 10 healthy people were taken as the normal control group. Self-assessment and objective measures were taken at each time point, including questionnaires for voice handicap index (VHI) and reflux symptom index (RSI), as well as acoustic and aerodynamic indicators such as fundamental frequency (F0), Jitter, Shimmer, noise-to-harmonics ratio, sound pressure level (SPL), phonation threshold pressure (PTP), phonation threshold flow, aerodynamic resistance(AR), aerodynamic efficiency, mean expiration airflow, maximum phonation time, and maximum loudest phonation time.
Results:
Notable elevations in RSI and VHI were observed during the D15 assessment, but by D60, these levels had returned to normal. At D60, Shimmer, PTP, and PTF significantly increased compared to the control group, while HNR and AR significantly decreased (p < 0.05). F0, SPL, and PTP significantly increased compared to 15 days (p < 0.05), while other acoustic and aerodynamic indicators showed no significant changes in intra-group and inter-group comparisons.
Conclusions:
Our study demonstrated that COVID-19 infection has a detrimental effect on voice production. Although subjective discomfort may gradually subside within 2 months after onset, alterations in phonation mode can be delayed. It is essential for healthcare professionals to remain vigilant in preventing any organic changes that may arise due to COVID-19-related voice disorders, such as muscle tension dysphonia.

Related Concept Videos
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...