Related Experiment Video
Updated: Aug 9, 2026
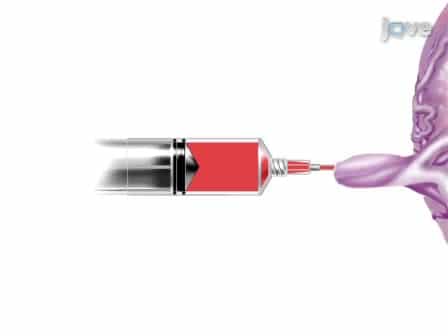

Guide Wire Assisted Catheterization and Colored Dye Injection for Vascular Mapping of Monochorionic Twin Placentas
Published on: September 5, 2011
Uterine Artery Pulsatility Index in Singleton Pregnancies Conceived via Assisted Reproductive Technology Versus
Antonios Siargkas1, Ioannis Tsakiridis1, Areti Faka1
1Third Department of Obstetrics and Gynecology, School of Medicine, Faculty of Health Sciences, Aristotle University of Thessaloniki, 54124 Thessaloniki, Greece.

Abstract:
Background/Objectives: Uterine artery pulsatility index (UtA-PI) is a key biomarker of placental function, but its clinical interpretation in assisted reproductive technology (ART) pregnancies is uncertain. This meta-analysis aimed to assess trimester- and method-specific UtA-PI differences between ART and spontaneous conceptions (SC) and to examine associated risks for preeclampsia (PE) and small-for-gestational-age (SGA) neonates to contextualize its findings. Methods: A systematic search of MEDLINE, Scopus, and the Cochrane Library was conducted through 25 June 2025. We included observational studies comparing UtA-PI and perinatal outcomes in singleton ART versus SC pregnancies. The primary outcome was the standardized mean difference (SMD) in first (until the 13+6 gestational week) and second trimester (14+0-23+6 gestational weeks) UtA-PI measurements; secondary outcomes were PE and SGA rates. Analyses were stratified by ART modalities. Random-effects models were used, and study quality was evaluated using the Newcastle-Ottawa Scale and risk of bias with QUIPS tool (INPLASY registration: INPLASY202560104). Results: Thirteen cohort studies were included. Overall, ART pregnancies had significantly lower UtA-PI values than SC in both the first (SMD = -0.28; 95% CI: -0.53 to -0.03) and second trimesters (SMD = -0.20; 95% CI: -0.36 to -0.04). These reductions were driven by oocyte donation (first-trimester SMD = -0.70; 95% CI: -1.21 to -0.18; second-trimester SMD = -0.46; 95% CI: -0.65 to -0.26) and artificial cycle frozen embryo transfers (ET) (first-trimester SMD = -0.69; 95% CI: -1.00 to -0.39). These lower UtA-PI values typically suggest better placental perfusion and a lower risk of placental related complications. However, ART pregnancies had an elevated overall risk for PE (risk ratio [RR] = 2.32; 95% CI: 1.72 to 3.12), with the highest risk in oocyte donation (RR = 6.11; 95% CI: 3.35 to 11.17) and artificial cycle frozen ET (RR = 3.45; 95% CI: 1.51 to 7.90). Conclusions: ART pregnancies, particularly from oocyte donation and artificial cycle frozen ET, show lower UtA-PI values despite a significantly elevated risk for PE. This finding suggests that mechanisms other than placental perfusion contribute to PE development. Clinically, the ART method is an independent risk factor for PE, and UtA-PI interpretation should be adjusted accordingly. Further research is crucial to elucidate the underlying pathophysiology.
More Related Videos
 09:52
Accurate and Simple Evaluation of Vascular Anastomoses in Monochorionic Placenta using Colored Dye
Published on: September 5, 2011
 09:51
Model Surgical Training: Skills Acquisition in Fetoscopic Laser Photocoagulation of Monochorionic Diamniotic Twin Placenta Using Realistic Simulators
Published on: March 21, 2018
