MRI-fusion biopsy era: the role of perineural invasion in low-risk prostate cancer
Related Experiment Video
Updated: Jul 10, 2026
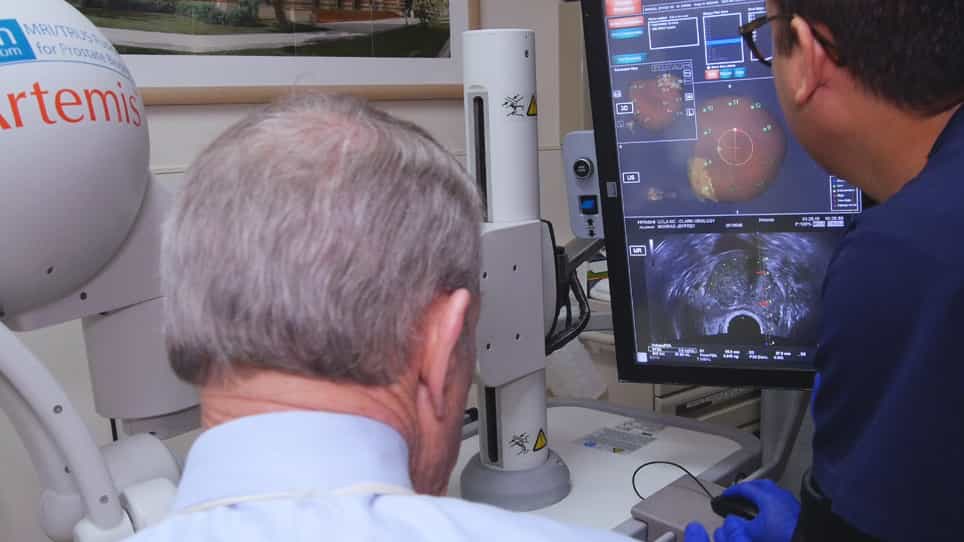
Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Nethusan Sivanesan1, Gabriela M Diaz1, Sebastien Strachan2
1Department of Urology, Yale School of Medicine, New Haven, CT, USA.

Objective:
To evaluate whether perineural invasion independently predicts Gleason score upgrading during active surveillance in patients undergoing MRI-US fusion biopsy.
Patients And Methods:
We retrospectively analyzed 325 patients initially diagnosed with Gleason Grade Group (GGG) 1 prostate cancer who underwent at least one subsequent biopsy. Demographics, imaging, and clinical variables were recorded. Univariate and multivariate logistic regression models assessed the association between perineural invasion and Gleason upgrading (GGG2+) on follow-up biopsy.
Results:
Among 325 eligible patients diagnosed with GGG 1 prostate cancer on initial biopsy, 51 (15%) had perineural invasion, while 274 (84%) did not. Gleason upgrade occurred in 110 (34%) patients. Upgrading was observed in 24 of 51 patients (47%) with perineural invasion, compared to 86 of 274 patients (32%) without perineural invasion (p = 0.03). On univariate analysis, older age (OR 1.03; p=0.03), African American race (OR 2.22; p=0.04), number of positive cores (OR 1.13; p=0.007), and cancer detected on targeted biopsy (OR 2.26; p=0.01) were associated with upgrading. In multivariable analysis, perineural invasion (OR 1.84; p=0.1) was not independently associated with Gleason upgrading when adjusting for PI-RADS 4-5 (OR 1.98; p=0.01). However, cancer detected on targeted biopsy (OR 2.26; p = 0.01) and African American race (OR 3.2; p = 0.01) remained independently associated with upgrading.
Conclusions:
In this contemporary series of patients managed with active surveillance in the era of MRI-ultrasound fusion biopsy, perineural invasion is not associated with Gleason upgrade on subsequent biopsy when adjusting for MRI- US fusion biopsy characteristics. Our findings highlight that a PI-RADS 4 or 5 lesion, and cancer found within an MRI-visible lesion are more predictive of subsequent progression in patients with GGG1 PCa.