Related Experiment Video
Updated: Jan 17, 2026
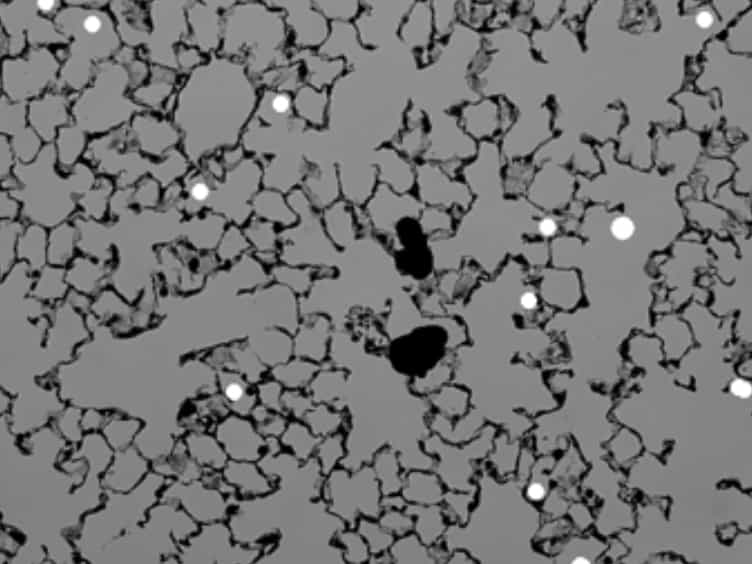

Automated Measurement of Pulmonary Emphysema and Small Airway Remodeling in Cigarette Smoke-exposed Mice
Published on: January 16, 2015
Quantitatively Assessed Emphysema Severity on HRCT Independently Predicts Coronary Artery Disease in COPD: A
Luoman Su1, Chen Qian2, Chunchun Yu1
1Department of Pulmonary and Critical Care Medicine, Key Laboratory of Interventional Pulmonology of Zhejiang Province, The First Affiliated Hospital of Wenzhou Medical University, Wenzhou, People's Republic of China.

Background:
Chronic obstructive pulmonary disease (COPD) is associated with an increased risk of coronary artery disease (CAD). However, the role of emphysema, which represents an important structural subtype of COPD, in the development of CAD remains insufficiently clarified. This study aimed to evaluate whether quantitatively assessed emphysema on high-resolution computed tomography (HRCT) independently predicts CAD in COPD patients.
Methods:
This retrospective cohort study included 392 COPD patients with no prior history of CAD between 2015 and 2020. All participants underwent HRCT for automated emphysema quantification using 3D Slicer software. Emphysema extent was quantified as the percentage of low attenuation areas (LAA%) below -950 Hounsfield units, with severe emphysema defined as LAA% >16.95%. Logistic regression and restricted cubic spline (RCS) analysis were employed to assess the relationship between emphysema index and CAD, including subgroup and interaction analyses. The ability of the emphysema index to predict CAD was evaluated using receiver operating characteristic (ROC) curves.
Results:
Severe emphysema was independently associated with a higher risk of CAD in COPD patients (OR = 2.08, 95% CI: 1.30-3.34; p = 0.002). This association remained robust even after adjusting for confounders (adjusted OR= 2.28, p = 0.005). RCS analysis indicates that the risk of CAD increases with the rise of the emphysema (p for nonlinearity =0.031). The area under the ROC curve for the predictive model was 0.81 (95% CI 0.77, 0.86). Additionally, patients with severe emphysema exhibited significantly more complex coronary lesions, reflected by higher SYNTAX scores (median 10.00 vs 16.29; p = 0.013).
Conclusion:
Quantitative HRCT-based emphysema independently predicts CAD in COPD and demonstrates additive risk with traditional cardiovascular factors. Integrating emphysema quantification with clinical risk assessment improves CAD risk stratification in COPD patients.
More Related Videos

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...