Related Experiment Video
Updated: Jan 17, 2026
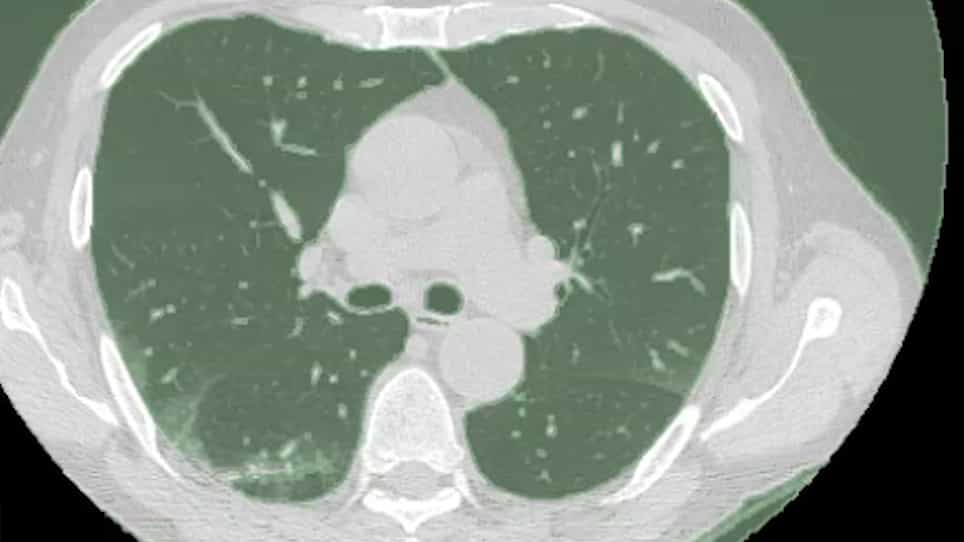

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Cryptogenic Organizing Pneumonia
1Department of Medicine, Division of Pulmonary, Allergy, and Critical Care Medicine, University of Colorado Anschutz Medical Center, Aurora, Colorado, United States.

Abstract:
Cryptogenic organizing pneumonia (COP), formerly called bronchiolitis obliterans organizing pneumonia (BOOP), was first described in the 1980s and is classified as a rare idiopathic interstitial pneumonia (IIP). COP classically presents in a subacute fashion following a flu-like illness with fever, non-productive cough, and fatigue. Imaging often reveals diffuse, bilateral, peribronchovascular and peripheral, consolidative and ground-glass opacities although various imaging subtypes also exist. Physical examination may be normal or reveal inspiratory crackles. Hypoxemia, when present, is commonly identified with exertion but can also occur at rest. Diagnostic evaluation relies on excluding secondary causes of organizing pneumonia and includes a thorough history including medications, exposures, and signs or symptoms of underlying rheumatologic disease. Invasive diagnostic testing including tissue sampling allows for histopathologic confirmation of COP while excluding secondary causes including infection and malignancy. Although video-assisted thoracoscopic surgery (VATS) lung biopsy is often the preferred method of obtaining sufficient tissue, less invasive means may be employed based on patient-specific factors. A defining feature of COP is steroid-responsiveness, and most experts recommend prolonged corticosteroid courses (6-12 months). Response to corticosteroids and prognosis are typically excellent. Relapse rates range from 25 to 50% and occur most often during steroid taper or complete withdrawal necessitating additional therapy. Steroid-sparing immunosuppression may be used in select circumstances. Further study is needed to define optimal corticosteroid dose and duration.
Insights
Cryptogenic organizing pneumonia (COP), a rare lung disease, presents with flu-like symptoms and lung opacities. It is typically treated effectively with prolonged corticosteroid courses, though relapses can occur.
Area of Science:
- Pulmonology
- Respiratory Medicine
- Idiopathic Interstitial Pneumonia
Background:
- Cryptogenic organizing pneumonia (COP), previously known as bronchiolitis obliterans organizing pneumonia (BOOP), is a rare idiopathic interstitial pneumonia (IIP).
- It typically manifests subacutely with flu-like symptoms, including fever, non-productive cough, and fatigue.
- Imaging reveals characteristic lung opacities, and hypoxemia may be present.
Purpose of the Study:
- To review the clinical presentation, diagnosis, and management of Cryptogenic Organizing Pneumonia (COP).
- To highlight the diagnostic challenges and the importance of excluding secondary causes.
- To discuss the established treatment protocols and prognosis for COP patients.
Main Methods:
- Diagnostic evaluation involves excluding secondary causes of organizing pneumonia through thorough history, medication review, exposure assessment, and rheumatologic disease screening.
- Invasive diagnostic testing, including tissue sampling via video-assisted thoracoscopic surgery (VATS) lung biopsy, is crucial for histopathologic confirmation.
- Less invasive methods may be considered based on individual patient factors.
Main Results:
- COP is characterized by steroid-responsiveness, with prolonged corticosteroid therapy (6-12 months) being the mainstay of treatment.
- Prognosis is generally excellent, with a high response rate to corticosteroids.
- Relapse rates range from 25% to 50%, often occurring during or after steroid withdrawal, necessitating further management.
Conclusions:
- Cryptogenic Organizing Pneumonia (COP) is a treatable condition with a favorable prognosis, primarily managed with corticosteroids.
- Careful monitoring for relapses and consideration of steroid-sparing agents in select cases are important.
- Further research is required to optimize corticosteroid dosing and duration for COP management.


Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction