Related Experiment Video
Updated: Jan 17, 2026
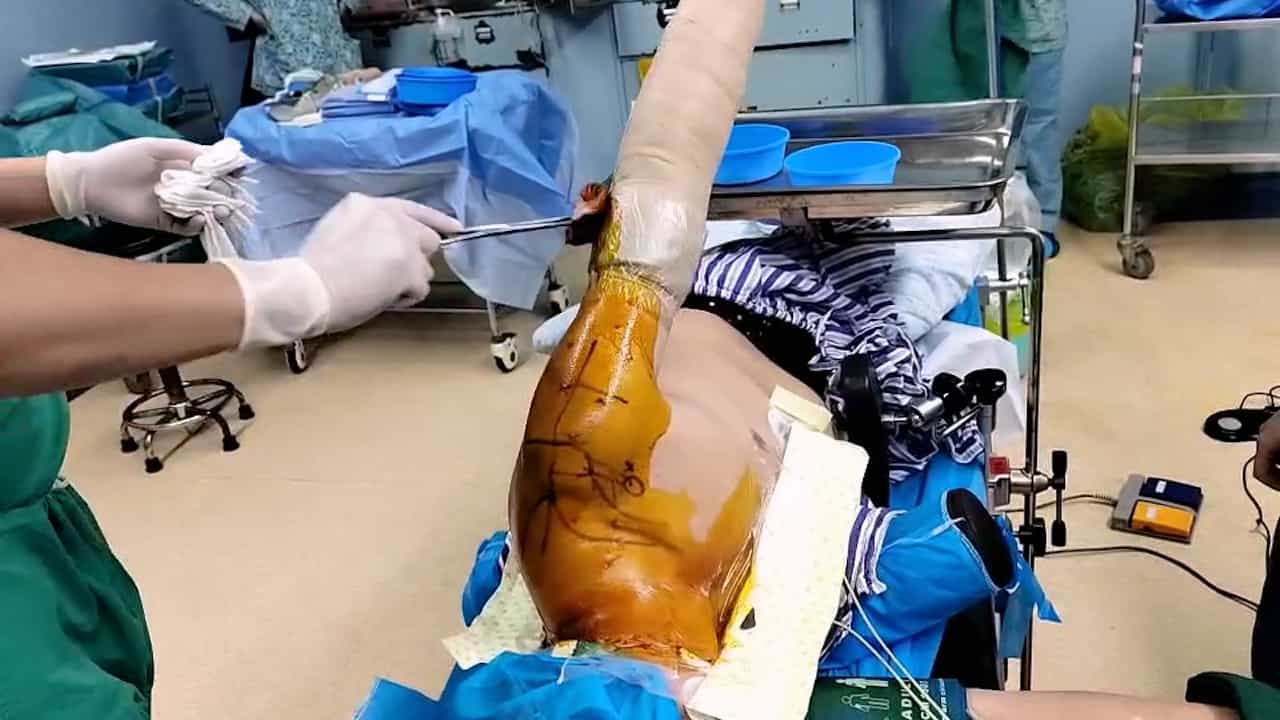

Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Subcoracoid impingement exacerbates pain and scapular dysfunction in full-thickness rotator cuff tears
Yi-Hsuan Weng1, Yang-Ting Chien1, Chon-Kio Wong1
1School and Graduate Institute of Physical Therapy, College of Medicine, National Taiwan University, Taipei, Taiwan.

Background:
Subcoracoid impingement co-occurs with subacromial impingement in 19% of the patients with rotator cuff tears. The influence of subcoracoid impingement in patients with full-thickness rotator cuff tear (FT-RCT) remains unknown. Therefore, it is worthwhile to investigate potential differences between FT-RCT patients with and without subcoracoid impingement.
Methods:
Twenty-two participants were categorized as having an FT-RCT combined with subcoracoid impingement, while 25 others were diagnosed with an FT-RCT without subcoracoid impingement. Characteristics and tear sizes were recorded using ultrasonography (USG). Humeral head migration was assessed by calculating the acromiohumeral distance using USG at 0°, 60°, and 90° of shoulder abduction. Shoulder range of motion, pain levels, and self-reported shoulder function were evaluated. Scapular kinematics (upward/downward rotation, anterior/posterior tilt, and external/internal rotation) and associated muscle activities (upper trapezius, lower trapezius, serratus anterior [SA], and teres major [TM]) were recorded during arm raising and lowering using motion tracing and surface electromyography systems, respectively.
Results:
The FT-RCT combined with subcoracoid impingement group experienced slightly higher pain levels (1.7 ± 0.6, 95% CI = 0.5-2.9, P = .008) and marginally more humeral head superior migration from 0°-60° shoulder abduction (0.14 ± 0.05 cm, 95% CI = 0.03-0.25 cm, P = .017) compared to the FT-RCT without subcoracoid impingement group. Regarding scapular biomechanics, the FT-RCT combined with subcoracoid impingement group demonstrated decreased upward rotation during arm lowering (4.0 ± 1.3°, 95% CI = 1.4-6.5°, P = .003) as well as decreased SA muscle activation during arm lowering (18.8% ± 8.5%, 95% CI = 1.7%-36.0%, P = .032) and decreased TM muscle activation during arm raising (11.4 ± 6.0%, 95% CI = 0.6%-23.5%, P = .018).
Conclusion:
Patients with FT-RCT combined with subcoracoid impingement report a slightly higher pain score. Greater superior humeral head migration, coupled with reduced scapular upward rotation, may exacerbate impingement and worsen symptoms. Additionally, these patients exhibit decreased recruitment of the SA and TM muscles. Despite reaching statistical significance, the magnitude of difference may limit its clinical applicability and warrants cautious interpretation.
More Related Videos
Related Concept Videos
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:23
Rheumatic Heart Disease I: Introduction
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...