Related Experiment Video
Updated: Jan 17, 2026


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Prognostic risk factors in upper gastrointestinal perforation: the role of body composition parameters
Teng Zhu1,2, Huayan Gu3, Yuefeng Chen1,2
1Department of Gastrointestinal Surgery, The First Affiliated Hospital of Wenzhou Medical University, Wenzhou, China.

Background:
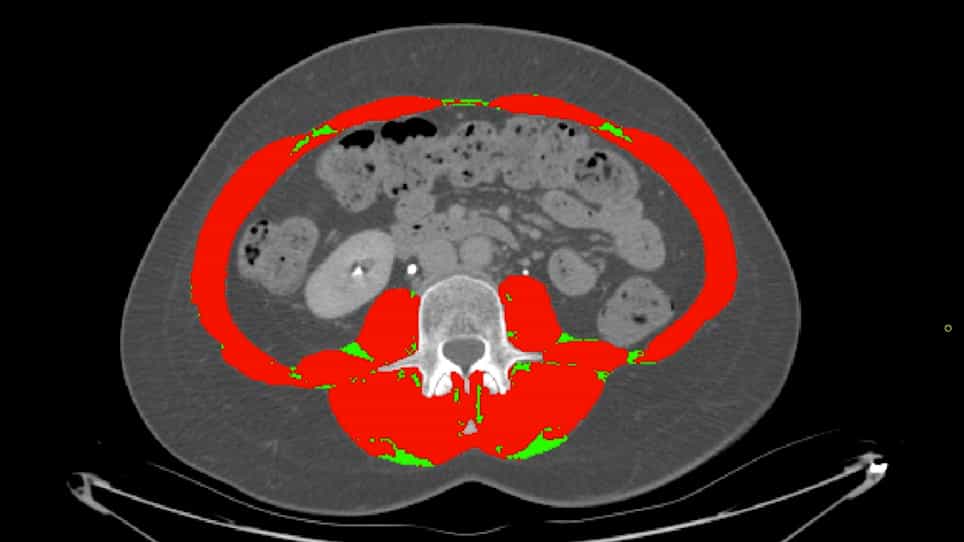
Despite medical advances, the prognosis for upper gastrointestinal perforation remained poor. The aim of our study was to identify predictors of adverse outcomes.
Methods:
We retrospectively analyzed laboratory data from patients with upper gastrointestinal perforation at the First Affiliated Hospital of Wenzhou Medical University (January 2021-December 2023), categorizing them according to septic shock, intensive care unit (ICU) admission, and postoperative complications.
Results:
Univariate and multivariate analyses of 200 patients with upper gastrointestinal perforation identified predictors of a poor prognosis: low muscle reserve (OR = 3.82, 95% CI 1.36-10.71, p = 0.011), high visceral fat area (VFA) (OR = 3.54, 95% CI 1.16-10.80, p = 0.026), and platelet-to-lymphocyte ratio (PLR) (OR = 1.01, 95% CI 1.01-1.01, p = 0.048) predicted septic shock. Sex (OR = 0.22, 95% CI 0.06-0.78, p = 0.020), high VFA (OR = 4.84, 95% CI 1.38-17.02, p = 0.014), prothrombin time (PT) (OR = 1.54, 95% CI 1.09-2.18, p = 0.014), and D-dimer (OR = 1.16, 95% CI 1.01-1.34, p = 0.048) influenced ICU admission. Meanwhile, surgical approach (OR = 7.82, 95% CI 1.94-31.57, p = 0.004), maximum perforation diameter (OR = 1.08, 95% CI 1.02-1.15, p = 0.013), and white blood cell (WBC) count (OR = 0.88, 95% CI 0.78-0.99, p = 0.039) were linked to postoperative complications.
Conclusion:
Our research found that the following factors were prognostic for upper gastrointestinal perforation: low muscle reserve, high VFA, PLR, sex, PT, D-dimer levels, surgical approach, WBC count, and perforation size.

Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors