Efficacy of a lung recruitment manoeuvre in children undergoing general anaesthesia with a supraglottic airway
Related Experiment Video
Updated: Jan 6, 2026
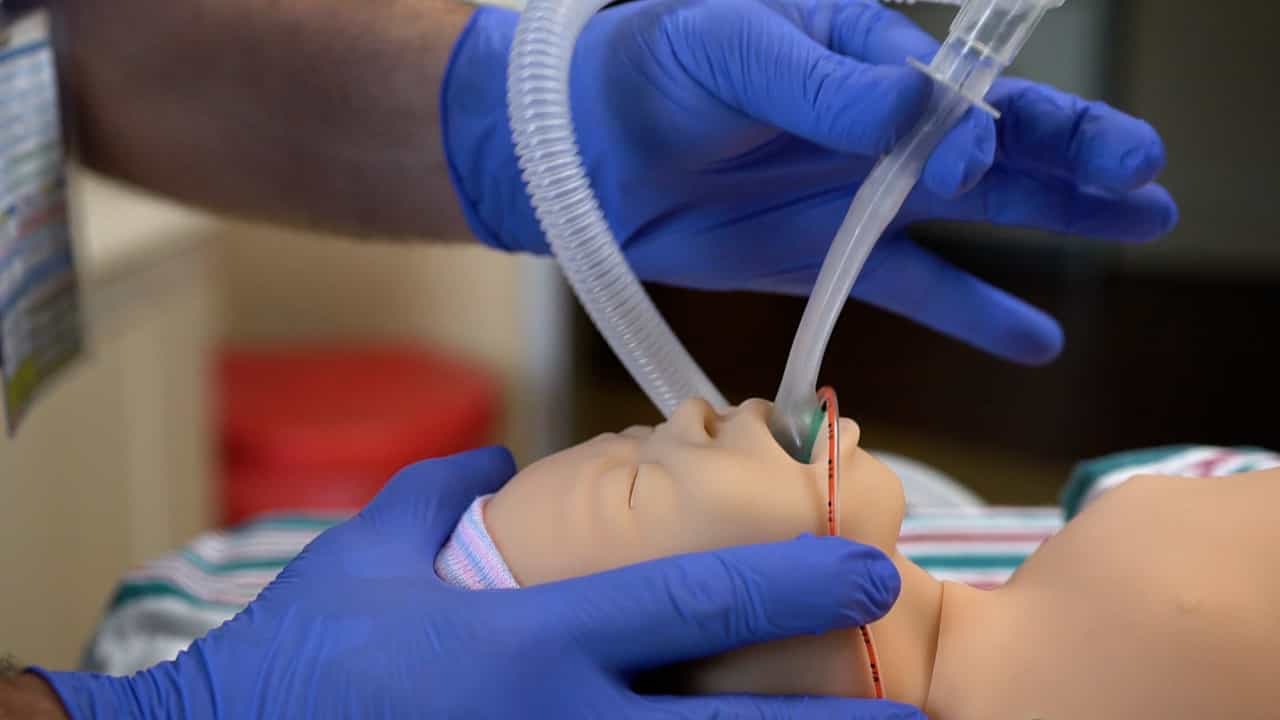
Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Ricarda Lippuner1, Charlotte Pellaud2, Markus Huber1
1Department of Anaesthesiology and Pain Medicine, Bern University Hospital, University of Bern, Bern, Switzerland.

Insights
A lung recruitment maneuver effectively restores end-expiratory lung volume (EELV) to baseline in children during general anesthesia with a supraglottic airway. This technique helps counteract anesthesia-induced lung atelectasis and improve oxygenation.
Area of Science:
- Pediatric Anesthesiology
- Respiratory Physiology
- Critical Care Medicine
Background:
- Lung atelectasis is a common complication of pediatric general anesthesia, potentially leading to impaired oxygenation.
- Lung recruitment maneuvers (LRMs) are explored as a strategy to mitigate anesthesia-related lung collapse.
- Feasibility of LRMs in pediatric patients with supraglottic airways requires evaluation.
Purpose of the Study:
- To assess the efficacy of a lung recruitment maneuver in restoring end-expiratory lung volume (EELV) to baseline in pediatric patients.
- To evaluate the impact of LRMs on lung homogeneity using electrical impedance tomography (EIT).
- To determine if LRMs can counteract anesthesia-induced atelectasis in children with supraglottic airways.
Main Methods:
- Feasibility study including children (ASA 1-2, 10-20 kg) undergoing anesthesia with a supraglottic airway.
- A recruitment maneuver was applied using specific ventilator settings and adjustable pressure-limiting (APL) valve pressures.
- End-expiratory lung impedance (EELI) and global inhomogeneity index were measured using electrical impedance tomography (EIT) at baseline and post-maneuver.
Main Results:
- The median estimated difference in EELV post-recruitment maneuver versus baseline was -0.9 ml kg⁻¹ (-1.6 to -0.1), falling within the predefined equivalence margin of ±2 ml kg⁻¹.
- No significant changes were observed in the global inhomogeneity index (0.0 [0.03-0.04]).
- 74 out of 95 eligible children's datasets were analyzed.
Conclusions:
- A lung recruitment maneuver effectively restores end-expiratory lung volume (EELV) to baseline in children during general anesthesia with a supraglottic airway.
- LRMs appear to be a safe and effective strategy for managing anesthesia-induced atelectasis in this pediatric population.
- Further research may explore optimal LRM protocols in pediatric anesthesia.
Background:
Lung atelectasis is a well-recognised consequence of general anaesthesia in children and can cause poor oxygenation. Lung recruitment manoeuvre has been proposed as a strategy to counteract atelectasis. In this feasibility study, we evaluated whether a recruitment manoeuvre in children with a supraglottic airway restores end-expiratory lung volume (EELV) to baseline using electrical impedance tomography.
Methods:
After ethics committee approval (BASEC 2022-01833), we included children (ASA physical status 1-2, 10-20 kg) scheduled for anaesthesia with a supraglottic airway. We performed a recruitment manoeuvre by setting an anaesthesia machine to spontaneous breathing with a 3 L min-1 fresh gas flow (fraction of inspired oxygen [Fio2] 1.0) and the adjustable pressure-limiting (APL) valve set to 30 cmH2O, until a pressure plateau was reached or a leak occurred. Data were collected at three time points: after induction of anaesthesia (baseline), after placement of a supraglottic airway, and after recruitment manoeuvre. The primary endpoint was the normalised change in end-expiratory lung impedance after the recruitment manoeuvre. The global inhomogeneity index was a secondary outcome. Equivalence was assumed if the 95% confidence interval for estimated ΔEELV remained within ±35% (±2 ml kg-1).
Results:
Of the 95 eligible children, we analysed 74 datasets. The median (95% confidence interval) estimated difference in EELV after recruitment manoeuvre vs baseline was -0.9 ml kg-1 (-1.6 to -0.1), within the equivalence margin. No significant changes in global inhomogeneity index (0.0 [0.03-0.04]) were observed.
Conclusions:
In children undergoing general anaesthesia with the use of a supraglottic airway, a recruitment manoeuvre effectively restores EELV to baseline.
Clinical Trial Registration:
NCT05672329.

Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses