Related Experiment Video
Updated: Jan 16, 2026
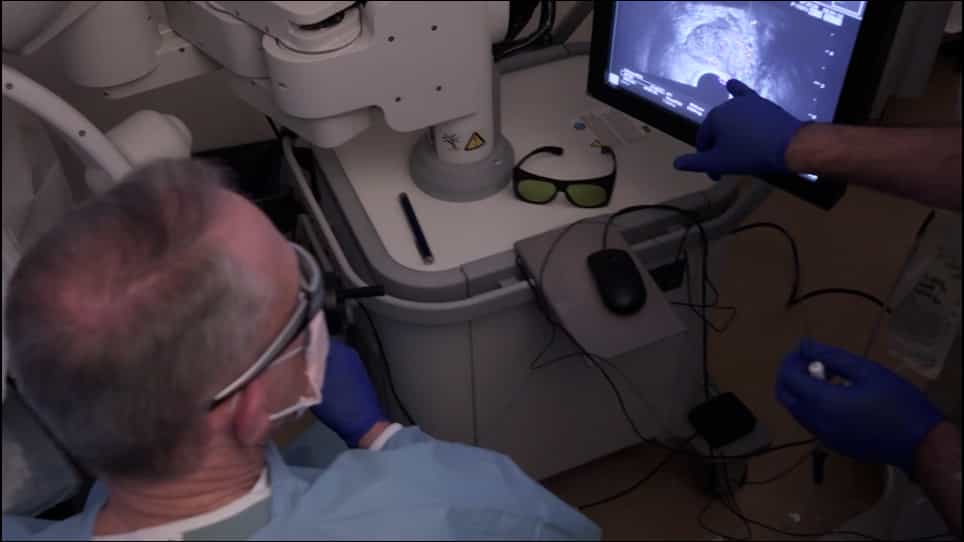

Focal Laser Ablation of Prostate Cancer: An Office Procedure
Published on: March 30, 2021
The Comparative Toxicity of Focal Ablation Versus Intensity Modulated Radiation Therapy for Prostate Cancer
James B Yu1, David M DeStephano2, Brian Jeffers2
1Department of Radiation Oncology, Dartmouth Cancer Center, 1 Medical Center Dr., Lebanon, New Hampshire; Cancer Outcomes, Public Policy, and Effectiveness Research (COPPER) Center at Yale, New Haven, Connecticut.

Purpose:
Focal ablative therapy (FT) aims to treat prostate cancer (PCa) with reduced toxicity compared with standard radiation therapy. There is an absence of studies comparing FT and intensity modulated radiation therapy (IMRT) for PCa.
Methods And Materials:
Using the SEER-Medicare database, we identified fee-for-service Medicare beneficiaries with PCa diagnosed from 2010 to 2017. Patients who underwent IMRT were Mahalanobis matched 2:1 to FT patients based on demographics, Medicaid eligibility, comorbidity, flu vaccination, primary care access, year, cancer characteristics, and androgen-deprivation therapy. We used logistic regression models to assess the relation between treatment modality and the presence of claims indicative of a gastrointestinal or genitourinary complication within 6, 12, and 24 months of treatment.
Results:
We identified 9928 IMRT and 800 FT patients. After matching, patients treated with FT were less likely to have gastrointestinal toxicity (6.2%) within 12 months compared with IMRT patients (9.5%, odds ratio [OR]; 0.63 [95% CI, 0.45-0.88]); results were similar at 24 months (11.0% FT vs 21.5% for IMRT; OR, 0.45 [95% CI, 0.35-0.58]). Most gastrointestinal toxicity was because of diagnoses of rectal bleeding and colitis. In contrast, there were more claims indicative of genitourinary toxicity for FT compared with IMRT during the 0 to 12 (34.6% vs 15.8%; OR, 2.69 [95% CI, 2.21-3.28]) and 0 to 24 (41.7% vs 29.3%; OR, 1.69 [95% CI, 1.42-2.01]) month periods. The largest difference was in incontinence therapy (17.4% vs 7.5%, P < .01) and erectile dysfunction (18.2% vs 13.1%, P < .01), favoring IMRT.
Conclusions:
Among older patients with PCa, FT was associated with a higher risk of incontinence and impotence, than IMRT. There was more colitis and rectal bleeding with IMRT versus FT, but related procedures were rare and not significantly different.


