Related Experiment Video
Updated: Jan 16, 2026


Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Effects of Minimally Invasive Gynecologic Surgery Subspecialty Training on Outcomes of Hysterectomy for Benign
Raanan Meyer1, Rebecca Schneyer1, Kacey Hamilton1
1Division of Minimally Invasive Gynecologic Surgery, Department of Obstetrics and Gynecology, Cedars Sinai Medical Center, Los Angeles, California; The Dr. Pinchas Bornstein Talpiot Medical Leadership Program, Sheba Medical Center, Tel Hashomer, Ramat-Gan, and the Department of Gynecologic Oncology, Hadassah Medical Center, Faculty of Medicine, Hebrew University of Jerusalem, Jerusalem, Israel; and the Lady Davis Institute for Cancer Research, Jewish General Hospital, McGill University, Quebec, Canada.

Objective:
To compare surgical outcomes among patients undergoing hysterectomy for benign indications with minimally invasive gynecologic surgery subspecialists (MIGS group), gynecologic oncologists (GO group), and general obstetrician-gynecologists (OB-GYN group).
Methods:
We conducted a retrospective cohort study from a quaternary care academic hospital. We included patients undergoing hysterectomy for benign reasons from 2015 to 2020. Exclusion criteria were malignant, premalignant, or suspected malignant condition, pelvic mass (other than leiomyoma), concomitant correction of pelvic organ prolapse, and peripartum hysterectomy. The primary outcome was the odds of a composite of any intraoperative or postoperative complications by surgeon group. Secondary outcomes were conversion to laparotomy, estimated blood loss, and admission times by surgeon subspecialty.
Results:
A total of 946 hysterectomies were performed during the study period, of which 356 (37.6%) were performed by obstetrician-gynecologists (ob-gyns), 220 (23.3%) by gynecologic oncologists, and 370 (39.1%) by minimally invasive gynecologic surgeons. Abdominal hysterectomies were performed in 36.8% of cases in the OB-GYN group and 30.0% of cases in the GO group, compared with 0.3% of cases in the MIGS group (P<.001). Intraoperative and postoperative complications occurred in 11.9% of cases in the MIGS group, 18.2% of cases in the GO group (adjusted odds ratio [aOR] 1.79, 95% CI, 1.14-2.08), and 20.8% of cases in the OB-GYN group (aOR 1.64, 95% CI, 1.01-2.69). Conversion to laparotomy occurred in 0.3% of cases in the MIGS group, 7.1% of cases in the GO group, and 7.6% of cases in the OB-GYN group (P<.001). Estimated blood loss, total admission time from surgery to discharge, and total days of hospitalization were all lower in the MIGS group compared with the other two groups (P<.001 for all comparisons). The aOR for same-day discharge was independently lower in the GO group (0.50, 95% CI, 0.29-0.86) and the OB-GYN group (0.23, 95% CI, 0.15-0.33) compared with the MIGS group.
Conclusion:
Fellowship-trained minimally invasive gynecologic surgery subspecialists had lower rates of perioperative complications for hysterectomy for benign indications compared with gynecologic oncologists and ob-gyns. Minimally invasive gynecologic surgery cases were also associated with fewer rates of laparotomy, less blood loss, and shorter hospital stays.
More Related Videos
 05:21
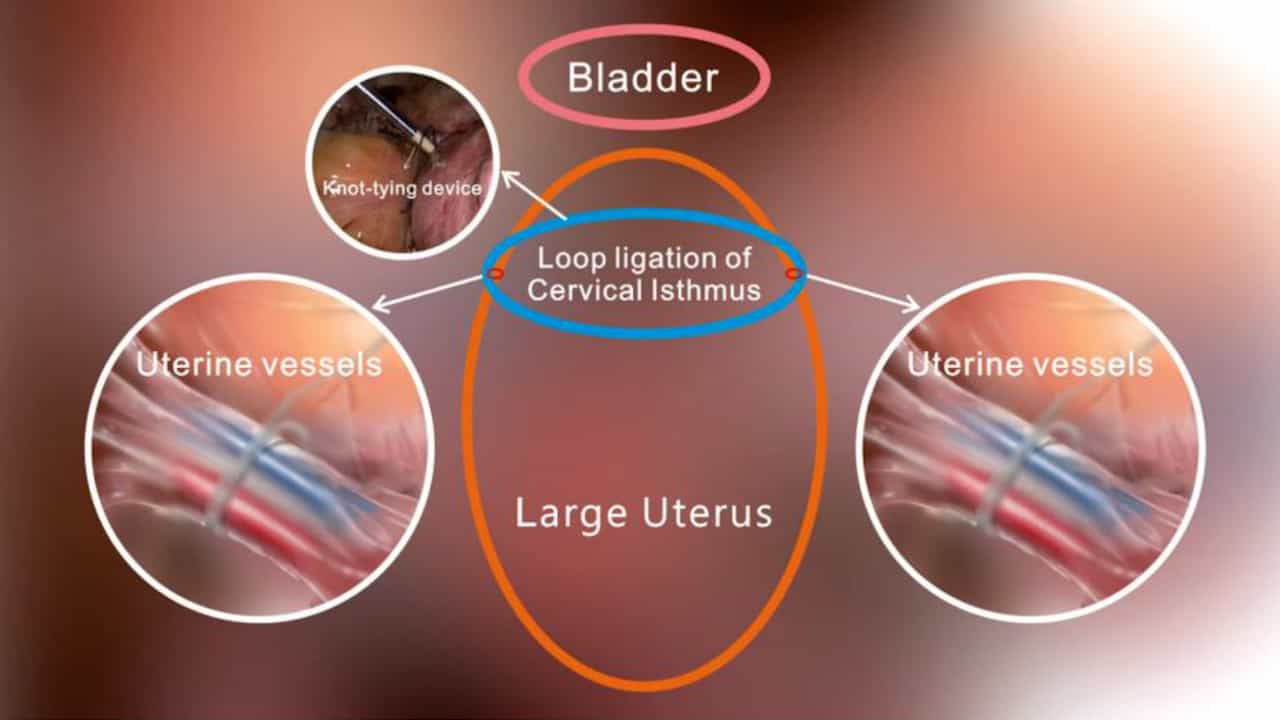
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
 03:01
Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024