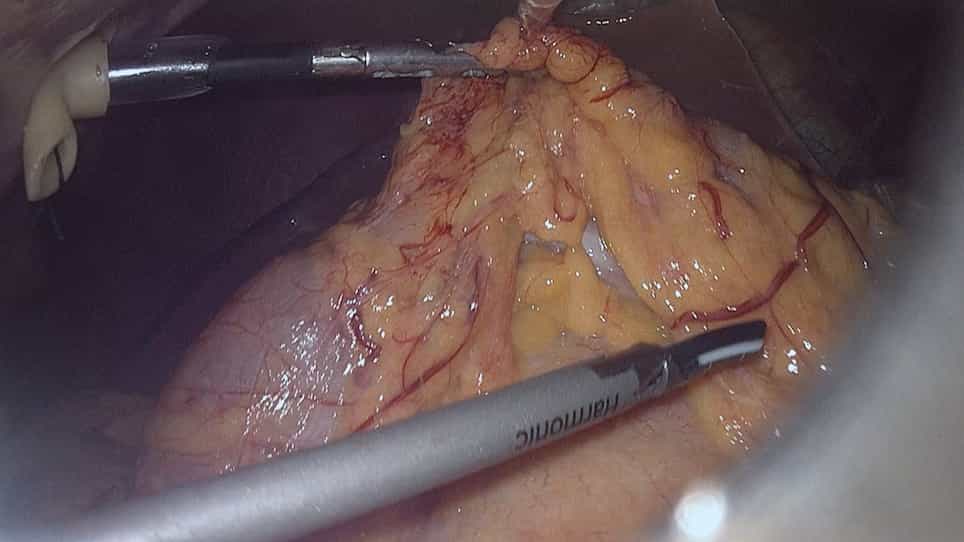
Related Experiment Video
Updated: Jan 16, 2026
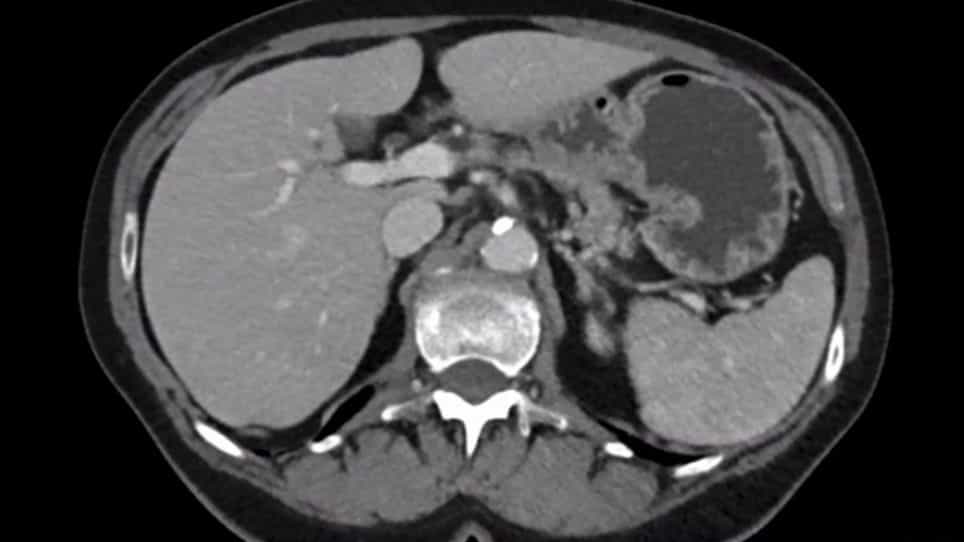

Laparoscopic Radical Left Pancreatectomy for Pancreatic Cancer: Surgical Strategy and Technique Video
Published on: June 6, 2020
Minimally Invasive Distal Pancreatectomy as the Standard of Care in the US: Are We There Yet?
Laleh Foroutani1, Andrew Gonzalez1, Jaeyun Jane Wang1
1Department of Surgery, University of California San Francisco, San Francisco, CA 94143, USA.

Introduction:
While there is an increasing shift towards minimally invasive distal pancreatectomy (MIDP), little is known about how utilization of MIDP vs. open distal pancreatectomy (ODP) has evolved over time. We aimed to determine competing temporal trends in use and outcomes of MIDP (laparoscopic and robotic) over time and to determine if a threshold of effectiveness has been reached.
Methods:
Adults undergoing MIDP and ODP were identified from the National Cancer Database (2010-2021) and the National Surgical Quality Improvement Program database (2014-2022). Propensity score matching (PSM) was performed to address baseline differences between groups before comparing outcomes. Joinpoint regression analysis (JRA) was employed to assess adjusted trends in adoption and outcomes. We calculated Annual Percentage Change (APC) and Average Annual Percentage Change (AAPC) to quantify yearly adoption rates and their trends, respectively.
Results:
Among 21,966 patients in the NCDB cohort, 49.5% underwent MIDP, including 33.7% laparoscopic distal pancreatectomy (LDP) and 15.8% robotic distal pancreatectomy (RDP), while 50.5% underwent ODP. ODP declined from 74.1% of cases (2010) to 41.1% (2021), with an AAPC of -4.9%. MIDP increased significantly throughout the study from 25.9% of cases (2010) to 58.9% (2021), with an AAPC of 6.3%. Among MIDP subgroups, there was an initial increase in LDP until 2016, after which its rate of utilization stagnated with an AAPC of 0.7% (p > 0.05). In contrast, RDP demonstrated steady growth with an AAPC of about 15% (p < 0.05). A consistent and significant decline in clinically relevant postoperative pancreatic fistula rates occurred across all surgical approaches, with the most pronounced improvement observed in the robotic approach. MIDP approaches had significantly shorter hospital stays and lower mortality rates; however, RDP cases were associated with longer operative times compared to LDP and ODP.
Conclusions:
Over the past decade, the use of MIDP increased while ODP decreased. This increase was initially driven by greater use of LDP, which plateaued after 2016, and was further driven by the increased use of the robotic approach. Specifically, RDP demonstrated consistent growth, while LDP showed a decline around 2016. These findings highlight changing practice patterns, accompanied by improvements across all surgical approaches. This may provide insights for clinical training and resource allocation.
Insights
Minimally invasive distal pancreatectomy (MIDP) use increased significantly, driven by robotic approaches, while open distal pancreatectomy (ODP) declined. Outcomes improved across all methods, with robotic procedures showing the most significant gains in reducing pancreatic fistula rates.
Area of Science:
- Surgical Oncology
- Minimally Invasive Surgery
- Pancreatic Surgery
Background:
- The adoption of minimally invasive distal pancreatectomy (MIDP) is rising, but its comparative evolution against open distal pancreatectomy (ODP) remains unclear.
- Understanding temporal trends in MIDP versus ODP utilization is crucial for assessing surgical practice evolution.
Purpose of the Study:
- To analyze the changing utilization trends of MIDP (laparoscopic and robotic) compared to ODP over time.
- To evaluate the effectiveness and outcomes associated with MIDP and ODP, determining if a threshold of efficacy has been met.
Main Methods:
- Utilized data from the National Cancer Database (2010-2021) and the National Surgical Quality Improvement Program (2014-2022) for adult patients undergoing distal pancreatectomy.
- Employed propensity score matching (PSM) to control for baseline differences and Joinpoint Regression Analysis (JRA) to assess temporal trends in adoption and outcomes.
- Calculated Annual Percentage Change (APC) and Average Annual Percentage Change (AAPC) to quantify adoption rates and trends.
Main Results:
- MIDP utilization rose from 25.9% to 58.9% (AAPC 6.3%), while ODP decreased from 74.1% to 41.1% (AAPC -4.9%).
- Laparoscopic distal pancreatectomy (LDP) use plateaued after 2016 (AAPC 0.7%), whereas robotic distal pancreatectomy (RDP) showed consistent growth (AAPC ~15%).
- All approaches demonstrated reduced pancreatic fistula rates, with the most significant improvement in RDP. MIDP was associated with shorter hospital stays and lower mortality, though RDP had longer operative times.
Conclusions:
- The shift towards MIDP is accelerating, initially propelled by LDP but increasingly driven by RDP's steady growth.
- Significant improvements in postoperative pancreatic fistula rates were observed across all surgical methods, particularly with robotic approaches.
- These evolving trends in utilization and outcomes offer valuable insights for surgical training and resource allocation in pancreatic surgery.