Related Experiment Video
Updated: Jan 16, 2026
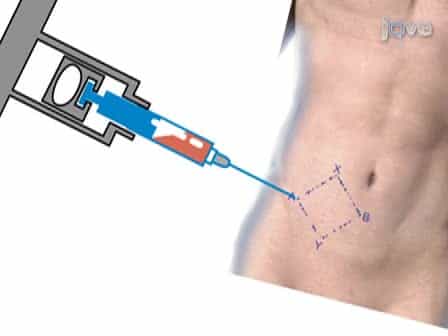

Performing and Processing FNA of Anterior Fat Pad for Amyloid
Published on: October 30, 2010
What Cardiologists Should Know About Amyloidosis
Rama Alashqar1, Ahmad Alkhatib2, Ala W Abdallah3
1Washington Hospital Center Program, MedStar Health, Georgetown University, Washington, DC 20010, USA.

Insights
Early recognition and accurate diagnosis of cardiac amyloidosis (CA) are crucial for improving patient outcomes. This review emphasizes a structured, biomarker- and imaging-guided approach for cardiologists to manage this complex condition.
Area of Science:
- Cardiology
- Cardiovascular Medicine
- Amyloidosis Research
Background:
- Cardiac amyloidosis (CA) is an underdiagnosed cause of heart failure with preserved ejection fraction (HFpEF).
- Caused by extracellular deposition of misfolded proteins (ATTR or AL), leading to myocardial dysfunction.
- Often presents as restrictive cardiomyopathy with potential multi-organ involvement.
Purpose of the Study:
- Provide a cardiology-focused review of cardiac amyloidosis.
- Emphasize early recognition, diagnostic strategies, and subtype differentiation.
- Discuss evolving and emerging therapies for ATTR and AL amyloidosis.
Main Methods:
- Review of epidemiology, pathophysiology, and clinical manifestations of ATTR and AL CA.
- Evaluation of key diagnostic tools: echocardiography, cardiac MRI, bone scintigraphy, protein screening, biopsy.
- Analysis of clinical presentation, ECG/imaging "red flags," and differentiation from mimics like HCM.
Main Results:
- Detailed review of diagnostic tools and a stepwise approach.
- Highlighting prognostic significance of staging systems and cardiac biomarkers.
- Exploration of subtype-specific therapies (daratumumab, tafamidis, gene silencers) and novel treatments (CRISPR).
Conclusions:
- Timely recognition and accurate diagnosis of CA are critical for improved outcomes.
- Cardiologists must lead multidisciplinary care amidst rapidly evolving diagnostics and therapeutics.
- A structured, biomarker- and imaging-guided approach enhances diagnosis, prognosis, and patient management.
Abstract:
Background: Cardiac amyloidosis (CA) is an increasingly recognized but historically underdiagnosed cause of restrictive cardiomyopathy and heart failure with preserved ejection fraction (HFpEF). It results from the extracellular deposition of misfolded protein fibrils, most commonly transthyretin (ATTR) or immunoglobulin light chains (AL), leading to progressive myocardial dysfunction and multi-organ involvement. Objective: This review provides a comprehensive, cardiology-centered overview of cardiac amyloidosis, with an emphasis on early recognition, diagnostic strategies, subtype differentiation, and the evolving therapies. Content: We summarize the epidemiology, pathophysiology, and clinical manifestations of both ATTR and AL subtypes. Key diagnostic tools, including echocardiography, cardiac magnetic resonance imaging, bone scintigraphy, monoclonal protein screening, and endomyocardial biopsy, are reviewed in the context of a stepwise diagnostic approach. Special attention is given to clinical presentation, electrocardiographic and imaging "red flags," and to differentiating CA from mimickers such as hypertrophic cardiomyopathy, hypertension-induced left ventricular hypertrophy, and aortic stenosis. Staging systems are detailed, highlighting the prognostic role of cardiac biomarkers. Therapeutic strategies are explored, including subtype-specific regimens (e.g., daratumumab-based therapy for AL; tafamidis and gene silencers for ATTR), the judicious use of conventional heart failure medications, and emerging therapies such as CRISPR-based gene editing. Conclusions: Timely recognition and accurate diagnosis of cardiac amyloidosis are critical to improving outcomes. As diagnostic tools and disease-modifying therapies evolve rapidly, cardiologists must remain at the forefront of multidisciplinary care. A structured biomarker- and imaging-guided approach can enhance diagnostic yield, inform prognosis, and optimize patient-specific management.
More Related Videos

Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 03:03
Amyloid Fibrils
03:03Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining,...