Related Experiment Video
Updated: Jan 16, 2026
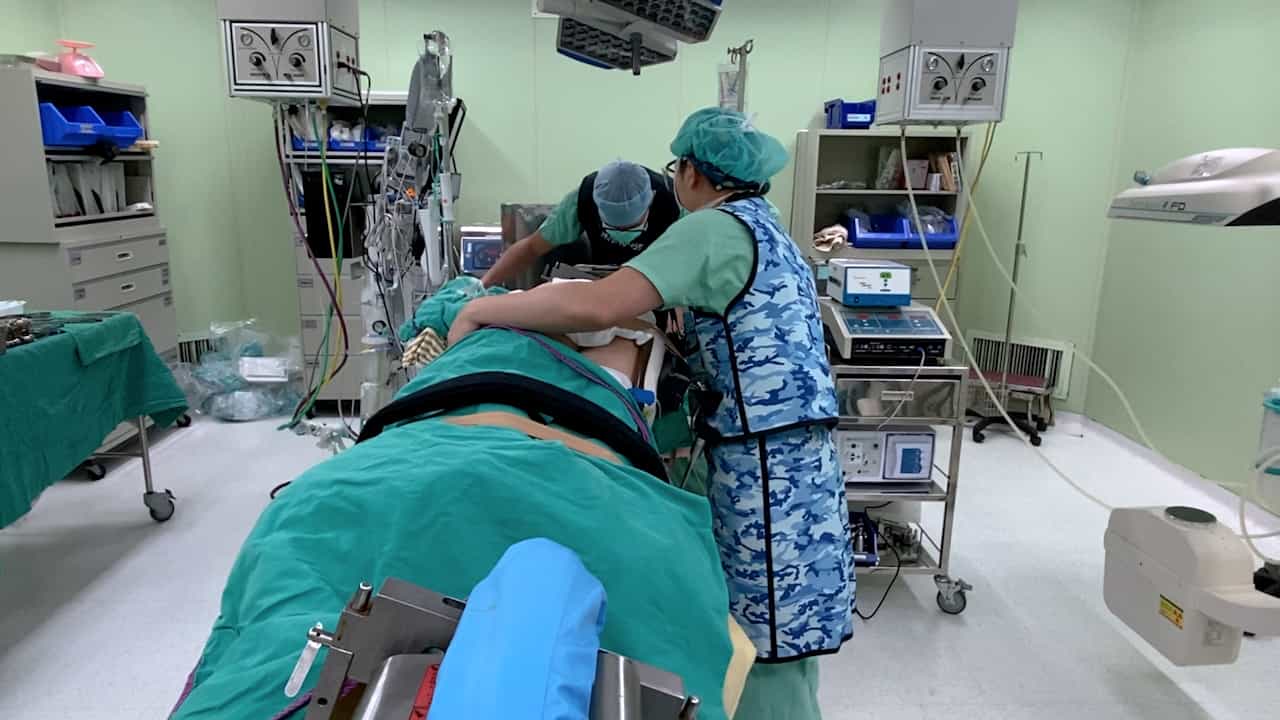

Prone Lateral Minimally Invasive Retropleural Corpectomy Using a Rotatable Radiolucent Jackson Table
Published on: July 3, 2025
[Application of 30° reverse trendelenburg combined with semi-prone position in single-port thoracoscopic surgery for
1Department of Thoracic Surgery, the First Affiliated Hospital of Zhengzhou University, Zhengzhou 450052, China.

Abstract:
Objective: To investigate the feasibility and advantages of 30°reverse trendelenburg combined with semi-prone position in single-port thoracoscopic surgery for lung cancer. Methods: This study is a prospective, randomized controlled trial. Between October 2022 and December 2023, patients with lung cancer who met the inclusion and exclusion criteria were prospectively enrolled at the Department of Thoracic Surgery, the First Affiliated Hospital of Zhengzhou University,and randomized using a simple randomization design to generate a random number table. Patients were allocated in a 1∶1 ratio to either the modified positioning group (30°reverse trendelenburg combined with semi-prone position) or the conventional positioning group (lateral decubitus position). Comparative analysis was performed on feasibility metrics including operative time, postoperative pain scores, surgeon and assistant fatigue levels, number of lymph nodes dissected, duration of postoperative chest tube drainage, and postoperative hospital stay. Inter-group comparisons were conducted using independent sample t-tests, χ2 tests or Kruskal-Wallis. Results: A total of 211 patients were included.The modified positioning group comprised 105 patients (58 males, 47 females) with an age of (56.2±10.3)years (range: 23 to 74 years). The conventional positioning group included 106 patients (55 males, 51 females) with an age of (57.8±11.7)years (range: 21 to 76 years). All patients underwent successful single-port thoracoscopic lung cancer surgery without severe perioperative complications. No statistically significant differences were observed between groups in operative time ((98±34) minutes vs. (114±36) minutes, t=-1.642, P=0.221), number of lymph nodes dissected (13.4±2.5 vs. 12.8±3.2, t=0.702, P=0.763), postoperative chest tube duration ((4.3±1.5) days vs. (5.1±1.8) days, t=-1.348, P=0.247), or postoperative hospital stay ((5.0±1.2) days vs. (5.6±1.5) days, t=-0.831, P=0.682). The modified positioning group demonstrated significantly lower postoperative day 1 pain scores on the visual analog scale (3.1±2.0 vs. 4.6±1.9, t=-4.321, P=0.027) and postoperative surgeon-reported fatigue scores (primary surgeon: 13.6±2.5 vs. 18.5±3.3, t=-6.963, P=0.002; assistant surgeon: 12.1±2.0 vs. 17.1±3.1, t=-6.133, P=0.003) compared with the conventional group, with all differences reaching statistical significance. Conclusions: The application of 30°reverse trendelenburg combined with semi-prone position during single-port thoracoscopic lung cancer surgery is both safe and feasible. Compared with the conventional lateral decubitus position, this modified positioning demonstrates significant advantages in reducing postoperative pain and alleviating surgical team fatigue (including both primary and assistant surgeons).