Related Experiment Video
Updated: Jul 14, 2026
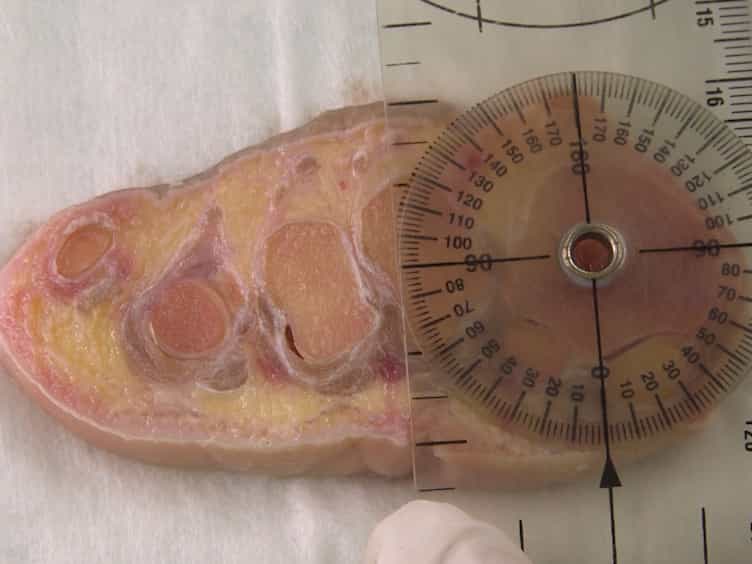

An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Preliminary Anatomical and Surgical Assessment of Combined Percutaneous Resection and Proximal Medial Gastrocnemius
Alessandro Cattolico1, Fabrizio Sergio2, Alessia Boemio1
1Department of Orthopaedics, Azienda Ospedaliera Universitaria "Luigi Vanvitelli", Università degli Studi della Campania" Luigi Vanvitelli" School of Medicine, Naples, Italy.

Insights
This study suggests that combining calcaneal exostosis resection with proximal medial gastrocnemius release (PMGR) may improve outcomes for Haglund syndrome patients. The combined surgical approach showed superior results compared to resection alone, particularly for those with Achilles-plantar complex contracture.
Area of Science:
- Orthopedic surgery
- Foot and ankle surgery
Background:
- Haglund syndrome involves heel pain due to calcaneal exostosis, Achilles tendinopathy, and retrocalcaneal bursitis.
- Surgical intervention is considered when conservative treatments fail.
Purpose of the Study:
- To evaluate the effectiveness of a combined surgical approach for Haglund syndrome.
- To compare outcomes of combined percutaneous resection and proximal medial gastrocnemius release (PMGR) with percutaneous resection alone.
Main Methods:
- A prospective study enrolled 224 patients undergoing combined percutaneous resection and PMGR, divided by Achilles-plantar complex contracture status.
- Outcomes were compared to historical control groups treated with resection only.
- Foot Function Index (FFI) and Victorian Institute of Sport Assessment-Achilles (VISA-A) scores were collected at baseline and 3, 6, and 12 months.
Main Results:
- Both prospective groups (A and B) showed significant improvements in FFI and VISA-A scores at 12 months (P < .001).
- The combined treatment groups demonstrated statistically superior outcomes compared to historical controls who received resection alone (P < .05).
- Comparisons are limited by the nonconcurrent, unmatched study design.
Conclusions:
- Adding Achilles-plantar complex lengthening to percutaneous calcaneal resection may offer benefits for Haglund syndrome.
- The nonrandomized design and historical controls limit causal inference.
- Findings are hypothesis-generating and require validation through randomized controlled trials.
Background:
Haglund syndrome is characterized by heel pain associated with posterosuperior calcaneal exostosis, insertional Achilles tendinopathy, and retrocalcaneal bursitis. When conservative treatments fail, surgical intervention is required. This study aims to evaluate the effectiveness of a combined surgical approach, integrating percutaneous resection of the calcaneal exostosis and proximal medial gastrocnemius release (PMGR) using the Barouk technique in treating Haglund syndrome. The goal is to assess whether this approach offers superior clinical outcomes compared to percutaneous resection alone.
Methods:
We prospectively enrolled 224 patients undergoing combined percutaneous resection and PMGR, divided into group A (n = 106; with Achilles-plantar complex contracture) and group B (n = 118; without contracture) based on passive dorsiflexion testing. Outcomes were compared to 2 historical retrospective control groups treated with resection only: group 1 (n = 124; with contracture) and group 2 (n = 135; without contracture). All prospective patients received the combined treatment regardless of contracture status. Patients with body mass index >30 were excluded. The Foot Function Index (FFI) and Victorian Institute of Sport Assessment-Achilles (VISA-A) Questionnaire scores were collected at baseline and 3, 6, and 12 months.
Results:
Groups A and B improved a mean 30 ± 5 FFI points and 40 ± 7 VISA-A points at 12 months (both P < .001). When compared to historical controls who underwent resection alone, the combined treatment groups showed statistically superior outcomes at all follow-up intervals (P < .05). However, these comparisons are limited by the nonconcurrent, unmatched study design.
Conclusion:
This mixed prospective-retrospective study suggests potential benefits of adding Achilles-plantar complex lengthening to percutaneous calcaneal resection. However, the nonrandomized design, historical controls, and lack of patient/outcome assessor masking significantly limit causal inference. Although the combined approach showed statistically superior outcomes compared with historical controls, these findings should be considered hypothesis-generating pending validation in randomized controlled trials.
Level Of Evidence:
Level III, retrospective-comparative cohort.
More Related Videos
 09:01
Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
