Related Experiment Video
Updated: Jan 16, 2026
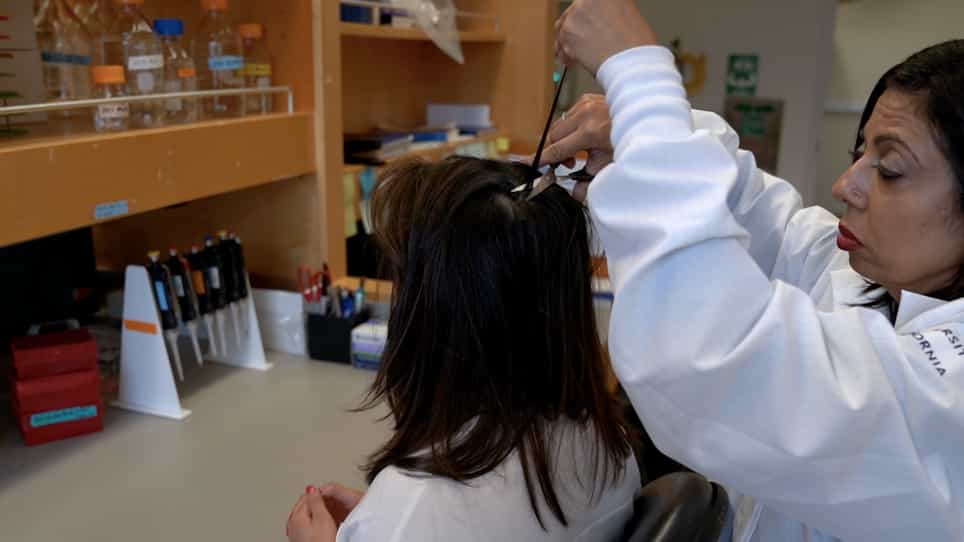

Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Rates and Risk Factors for On-Treatment Mortality Among a Cohort of Adults Treated for Drug-Sensitive Tuberculosis:
Amare W Tadesse1, Noriah Maraba2, Jason Alacapa3
1Department of Infectious Disease Epidemiology and International Health, London School of Hygiene & Tropical Medicine (LSHTM), London, UK.

Background:
Tuberculosis remains a leading cause of death globally, particularly in countries with high tuberculosis and HIV burdens. Disruptions caused by the COVID-19 pandemic may have further impacted tuberculosis outcomes. This study examines on-treatment mortality and associated risk factors in five countries.
Method:
We conducted a secondary analysis of data from ASCENT cluster-randomised trials of digital adherence tools for improved adherence involving 23,799 adults with drug-sensitive tuberculosis in South Africa, Tanzania, Ethiopia, the Philippines, and Ukraine. Analyses were conducted separately by country. Mortality rates were measured from treatment initiation to the earliest of 6 months, death, or loss to follow-up. Cox regression models (with random effects or robust standard errors for clustering) assessed the associations between mortality and HIV status, ART use, tuberculosis diagnosis type, and calendar periods (COVID-19 pandemic and conflict in Ukraine).
Results:
Mortality rates ranged from 7.6 (Ethiopia) to 23.2 (Tanzania) and 23.3 (Ukraine) per 100 person-years. Higher mortality was associated with: older age in all countries (age < 30 versus ≥ 60 years, adjusted rate ratio [aRR] ranging from 2.38 to 6.57 by country); HIV status (positive versus negative, aRR ranging from 1.44 to 2.98 by country); tuberculosis diagnosis type (clinical vs. bacteriological, aRR 1.5-1.6 in Ethiopia, Tanzania and South Africa); extrapulmonary tuberculosis (aRR 1.44 to 1.60 in Ukraine and Tanzania). ART versus HIV-positive not on ART was linked to lower mortality in South Africa and Ukraine but not in Tanzania. Analyses suggested possible mortality variations by calendar period.
Conclusion:
Our findings suggest variability in tuberculosis mortality across settings, influenced by HIV/ART and diagnosis type. The high mortality rates across countries may reflect underlying causes or potential misdiagnoses. Further investigation into these factors may be needed to improve tuberculosis outcomes globally.
More Related Videos
 10:04
Analysis of 18FDG PET/CT Imaging as a Tool for Studying Mycobacterium tuberculosis Infection and Treatment in Non-human Primates
Published on: September 5, 2017
 09:34
An Automated Culture System for Use in Preclinical Testing of Host-Directed Therapies for Tuberculosis
Published on: August 16, 2021
Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...