Related Experiment Video
Updated: Jan 16, 2026

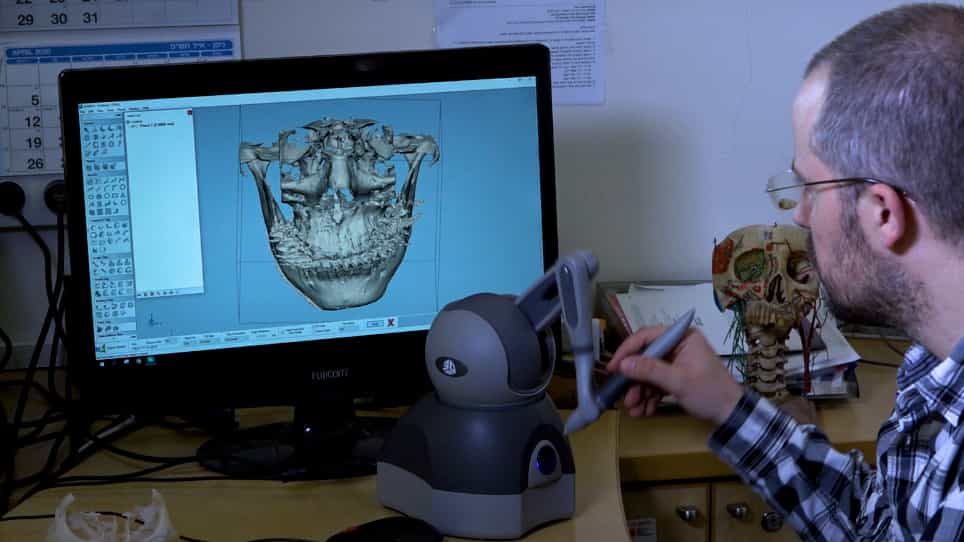
3D Planning and Printing of Patient Specific Implants for Reconstruction of Bony Defects
Published on: August 4, 2020
Rates and Determinants of Prosthodontic Rehabilitation After Segmental Jaw Surgery
Amal Idrissi Janati1, Ameena Nizar Beema2, Jordan Gigliotti3
1Assistant Professor, Faculty of Dental Medicine and Oral Health Sciences, McGill University, Montreal, Quebec, Canada; Research Director, Department of Dentistry and Oral and Maxillofacial Surgery, Montreal General Hospital, Montreal, Quebec, Canada.

Background:
Management of maxillofacial pathologies often requires ablative surgeries of the jaw which may include the tooth-bearing segment resulting in loss of oral function. Advances in maxillomandibular reconstruction with vascularized free flaps (VFFs) and dental implants have enabled prosthodontic rehabilitation (PR) in most patients. However, the impact of these advancements on rates and barriers of PR remains unclear.
Purpose:
The purpose of this study was to estimate the rate of PR and identify risk factors associated with failure to achieve PR.
Study Design, Setting, Sample:
This 7-year retrospective cohort study was conducted at the Montreal General Hospital and included patients aged ≥15 years who underwent vascularized free flap reconstruction following jaw segmental resection between 2015 and 2021.
Predictor Variable:
Predictor variables included age, sex, smoking, clinical diagnosis, adjuvant radiotherapy, flap type, and anterior tooth loss.
Main Outcome Variable(S):
The primary outcome is time to PR and secondary outcomes were PR status (not performed vs performed) and PR type (conventional vs implant-supported) respectively.
Covariates:
NA.
Analyses:
Descriptive statistics, comparison tests, Kaplan-Meier analysis, and univariate and multivariate Cox and logistic regression analyses were conducted (P < .05).
Results:
The study included 184 subjects with a mean age of 58 years (SD = 17), and 52% (n = 95) were men. The median follow-up was 20 months (interquartile range = 32). Malignancy was the most common diagnosis leading to surgery (n = 106; 58%), followed by benign tumors (n = 46; 25%). Cumulative proportion of PR was 41% (n = 76), including 19.5% (n = 36) of implant-supported prostheses. Median time to start PR was 44 months (95% CI: 30 to 78) and was significantly delayed in men, ever smokers, cancer patients, and those who received radiotherapy. In multivariate analysis, radiotherapy was the main predictor of failure to receive PR overall (P = .014) and implant-supported PR specifically (P = .025).
Conclusion And Relevance:
Many patients with dental morbidity after segmental jaw surgery, especially cancer patients requiring radiotherapy, did not receive PR, and even fewer received implant-supported prostheses, highlighting the need for preradiotherapy solutions.