Related Experiment Video
Updated: Jan 16, 2026

Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
When Trimethoprim-Sulfamethoxazole Turns Pernicious: Type 4 Renal Tubular Acidosis in a Diabetic Patient With
Öykü Zeynep Gerçek1, Birkan Alaycı1, Fatih Borlu2
1Internal Medicine, Şişli Hamidiye Etfal Training and Research Hospital, Istanbul, TUR.

Abstract:
Type 4 renal tubular acidosis (RTA) is an underrecognized but potentially life-threatening complication characterized by hyperkalemic, non-anion gap metabolic acidosis. Trimethoprim-sulfamethoxazole (TMP-SMX), commonly used for treating Pneumocystis jirovecii pneumonia (PCP), has been implicated as a reversible trigger of this condition, especially in metabolically vulnerable patients. We report the case of a 63-year-old woman with type 2 diabetes mellitus and Sjögren's syndrome who developed type 4 RTA during intravenous TMP-SMX therapy for PCP. Although initial arterial blood gas (ABG) analysis showed a near-normal pH, further evaluation revealed decreased serum bicarbonate (HCO₃⁻) and a partial pressure of carbon dioxide (PaCO₂) lower than expected by Winter's formula, consistent with a mixed acid-base disorder. Hyperkalemia and a positive urine anion gap confirmed the diagnosis of type 4 RTA. Distal (type 1) RTA, commonly associated with Sjögren's syndrome, was ruled out based on urine pH and potassium status. TMP-SMX was continued with close monitoring, and the acid-base abnormalities resolved following treatment completion. This case underscores the importance of considering medication-induced type 4 RTA in immunocompromised patients presenting with unexplained hyperkalemia and normal anion gap metabolic acidosis. TMP-SMX, although widely used and effective, necessitates vigilant electrolyte monitoring in susceptible individuals.
More Related Videos

Related Concept Videos
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:29
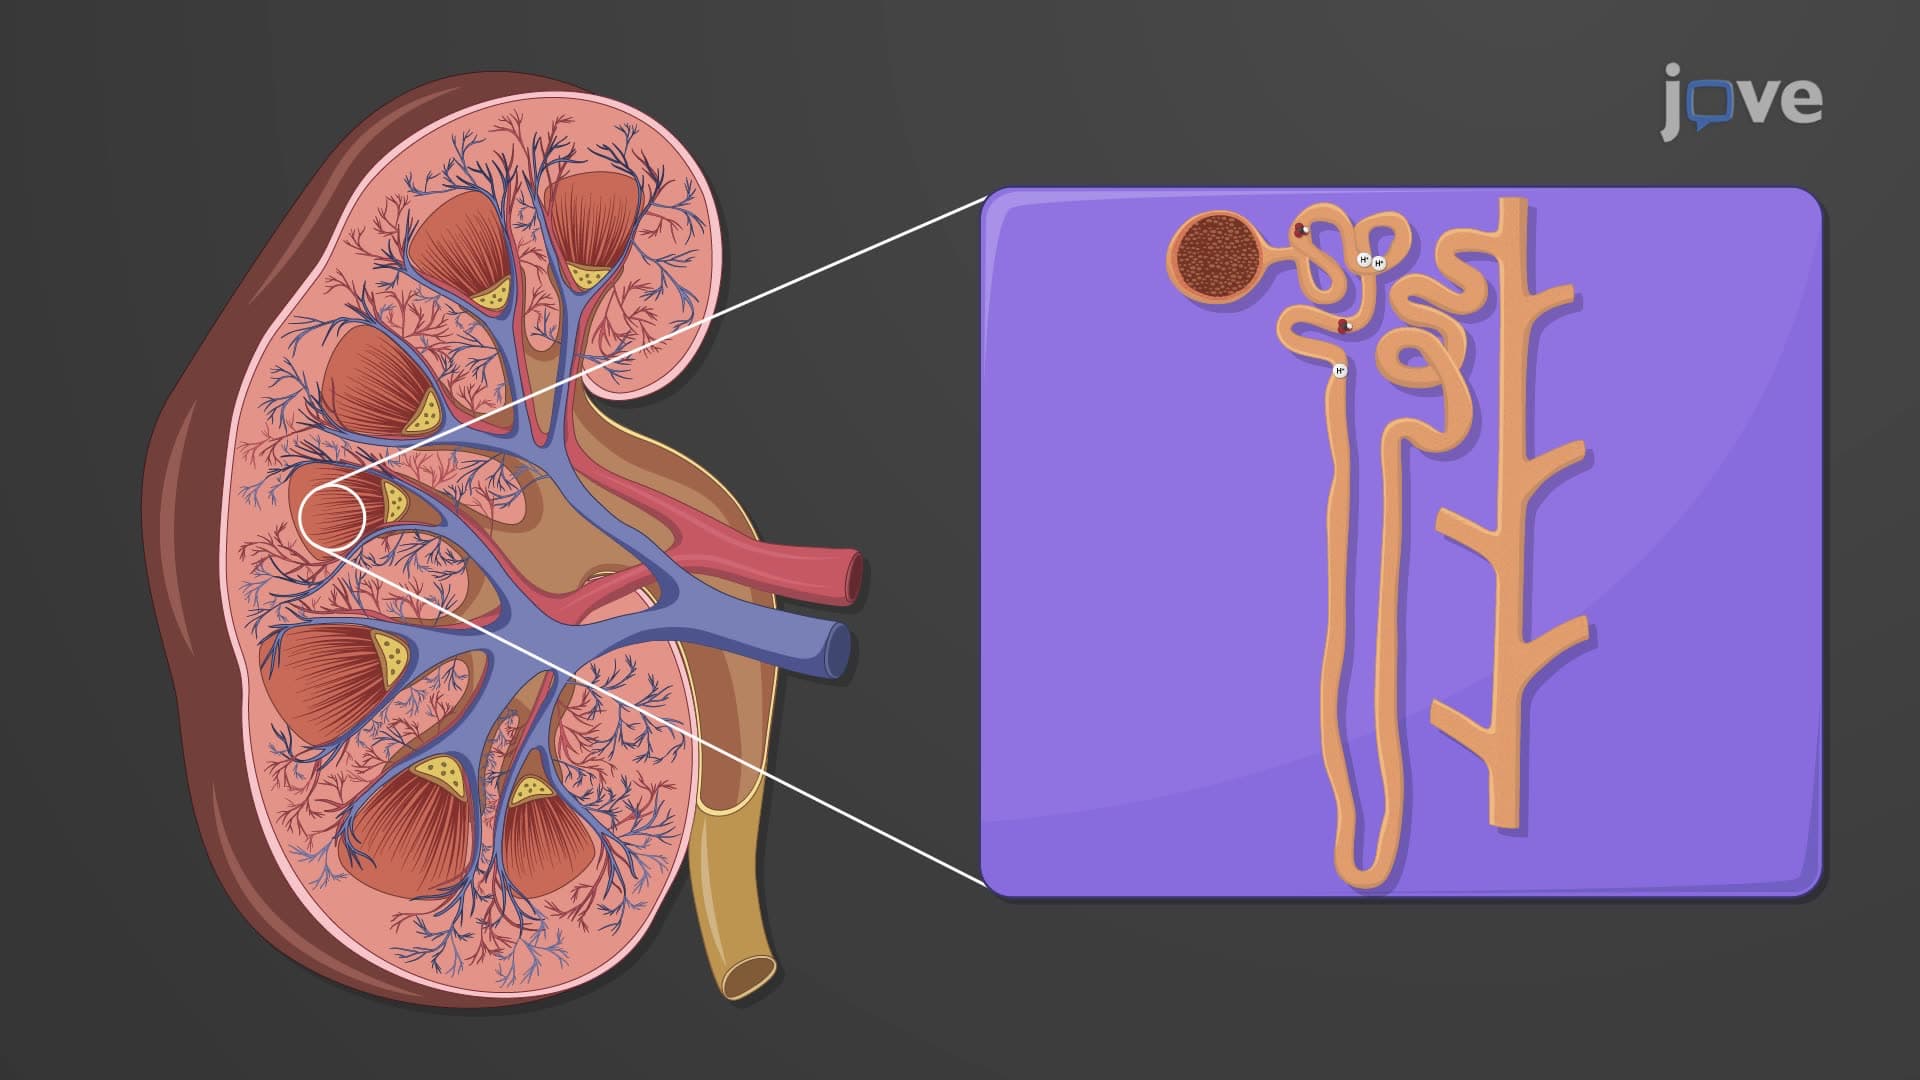
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Nephrotic Syndrome I : Introduction
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes: