Related Experiment Video
Updated: Jan 6, 2026


Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
Tidal volume and mortality during extracorporeal membrane oxygenation for acute respiratory distress syndrome: a
Torben M Rixecker1, Jeannine L Kühnle2, Johannes Herrmann3
1Department of Internal Medicine V (Pneumology, Allergology and Intensive Care Medicine), Saarland University, Kirrberger Str. 100, 66421, Homburg, Germany. torben.rixecker@uks.eu.

Background:
Approximately half of the patients with acute respiratory distress syndrome (ARDS) receiving extracorporeal membrane oxygenation (ECMO) remain ECMO-dependent beyond 14 days after ECMO initiation. The identification of factors associated with mortality during an ECMO run may update prognostic assessment and focus clinical interventions.
Methods:
In this observational study, data from 1137 patients with COVID-19 ARDS receiving ECMO support in 29 German centers between January 1st 2020 and July 31st 2021 were analyzed. Multivariable stepwise logistic regression analyses were performed to build survival prediction models with day-by-day data during the first 14 days of an ECMO run. The primary endpoint was all-cause mortality in the intensive care unit.
Results:
Mortality in this cohort was high (75%). Patients who remained ECMO-dependent on day 14 of their ECMO run showed comparable mortality to all patients receiving ECMO support on day 1. Yet, factors associated with mortality changed during the first 14 days of ECMO support. On day 1 of ECMO support, only patient age and lactate remained in the final mortality prediction model. On day 14 of an ECMO run, tidal volume was independently associated with mortality (adjusted Odds Ratio 0.693 (95%CI 0.564-0.851), p < 0.001 for 1 mL/kg increase in tidal volume per predicted body weight). The adjusted mortality for patients with a tidal volume below 2 mL/kg on day 14 of their ECMO run was above 80% (lower limit of the 95%CI interval). Higher tidal volume was mainly based on higher respiratory system compliance. Yet, the benefit of higher compliance was not observed in some patients who were still ventilated with very low driving pressures despite remaining ECMO-dependent on day 14 of ECMO support.
Conclusions:
Mortality predictors change during the course of an ECMO run. In a cohort with high mortality, on day 14 of ECMO support for ARDS, tidal volume may be an independent predictor of mortality. Further analyses on ventilation strategies in patients who remain ECMO-dependent are needed.
Trial Registration Number:
DRKS00022964, retrospectively registered.

Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Acute Respiratory Failure-III
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:15
Respiratory Volumes
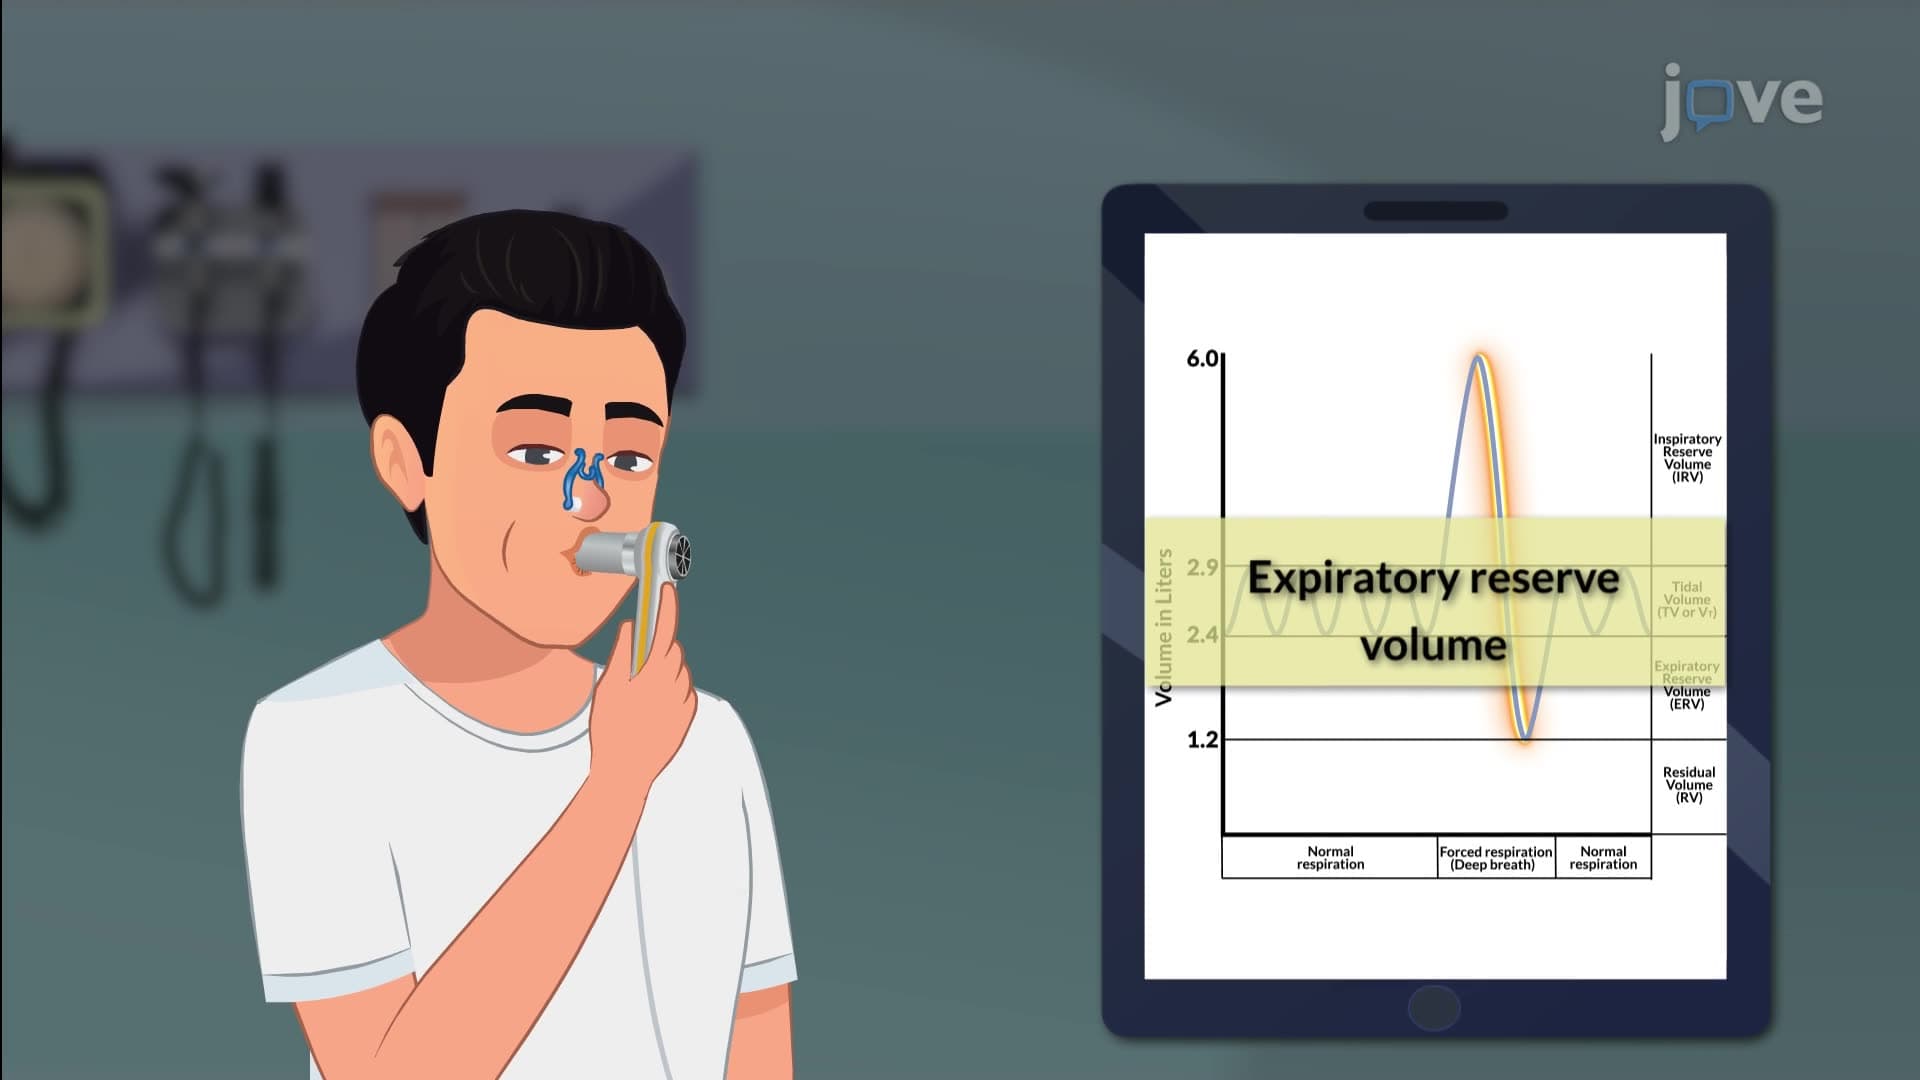
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...