Related Experiment Video
Updated: Jan 6, 2026
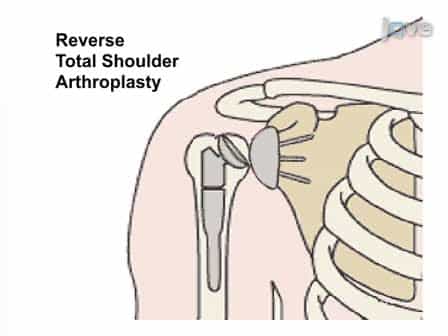

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Heart failure patients demonstrate excellent 1-year outcomes after total knee arthroplasty despite high healthcare
Nickelas Huffman1, Abizairie Sánchez-Feliciano2, Khaled A Elmenawi1
1Cleveland Clinic, Department of Orthopedic Surgery, Cleveland, OH, USA.

Insights
Heart failure patients undergoing total knee arthroplasty (TKA) experience higher healthcare use but achieve similar pain and function improvements as non-heart failure patients. Heart failure severity does not impact these outcomes, suggesting tailored risk stratification may not be needed.
Area of Science:
- Orthopedic Surgery
- Cardiology
- Health Services Research
Background:
- Total knee arthroplasty (TKA) is frequently performed in patients with heart failure (HF).
- Postoperative outcomes and healthcare resource utilization in these patients are not well-defined.
- Understanding these outcomes is crucial for optimizing perioperative care.
Purpose of the Study:
- To compare healthcare resource utilization and patient-reported outcome measures (PROMs) after TKA between patients with and without HF.
- To analyze outcomes based on HF severity, specifically ejection fraction (EF) categories.
Main Methods:
- Retrospective analysis of 12,491 TKA patients (2016-2021), including 495 with HF.
- HF patients categorized by EF: preserved (≥50%), mildly reduced (41-49%), and reduced (≤40%).
- Comparison of healthcare utilization metrics, 1-year mortality, and PROMs (KOOS-Pain, KOOS-PS, KOOS-JR) using MCID and PASS thresholds.
Main Results:
- HF patients showed significantly higher odds of prolonged hospital stay, non-home discharge, 90-day readmission, 90-day ED visits, and 1-year mortality.
- One-year PROMs were similar between HF and non-HF groups; HF patients were more likely to achieve MCID for KOOS-PS.
- Mildly reduced EF subgroup reported higher 1-year KOOS-Pain and achieved PASS for pain; EF did not predict 1-year outcomes.
Conclusions:
- Despite increased healthcare utilization, HF patients achieve comparable functional and pain improvements after TKA.
- HF severity (EF) did not correlate with differential healthcare utilization or outcomes, questioning the need for HF-specific risk stratification.
- Further research may explore specific interventions to mitigate increased resource use in HF patients undergoing TKA.
Purpose:
Many heart failure (HF) patients undergo total knee arthroplasty (TKA), but their postoperative outcomes remain unclear. This study aimed to compare healthcare resource utilization and patient-reported outcome measures (PROMs) after TKA between patients with and without HF.
Methods:
A retrospective analysis of 12,491 TKA at our institution from 2016 to 2021, including 495 with HF. HF patients were stratified into three ejection fraction (EF) categories: preserved (≥ 50%, n = 374), mildly reduced (41-49%, n = 53), and reduced (≤ 40%, n = 68). Healthcare utilization metrics and 1-year mortality were compared. PROMs were assessed using the Knee Injury and Osteoarthritis Outcome Score for Pain (KOOS-Pain), Physical Function Shortform (KOOS-PS), and Joint Replacement (KOOS-JR) at baseline and 1-year postoperatively. Minimal clinically important difference (MCID) and patient-acceptable symptom state (PASS) thresholds were evaluated.
Results:
HF patients had significantly higher odds of prolonged hospital stay (OR 2.55, p < 0.001), non-home discharge (OR 2.17, p < 0.001), 90-day readmission (OR 2.02, p < 0.001), 90-day emergency department visits (OR 1.55, p = 0.002), and 1-year mortality (OR 3.53, p = 0.007). PROMs were similar between HF and non-HF patients at 1 year, though HF patients were more likely to achieve MCID for KOOS-PS (p = 0.021). Among EF subgroups, patients with mildly reduced EF had significantly higher 1-year KOOS-Pain (p = 0.024) and PASS achievement for pain (p = 0.043). EF did not predict 1-year outcomes.
Conclusion:
Despite increased healthcare utilization, HF patients undergoing TKA achieve similar improvements in pain and functionality as non-HF patients. HF severity was not associated with differential healthcare utilization, suggesting that risk stratification based on HF severity may not be necessary. Level of evidence III.


Related Concept Videos
 01:30
Heart Failure V: Medical Management
 01:21
Rheumatic Heart Disease III: Medical Management
 01:29
Heart Failure II: Pathophysiology
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:20
Rheumatic Heart Disease IV: Nursing Management
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management