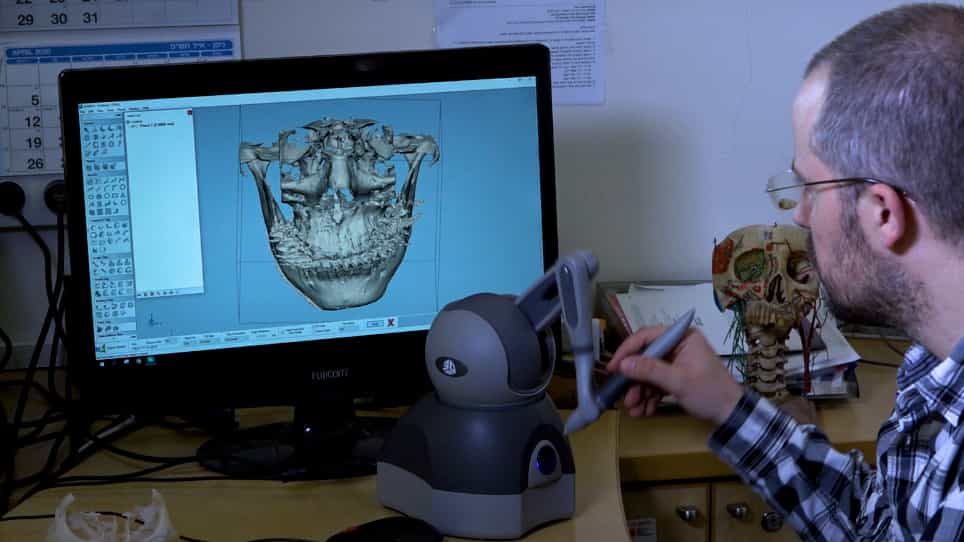
Related Experiment Video
Updated: Jul 19, 2026


A Postoperative Evaluation Guideline for Computer-Assisted Reconstruction of the Mandible
Published on: January 28, 2020
Management of the pterygoid plate in orthognathic surgery: a narrative review
Ji Young Hwang1, Dae Seok Hwang2,3, Borim Choi4
1Department of Oral and Maxillofacial Surgery, School of Dentistry, Pusan National University, Yangsan, Republic of Korea. hwangjy16@gmail.com.

Background:
The most critical factor for successfully performing setback and superior/posterior impaction of the maxilla in orthognathic surgery is securing sufficient space. This space can be achieved through pterygoid plate fracture, removal, or grinding. However, most studies to date have provided limited investigation into the management of the pterygoid process itself.
Main Text:
Safe manipulation of the pterygoid plate demands a precise understanding of the surrounding anatomy. The course of the internal maxillary artery demonstrates substantial anatomical and ethnic variability. In the relationship with the lateral pterygoid muscle, lateral positioning of the artery is more common in Asian populations, and symmetric courses occur more frequently than asymmetric ones. Preservation of the descending palatine artery helps maintain perfusion of the maxilla, although ligation may be indicated in certain situations. The risk of vascular injury increases when the osteotome is placed more than 15 mm superior to the most inferior point of the pterygomaxillary junction. To avoid high-level fractures, the osteotome should be positioned with its lower end at the base of the pterygomaxillary fissure and its tip directed superiorly. These anatomical considerations are essential for selecting the appropriate technique among available options, including fracture, removal, and grinding.
Conclusions:
All three methods of pterygoid plate management-fracture, removal, and grinding-are all effective methods that provide skeletal stability and demonstrate no significant differences in complications including bleeding. Optimal technique selection should be guided by detailed anatomical knowledge, patient-specific factors, and intraoperative findings to maximize surgical safety and effectiveness.