Related Experiment Video
Updated: Jul 23, 2026


Utilizing High Resolution Ultrasound to Monitor Tumor Onset and Growth in Genetically Engineered Pancreatic Cancer Models
Published on: April 7, 2018
Prospective evaluation of pancreaticobiliary maljunction using high-frequency ultrasonography in children
Yuanfang Lai1, Wen Ling1, Luyao Zhou2
1Fujian Maternity and Child Health Hospital, No.18 Daoshan Road, Gulou Districk, Fuzhou, 350000, China.

Insights
High-frequency ultrasonography effectively diagnoses pancreaticobiliary maljunction in children by visualizing the abnormal common channel. Specific ultrasound findings like gallbladder wall thickening and duct dilation are key indicators when junctional anatomy is unclear.
Area of Science:
- Pediatric Gastroenterology
- Diagnostic Imaging
- Hepatobiliary Surgery
Background:
- Ultrasound (US) offers clear visualization of the pancreaticobiliary junction.
- Limited pediatric studies exist on US for diagnosing pancreaticobiliary maljunction.
Purpose of the Study:
- To prospectively evaluate the diagnostic value of high-frequency ultrasonography for pancreaticobiliary maljunction in pediatric patients.
- To assess the efficacy of specific ultrasound characteristics in diagnosing this condition.
Main Methods:
- High-frequency US examinations were performed on suspected pediatric patients.
- Evaluated gallbladder wall, common bile duct, biliary echoes, pancreatic duct, and pancreaticobiliary junction.
- Compared US characteristics between patients with and without pancreaticobiliary maljunction.
- Calculated and compared areas under receiver operating characteristic curves (AUCs).
Main Results:
- High-frequency US visualized the pancreaticobiliary junction in 76.8% of patients.
- Pancreatic duct and common bile duct dilation showed higher sensitivity for diagnosis.
- A four-characteristic set achieved optimal diagnostic results (AUC=0.872).
- In cases of indeterminate junctional anatomy, a subset of findings (thickened gallbladder wall, heterogeneous biliary echoes, pancreatic duct dilation) demonstrated superior discrimination (AUC=0.931).
Conclusions:
- High-frequency ultrasonography can directly diagnose pancreaticobiliary maljunction in children by visualizing the abnormal common channel.
- Ultrasound findings like thickened gallbladder wall, heterogeneous biliary echoes, and pancreatic duct dilation are highly informative when junctional anatomy is indeterminate.
Background:
Ultrasound (US) enables clear visualization of the pancreaticobiliary junction within the pancreatic parenchyma. However, limited studies have evaluated its diagnostic utility for pancreaticobiliary maljunction in pediatrics.
Objective:
To prospectively assess the diagnostic value of high-frequency ultrasonography for pancreaticobiliary maljunction in suspected pediatric patients.
Materials And Methods:
All suspected patients received detailed high-frequency US examination of the gallbladder wall, common bile duct, heterogeneous biliary echoes (including stones, sludge, and protein plugs), pancreatic duct, pancreaticobiliary junction, or common channel. Ultrasound characteristics were compared in patients with versus without pancreaticobiliary maljunction. The areas under receiver operating characteristic curves (AUCs) for different US characteristics in the diagnosis of pancreaticobiliary maljunction were calculated and compared.
Results:
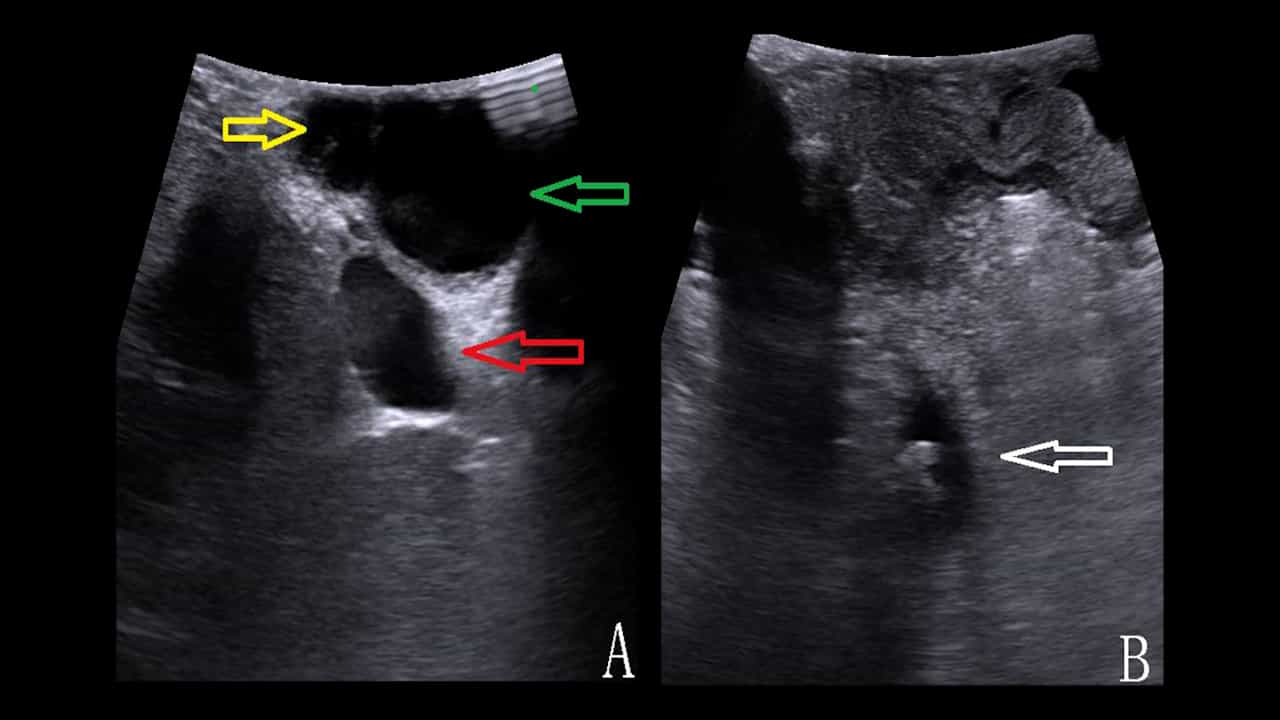
The study included 56 pediatric patients (male 19, female 37; median age 38.5 months, interquartile range 12-81). Pancreaticobiliary maljunction was present in 32 patients and absent in 24. High-frequency ultrasonography successfully depicted the pancreaticobiliary junction in 43 patients (76.8%). Higher sensitivities were observed in pancreatic duct dilation (88%) and common bile duct dilation (97%) compared to gallbladder wall thickening (78%) and heterogeneous biliary echoes (75%) for pancreaticobiliary maljunction identification, though specificities were suboptimal (21-63%). The full four-characteristic set achieved optimal results (AUC=0.872, sensitivity=84%, specificity=75%). The subset excluding common bile duct dilation maintained strong efficacy (AUC=0.860, sensitivity=81%, specificity=75%). Of note, among patients with the junction of pancreaticobiliary duct unclear, the common bile duct-excluded subset (thickened gallbladder wall, heterogeneous biliary echoes, pancreatic duct dilation) had a superior discrimination ability (AUC=0.931, sensitivity=100%, specificity=78%).
Conclusion:
High-frequency ultrasonography enables direct pancreaticobiliary maljunction diagnosis in children via visualization of the abnormal common channel. When junctional anatomy is indeterminate, ultrasound characteristics-particularly thickened gallbladder wall, heterogeneous biliary echoes, and pancreatic duct dilation-serve as highly informative diagnostic indicators.
More Related Videos
 07:44
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
 04:03
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
