
Primary Intraocular Lens Insertion in Infants Under 6 Months of Age: A Retrospective Cohort Study
Idan Farber1, Ahed Imtirat1,2, Mor Erick Rosenblum1
1Faculty of Health Sciences, Ben-Gurion University of the Negev, Be'er Sheva, Israel.

Insights
Primary intraocular lens (IOL) implantation is safe and effective for pediatric cataracts, even in infants under six months. This approach offers comparable visual acuity and complication rates, supporting its use in selected young patients.
Area of Science:
- Ophthalmology
- Pediatric Surgery
Background:
- Pediatric cataracts are a major cause of vision loss in children.
- Intraocular lens (IOL) implantation is standard for children over two, but its use in younger children is debated.
- Primary IOL implantation may mitigate risks associated with prolonged uncorrected aphakia in young children, especially those with limited postoperative care adherence.
Purpose of the Study:
- To evaluate the outcomes of primary intraocular lens (IOL) implantation in pediatric cataract patients across different age groups.
- To compare best-corrected visual acuity (BCVA) and the incidence of postoperative complications, including glaucoma, toxic anterior segment syndrome (TASS), retinal detachment (RD), and the need for yttrium-aluminum-garnet (YAG)/membranectomy.
Main Methods:
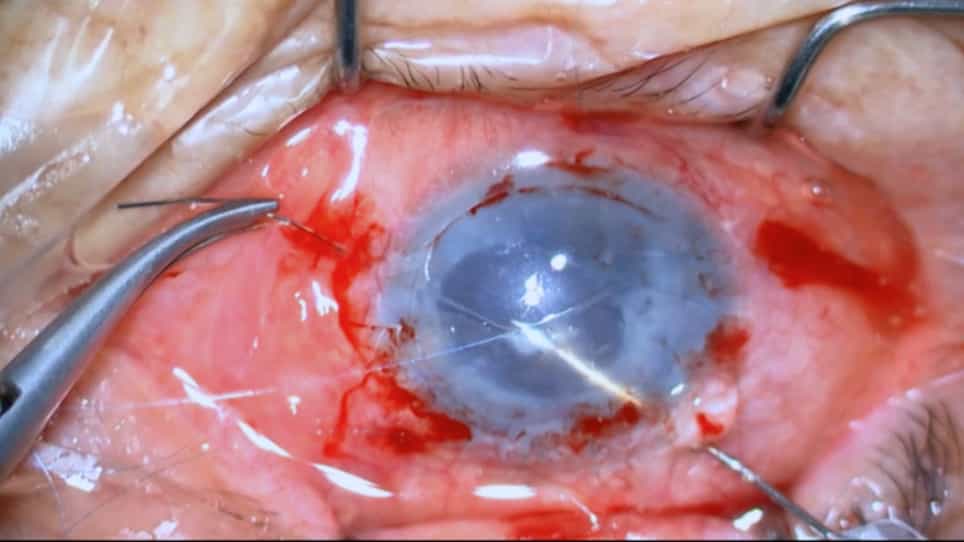
- A retrospective study analyzed 169 eyes from 119 pediatric patients who underwent primary IOL implantation.
- Patients were categorized into three age groups: under 6 months, 6-12 months, and 1-18 years.
- Outcomes were assessed over a median follow-up of 6.4 years, focusing on BCVA and specific complications.
Main Results:
- No significant differences in LogMAR visual acuity or major complications (glaucoma, RD, TASS) were found between age groups.
- The incidence of YAG capsulotomy/membranectomy was highest in the under 6 months group (36%) compared to older groups (22% and 13%).
- Unilateral cases in the youngest group showed a higher rate of YAG/membranectomy, though most patients avoided further surgery.
Conclusions:
- Primary IOL implantation in pediatric cataracts yields comparable visual acuity and complication rates across all studied age groups.
- While younger infants (<6 months), particularly those with unilateral cataracts, may require more YAG/membranectomies, primary IOL remains a viable option.
- These findings support primary IOL implantation as a beneficial surgical strategy for carefully selected pediatric cataract patients.
Background/Aims:
Pediatric cataracts are considered a leading cause of visual impairment. While intraocular lens (IOL) implantation is mostly performed for children >2 years, its use in younger children remains contentious. This study assessed primary IOL in a unique pediatric population characterized by limited adherence to postoperative care, where primary IOL implantation was favored to minimize the risk of prolonged uncorrected aphakia.
Methods:
This retrospective study examined primary IOL implantation outcomes in children across three age brackets: below 6 months, 6-12 months, and 1-18 years, focusing on best-corrected visual acuity (BCVA) and complications including glaucoma, toxic anterior segment syndrome (TASS), retinal detachment (RD), and yttrium-aluminum-garnet (YAG)/membranectomy.
Results:
169 eyes from 119 patients were evaluated over a median follow-up period of 6.4 years. No significant differences were observed between age groups in terms of LogMAR visual acuity (p = 0.344) or the incidence of postoperative complications such as glaucoma (p = 0.244), retinal detachment (p = 0.244), or TASS (p = 0.960). The incidence of YAG capsulotomy/membranectomy was highest in the <6 months group (36%), compared to 22% in the 6-12 months group and 13% in the >1 year group (p = 0.020). Among unilateral cases, all 3 patients diagnosed before 6 months required YAG/membranectomy.
Conclusion:
Primary IOL implantation for pediatric cataracts resulted in comparable visual acuity and overall complication rates across all age groups. Although a higher incidence of YAG/membranectomy was observed in children under 6 months, particularly among unilateral cases, most patients still avoided the need for additional surgical intervention. These findings support primary IOL implantation as a valid option for selected patients.