Related Experiment Video
Updated: Aug 9, 2026

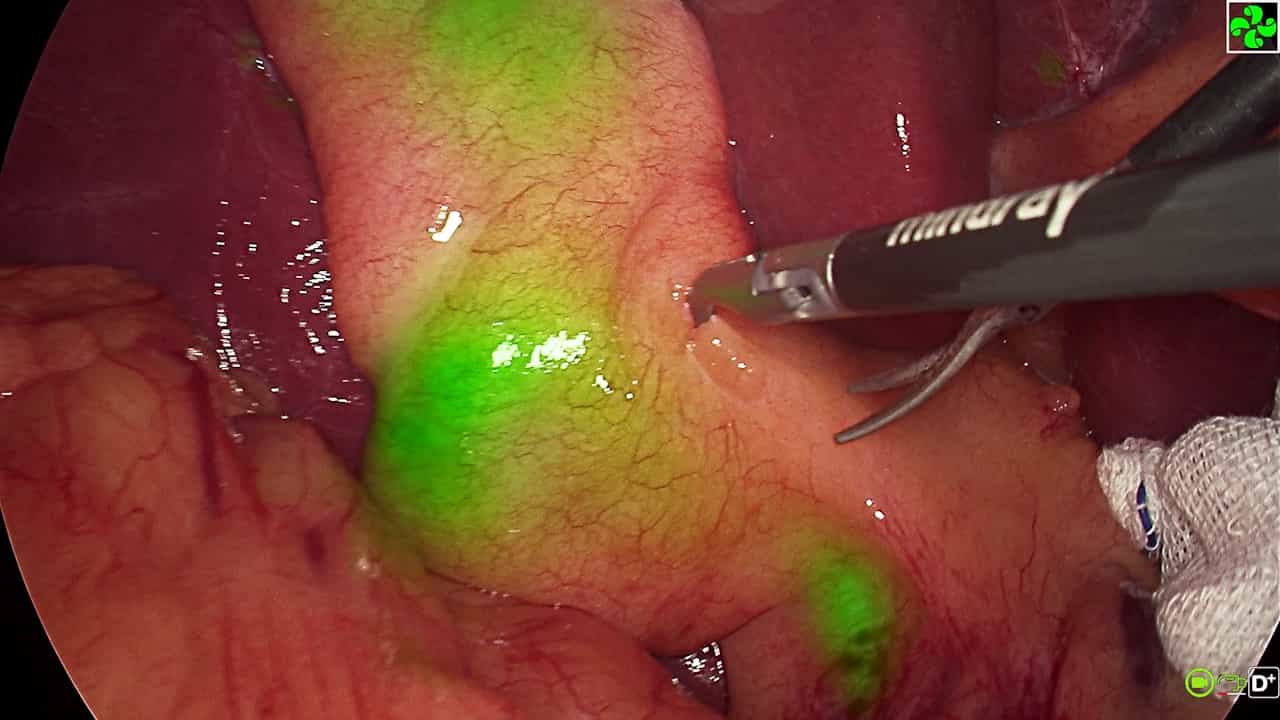
The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
Published on: January 31, 2025
Preoperative C-reactive protein as a predictor of conversion and complications in laparoscopic cholecystectomy for
Parham Khoshdani Farahani1, Shakiba Khosravi Nejat2
1Department of Surgery, School of Medicine, Alborz University of Medical Sciences, Karaj, Iran. pkhoshdanifarahani@gmail.com.

Introduction:
Laparoscopic cholecystectomy (LC) is the gold standard for gallbladder surgery but may require conversion to open surgery in complicated cases. While preoperative C-reactive protein (CRP) is known to reflect inflammation, its predictive role in surgical outcomes remains debated. This study evaluated CRP as a predictor of surgical outcomes in acute cholecystitis and uncomplicated gallbladder stones, explicitly excluding choledocholithiasis to isolate gallbladder-specific inflammatory predictors.
Materials And Methods:
This retrospective cohort study analyzed 180 patients undergoing LC for acute cholecystitis (n = 76), chronic cholecystitis (n = 14), or uncomplicated cholelithiasis (n = 90). Preoperative CRP levels were measured, and ROC analysis determined optimal thresholds for predicting conversion and complications (hydrops, necrosis, phlegmon, abscess, bleeding). Due to incomplete albumin data (17.8% missing), the CRP-to-albumin ratio (CAR) could not be robustly analyzed; thus, CRP was the primary focus. Patients with common bile duct (CBD) stones (n = 32) were excluded to eliminate confounding biliary obstruction. Demographic and clinical data of the patients were recorded, and statistical analysis was performed using R software.
Results:
Acute cholecystitis patients had higher CRP (25.4 vs. 7.1 mg/L, p < 0.001), longer hospital stays (7.4 vs. 2.2 days, p = 0.001), and more complications (e.g., necrosis: 16.7% vs. 1.1%, p < 0.001). CRP predicted conversion to open surgery with Area Under the Curve (AUC) 0.964 (optimal threshold: 7.5 mg/L, sensitivity 100%) and complications (AUC 0.899-0.983). Chronic cholecystitis patients had lower CRP (4.2 mg/L) and no conversions.
Conclusions:
CRP demonstrated high accuracy (AUC 0.964) in predicting conversion and complications in acute cholecystitis, with thresholds actionable for surgical planning. Its utility in uncomplicated cholelithiasis is limited.