Related Experiment Video
Updated: Jan 15, 2026


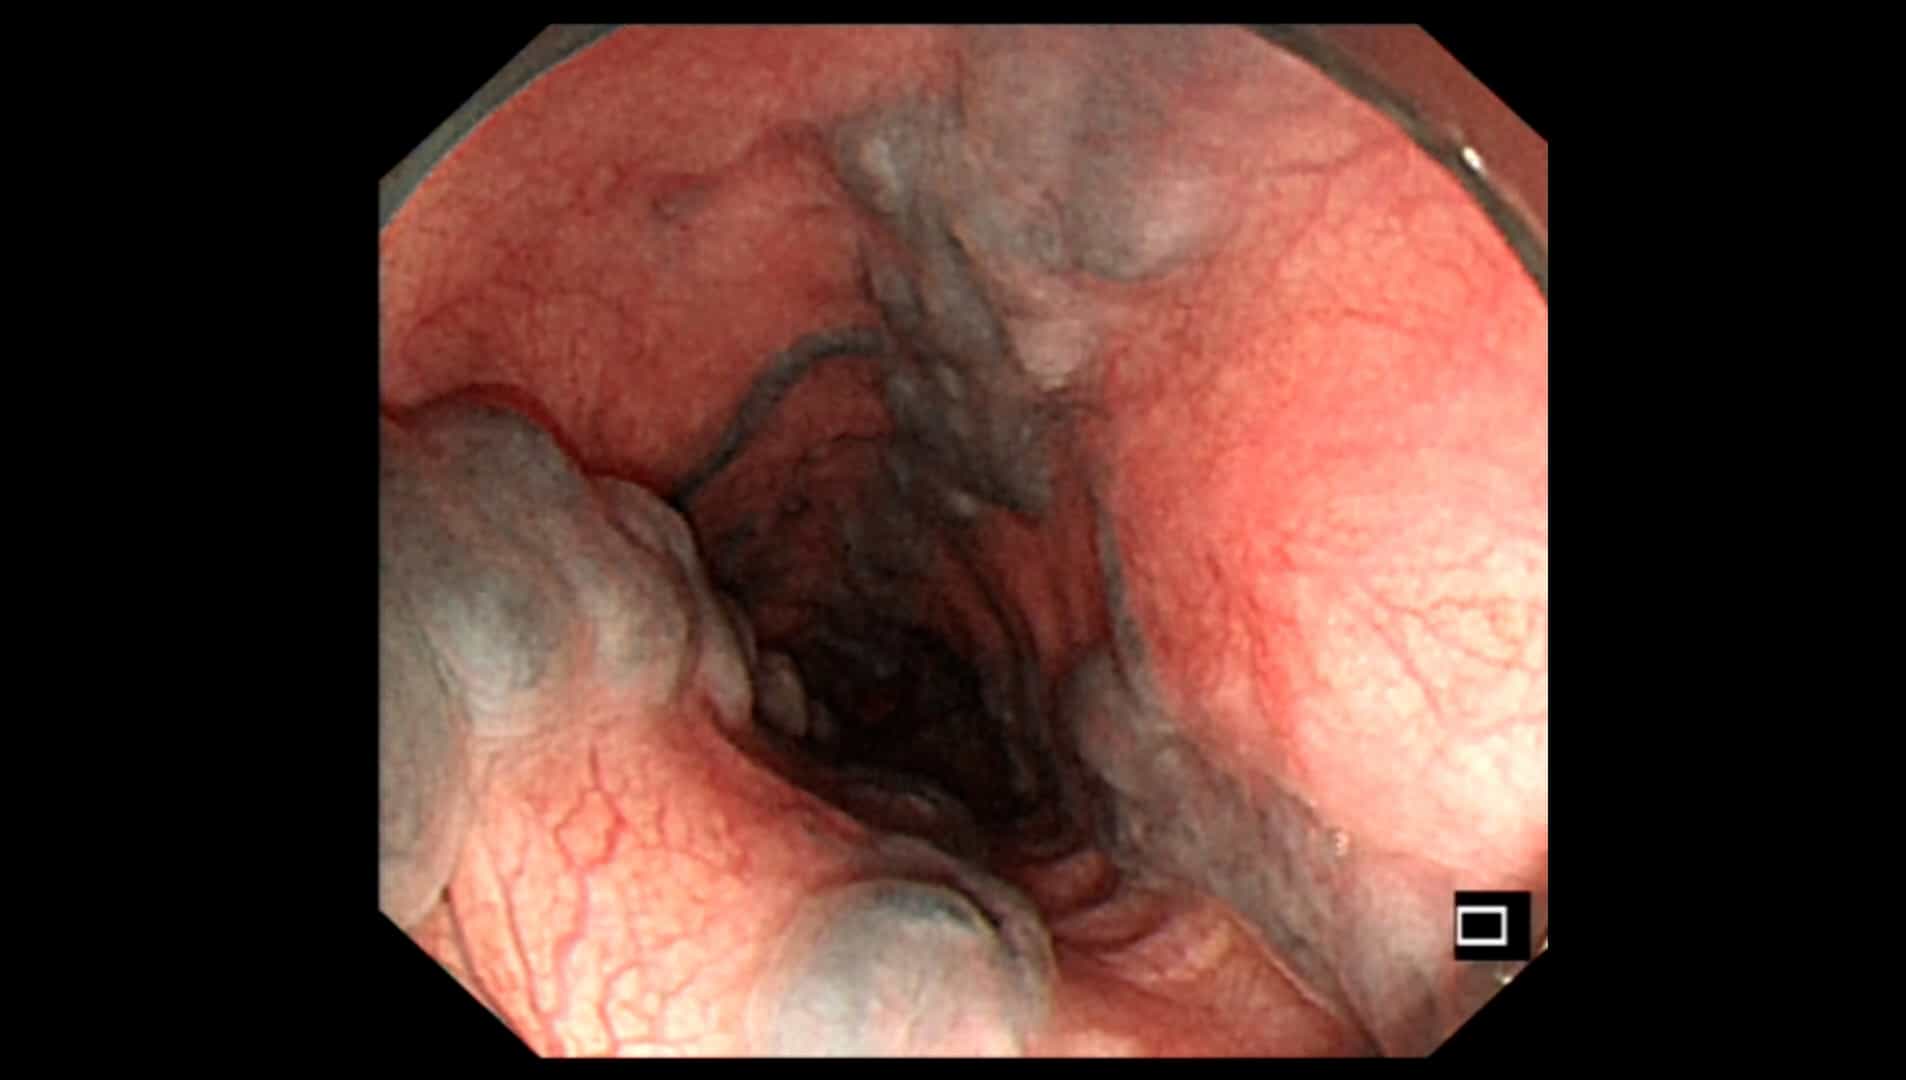
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025
Stenting Versus Endoscopic Vacuum Therapy for Anastomotic Leakage After Esophago-Gastric Surgery
Carlo Galdino Riva1, Stefano Siboni1, Matteo Capuzzo1
1Division of General and Emergency Surgery, IRCCS Policlinico San Donato, University of Milan, 20097 Milan, Italy.

Abstract:
Background: Anastomotic leakage (AL) is a major complication after esophago-gastric surgery, with incidence rates of 11-21% and mortality up to 14%. Early intervention is essential to reduce morbidity. Endoscopic treatments have advanced, with self-expandable metal stents (SEMSs) as the traditional standard (success ~90%), but they carry risks like migration, stenosis, and need for drainage. Endoscopic vacuum therapy (EVT), applying negative pressure to drain secretions and promote healing, has shown success rates of 66-100%. Limited comparative data exists from small retrospective studies. This study compares SEMS and EVT for safety and efficacy in AL management. Methods: A retrospective case-control study from a prospective database at our institution was performed (March 2012-2025). We included patients with AL post-esophageal/gastric surgery treated endoscopically (SEMS or EVT). We excluded patients treated with conservative or surgical management. Demographics, comorbidities, oncology, surgery type, leak details, treatments, and outcomes were collected. Primary outcome was complete healing of the leak, while secondary outcomes were time to success, number of procedures needed, hospital stay, complications, mortality. Results: From 592 resections, we extracted 68 AL (11.5%), 45 of which met the inclusion criteria (22 SEMS, 23 EVT). Groups were similar demographically, but SEMS had more respiratory issues (43% vs. 8.7%, p = 0.018). SEMS were used more after esophagectomy (86.4% vs. 56.5%, p = 0.004); EVT was performed mostly after gastrectomy (34.7% vs. 9.1%, p = 0.009). Success rate was 86.4% for SEMS vs. 95.6% for EVT (p = 1.000). Complications were significantly lower in EVT (8.3% vs. 50%, p = 0.001; SEMS: 36.4% migrations, 18.2% stenoses). Leak onset time, modality of diagnosis, and leak size were comparable among the groups. Need for jejunostomy was higher in EVT (43.5% vs. 9.1%, p = 0.015), while chest drains in SEMS (63.7% vs. 13.1%, p < 0.001). Hospital stays (33-38 days, p = 0.864) and mortality (22.7% vs. 8.7%, p = 0.225) were similar. No differences were observed in terms of long-term mortality (log-rank p = 0.815). Conclusions: SEMS and EVT are both effective for AL after esophago-gastric surgery. EVT offers fewer complications and shorter treatment, so it is favored especially for esophago-jejunal leaks.

Related Concept Videos
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...