Related Experiment Video
Updated: Jan 15, 2026
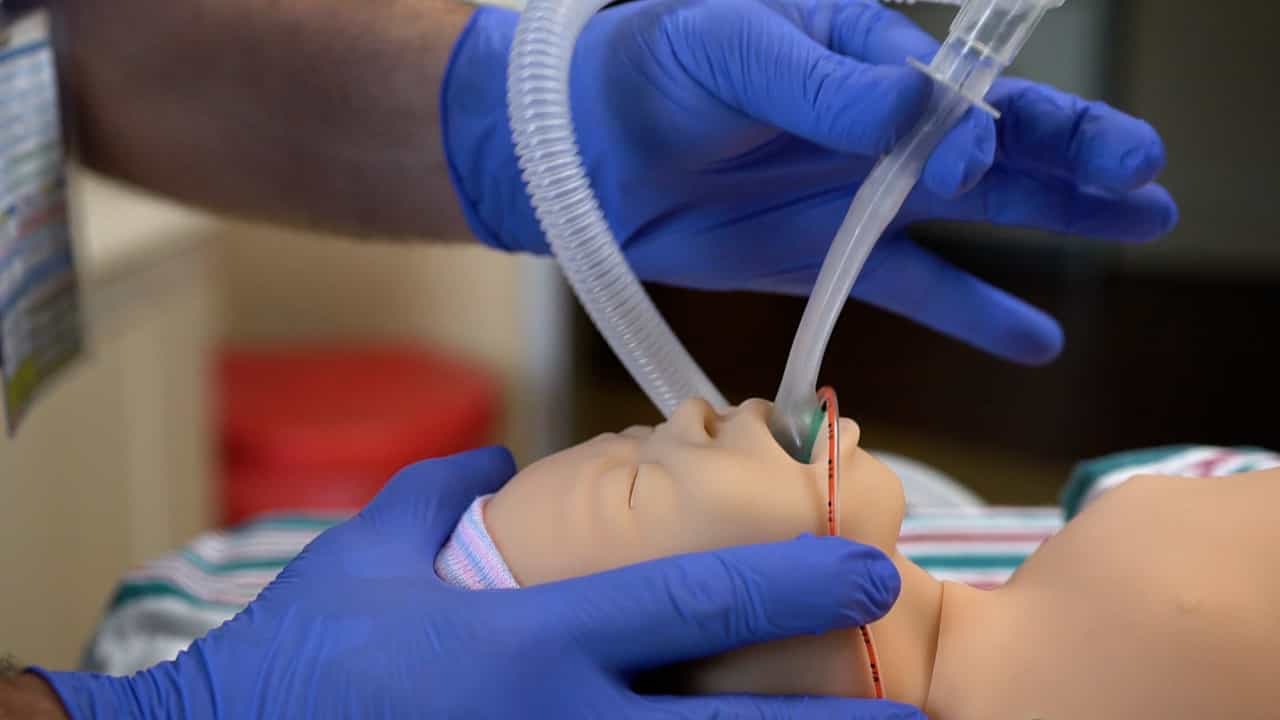
Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Airway Management in Pregnancy: A Case of Successful Treatment of Subglottic Stenosis
Linh Ton1, Ritika Modi1, Diane Choi2
1Anesthesiology, University of Miami Miller School of Medicine, Miami, USA.

Subglottic stenosis (SGS) is a narrowing of the airway that can be congenital or acquired, often resulting from prior intubation, infection, or autoimmune diseases. When SGS occurs during pregnancy, it presents unique challenges for anesthetic management. Symptoms commonly mimic those caused by pregnancy-related airway changes, making diagnosis and treatment more challenging. Additionally, ensuring both maternal and fetal safety during anesthesia is critical and requires a multidisciplinary approach. We report a case of a 26-year-old pregnant woman at 12 weeks' gestation who presented with severe hyperemesis gravidarum resulting in acute respiratory failure with suspected esophageal perforation, necessitating intubation. A Gastrografin study later ruled out perforation, and she was successfully extubated after two days without surgical intervention. One month later, she was readmitted with progressive dyspnea and wheezing, initially misdiagnosed as an asthma exacerbation. Her symptoms failed to improve with IV steroids, and a bedside fiberoptic exam by ENT revealed 85% SGS. Balloon dilation was performed under general anesthesia with a carefully tailored anesthetic plan, including the use of nebulized lidocaine, propofol, sevoflurane, dexmedetomidine, ketamine, and jet ventilation to maintain spontaneous ventilation and optimize maternal and fetal safety. Postoperatively, her respiratory symptoms improved, and she went on to have an uneventful delivery five months later. This particular case highlights the critical role of anesthesia in managing SGS in pregnancy. Key considerations included maintaining stable oxygenation, preventing airway trauma, and ensuring minimal risk to the fetus. Balloon dilation proved effective in restoring airway patency. This case underscores the importance of a multidisciplinary approach to anesthesia care and emphasizes the need for individualized anesthetic strategies when managing airway conditions like SGS in pregnant patients.
Subglottic stenosis (SGS) is a narrowing of the airway that can be congenital or acquired, often resulting from prior intubation, infection, or autoimmune diseases. When SGS occurs during pregnancy, it presents unique challenges for anesthetic management. Symptoms commonly mimic those caused by pregnancy-related airway changes, making diagnosis and treatment more challenging. Additionally, ensuring both maternal and fetal safety during anesthesia is critical and requires a multidisciplinary approach. We report a case of a 26-year-old pregnant woman at 12 weeks' gestation who presented with severe hyperemesis gravidarum resulting in acute respiratory failure with suspected esophageal perforation, necessitating intubation. A Gastrografin study later ruled out perforation, and she was successfully extubated after two days without surgical intervention. One month later, she was readmitted with progressive dyspnea and wheezing, initially misdiagnosed as an asthma exacerbation. Her symptoms failed to improve with IV steroids, and a bedside fiberoptic exam by ENT revealed 85% SGS. Balloon dilation was performed under general anesthesia with a carefully tailored anesthetic plan, including the use of nebulized lidocaine, propofol, sevoflurane, dexmedetomidine, ketamine, and jet ventilation to maintain spontaneous ventilation and optimize maternal and fetal safety. Postoperatively, her respiratory symptoms improved, and she went on to have an uneventful delivery five months later. This particular case highlights the critical role of anesthesia in managing SGS in pregnancy. Key considerations included maintaining stable oxygenation, preventing airway trauma, and ensuring minimal risk to the fetus. Balloon dilation proved effective in restoring airway patency. This case underscores the importance of a multidisciplinary approach to anesthesia care and emphasizes the need for individualized anesthetic strategies when managing airway conditions like SGS in pregnant patients.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...