Related Experiment Video
Updated: Jul 26, 2026
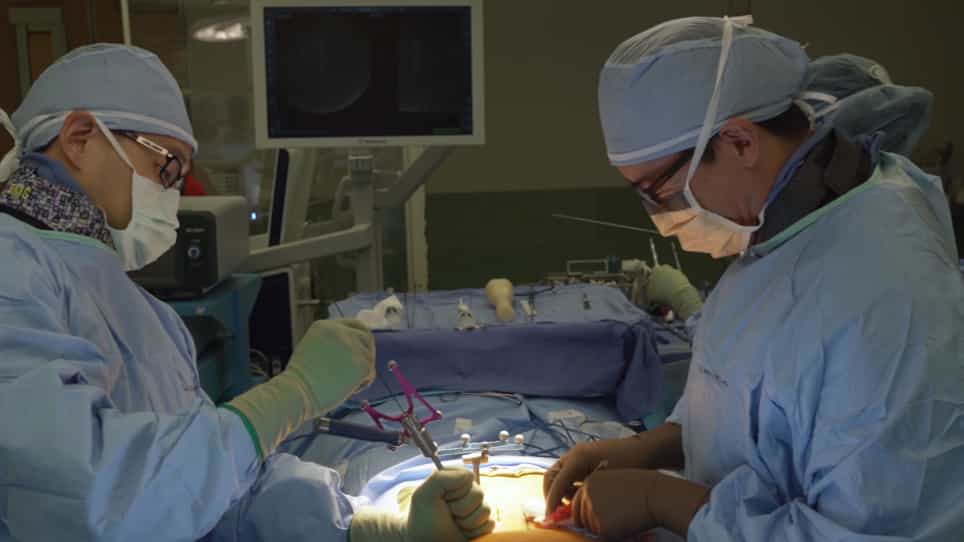

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Impact of Cage Angle on Spinal Alignment in Posterior Lumbar Interbody Fusion: A Comparison of 12°, 16°, and 22°
Daisuke Inoue1, Hiroaki Matsumori1, Hideki Shigematsu2
1Department of Orthopedic Surgery, Kashiba Asahigaoka Hospital, Kashiba, Japan.

Introduction:
We evaluated the effect of 3 high-angle cages on spinal alignment and clinical outcomes following posterior lumbar interbody fusion (PLIF).
Methods:
A retrospective analysis was performed on 104 patients who underwent PLIF at the L4/5 level between January 2021 and August 2023. Patients were divided into 3 groups: 12° (L), 16° (M), and 22° (H) cage groups. Lumbar spine radiographs were taken preoperatively and one year postoperatively to assess slip rate (% slip), segmental lumbar lordosis (SLL), segmental intervertebral angle (SIA), lumbar lordosis (LL), pelvic incidence-LL, sagittal vertical axis (SVA), Japanese Orthopedic Association score, and lower back pain visual analog scale score. Bone union and cage subsidence rates were evaluated using computed tomography 6 months postoperatively. Statistical analyses were performed using either the Wilcoxon signed rank test, Kruskal-Wallis test, or z-test.
Results:
Intragroup analysis showed significant improvements in local alignment, with notable SVA improvement in the H group. Intergroup comparisons revealed no significant differences in preoperative evaluation items. Postoperatively, the H group showed significantly greater improvements in SLL and SIA than the L group. Although no significant difference was observed in bone union, the cage subsidence rate was significantly higher in the H group than in other groups.
Conclusions:
PLIF using high-angle cages (≥12°) significantly improved local alignment in all groups. The 22° cage showed greater improvements in SLL and SIA but a higher incidence of cage subsidence. No significant clinical differences were observed between groups. LL in the lower lumbar spine can be achieved relatively easily using a cage with a larger angle in PLIF. However, although a cage with a larger angle may be advantageous for lordosis formation, postoperative clinical outcomes do not differ; therefore, cage selection should consider the surgeon's skill and patient factors, such as the degree of preoperative lumbar disc degeneration, instability, and alignment.
Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:16
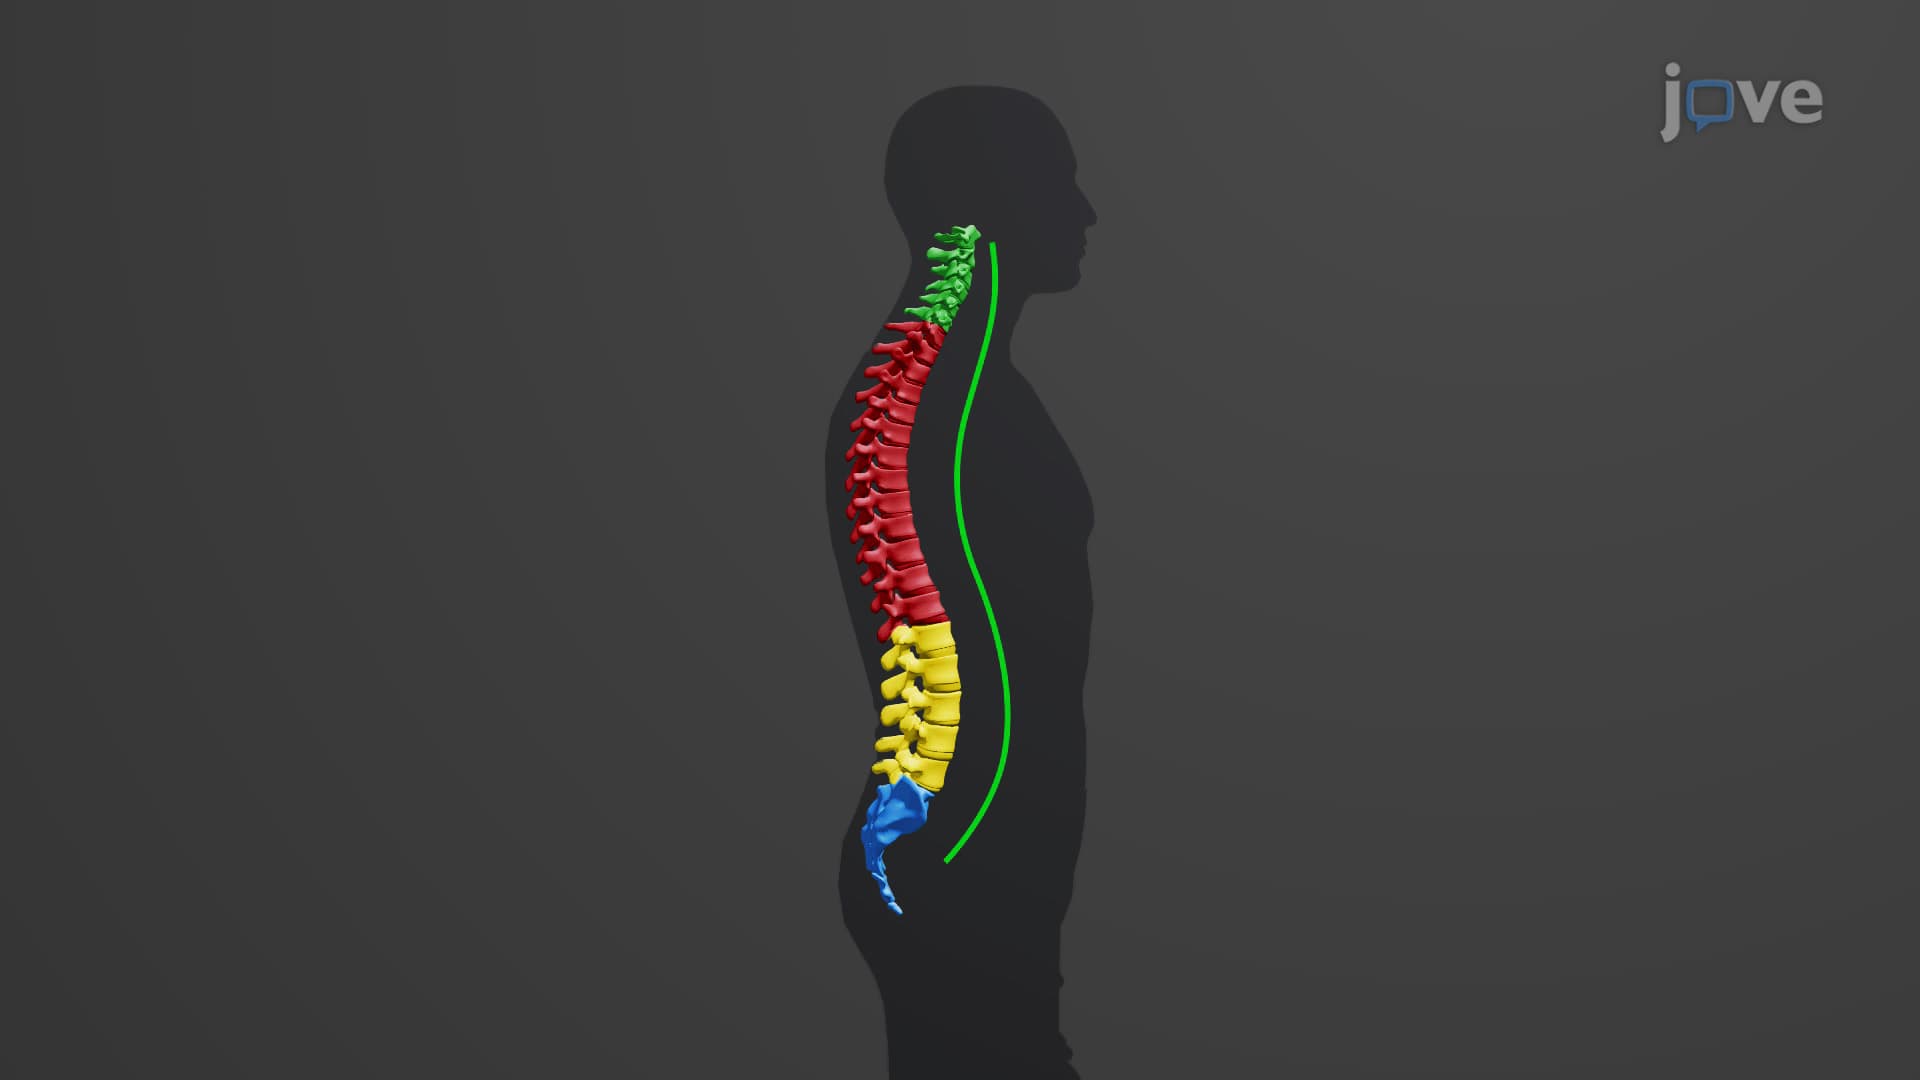
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:30
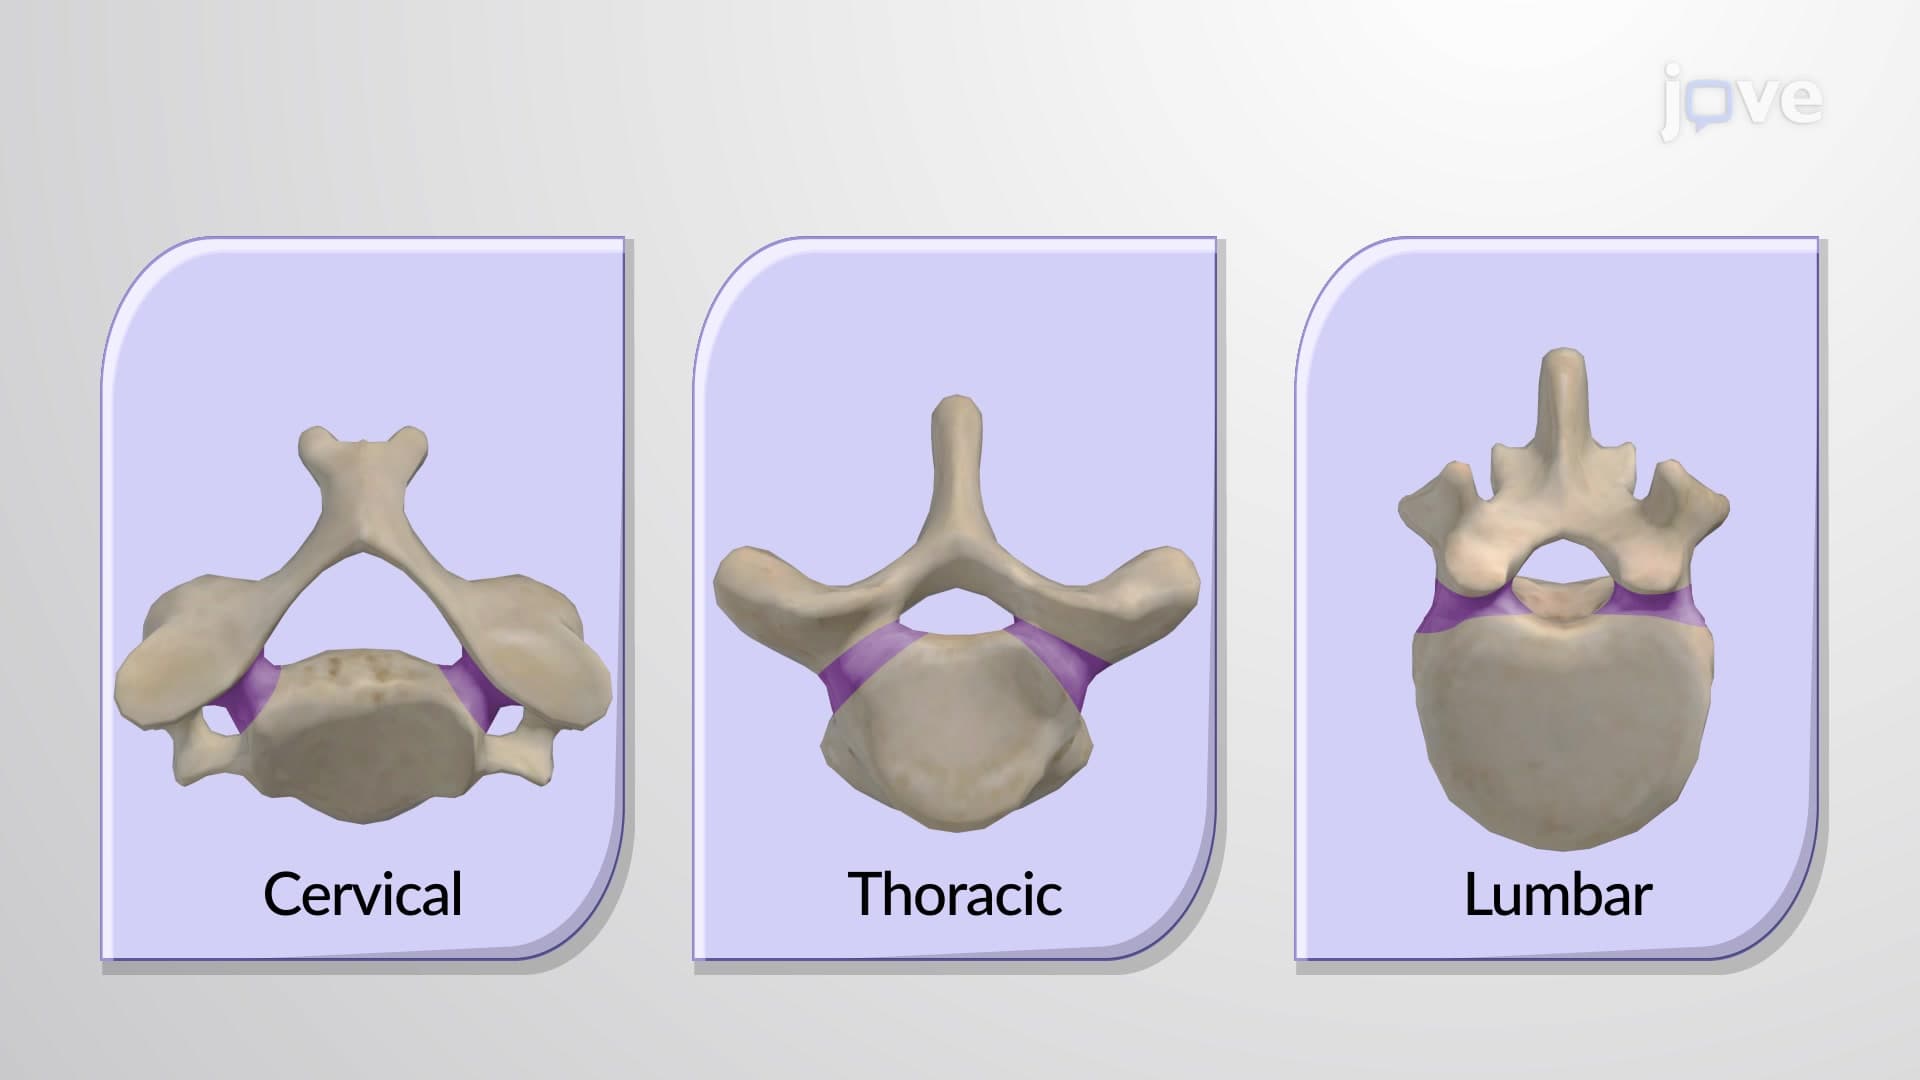
General Structure of a Vertebra
 01:28
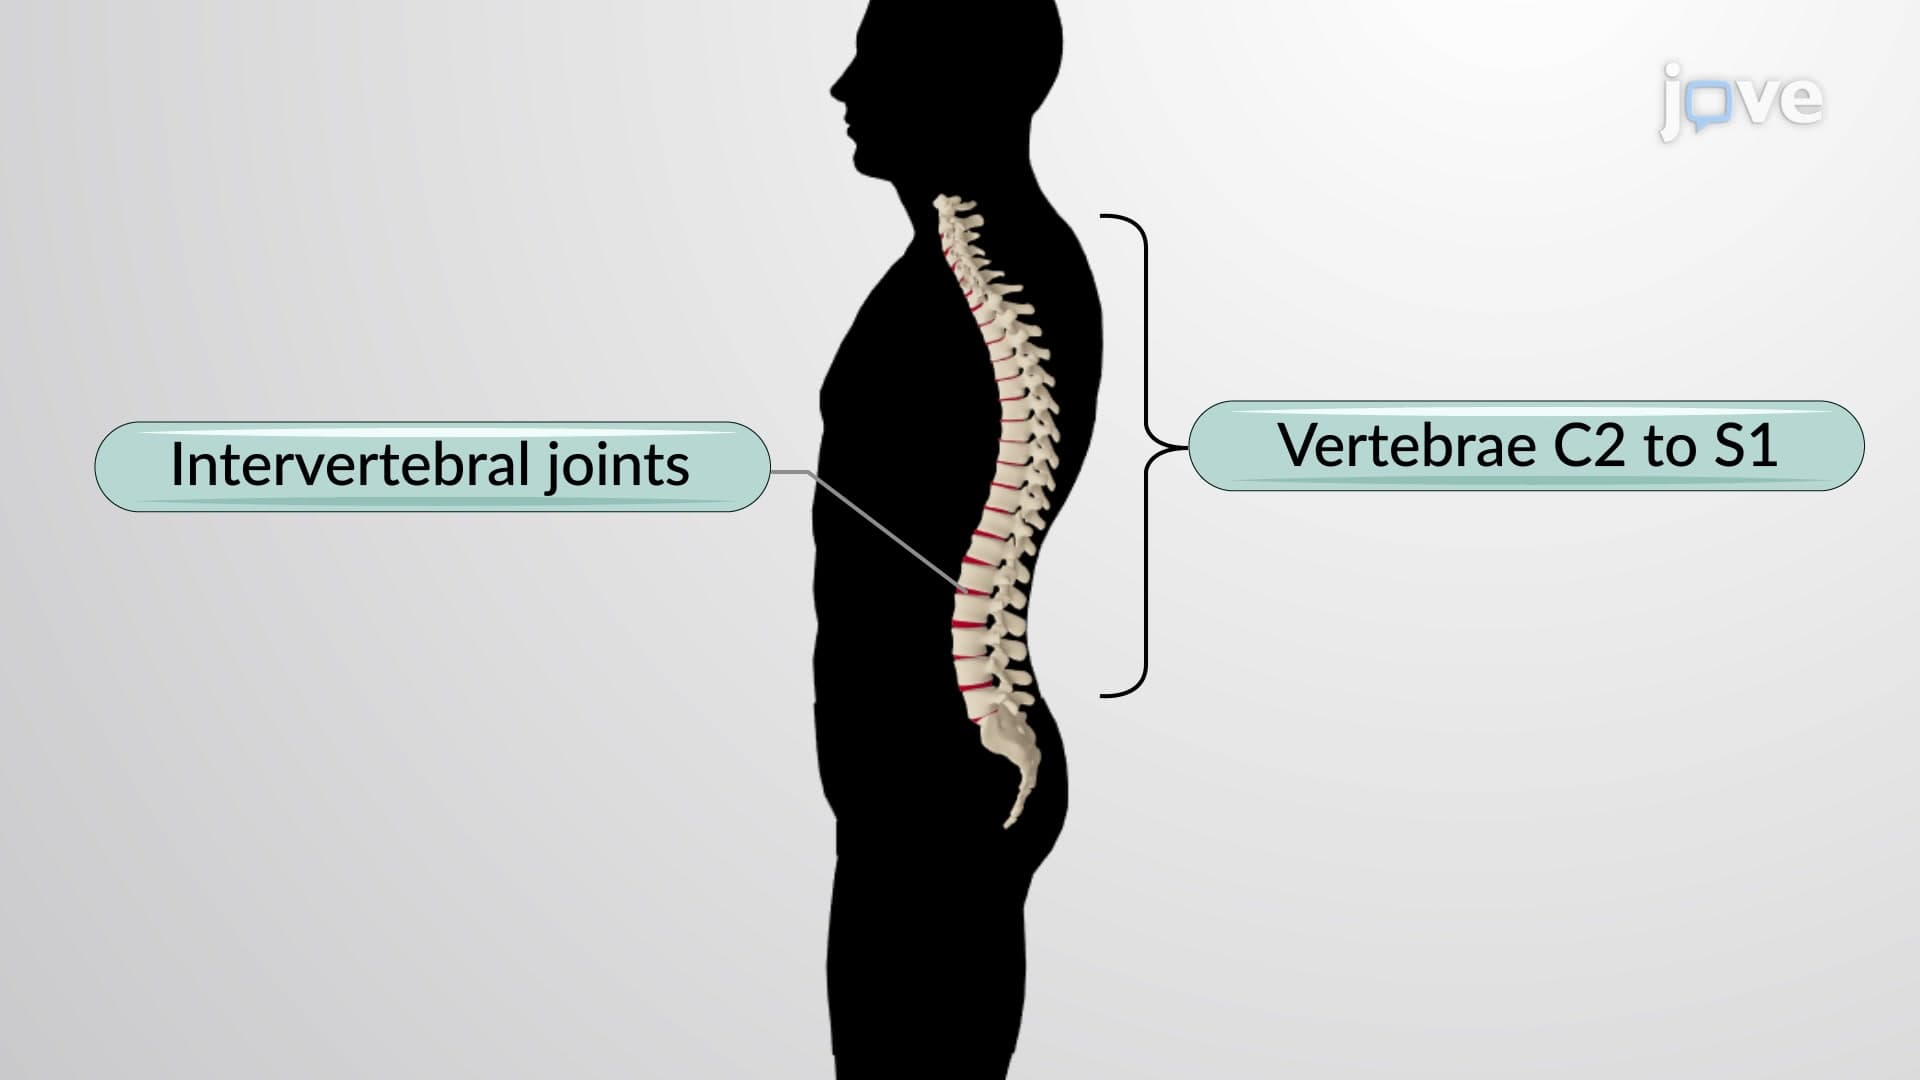
Articulations of the Vertebral Column
 01:10
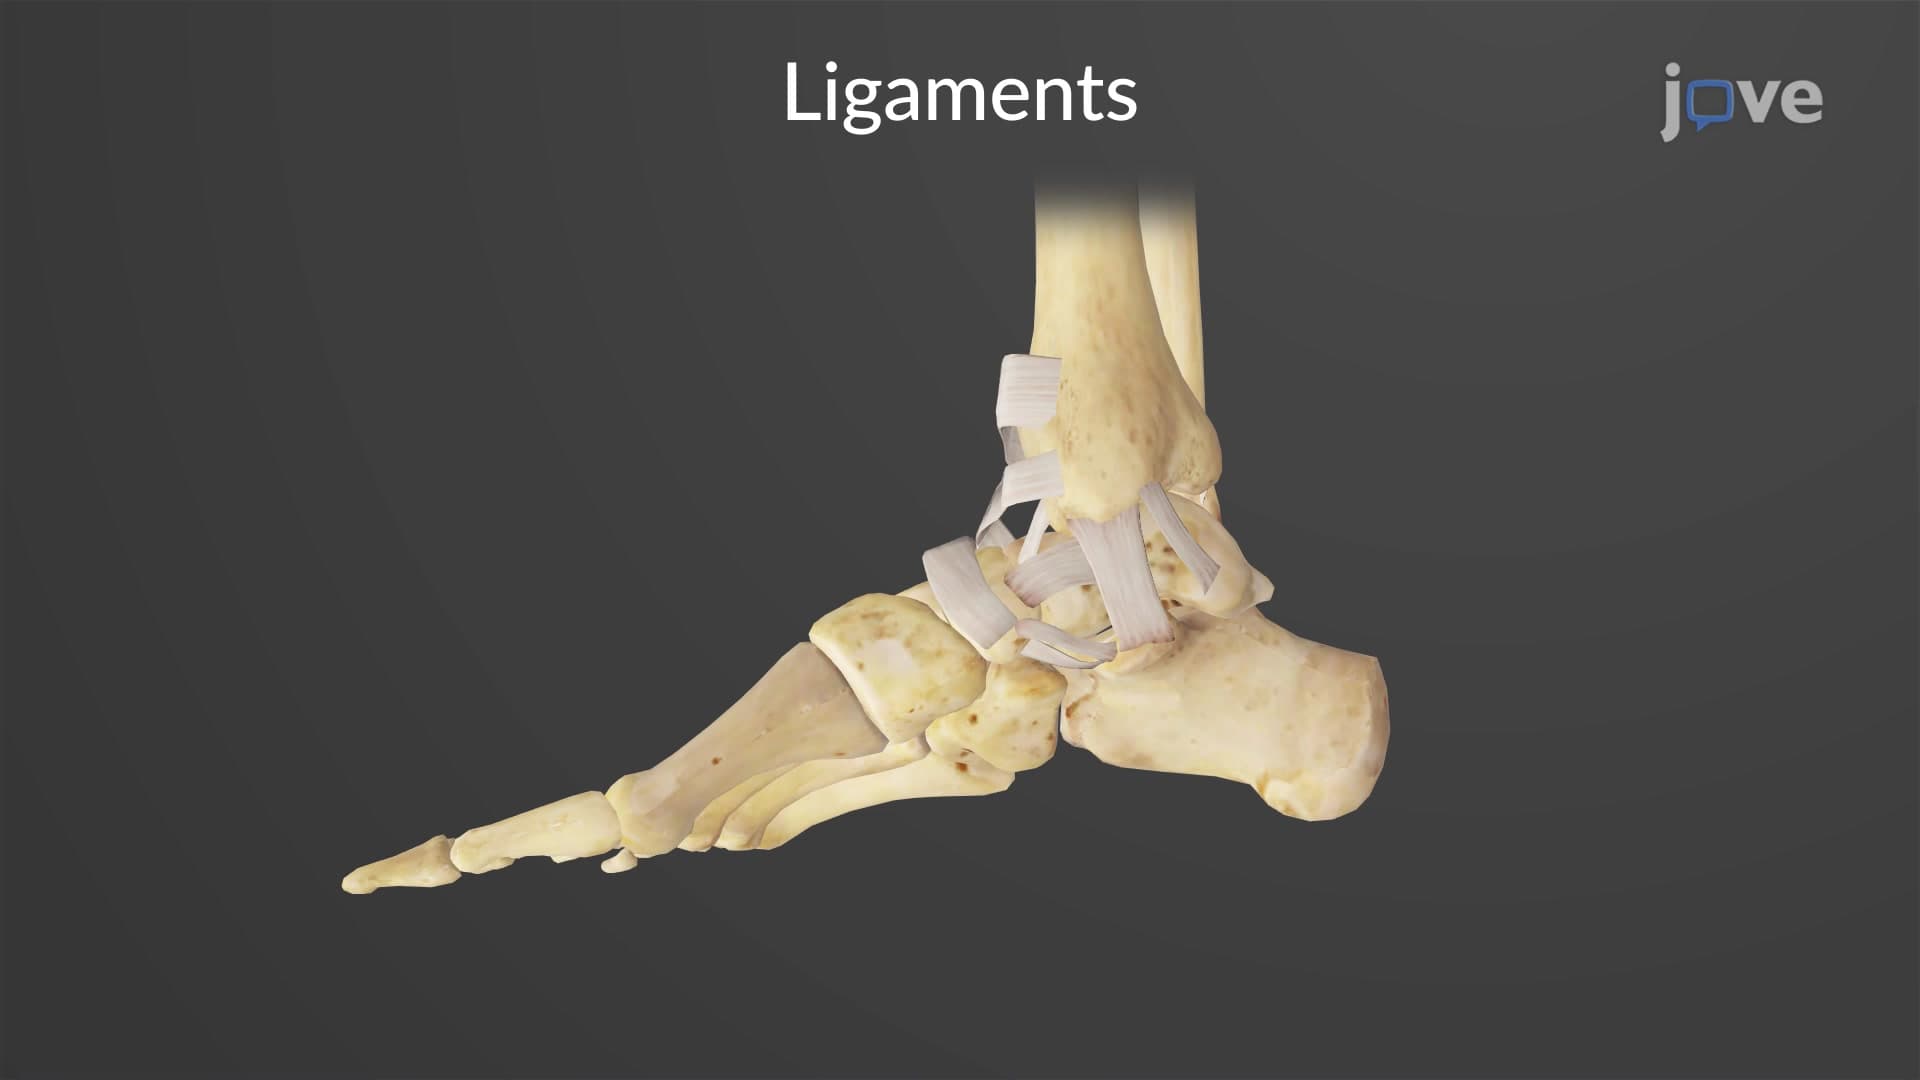
Ankle Joint
 01:15
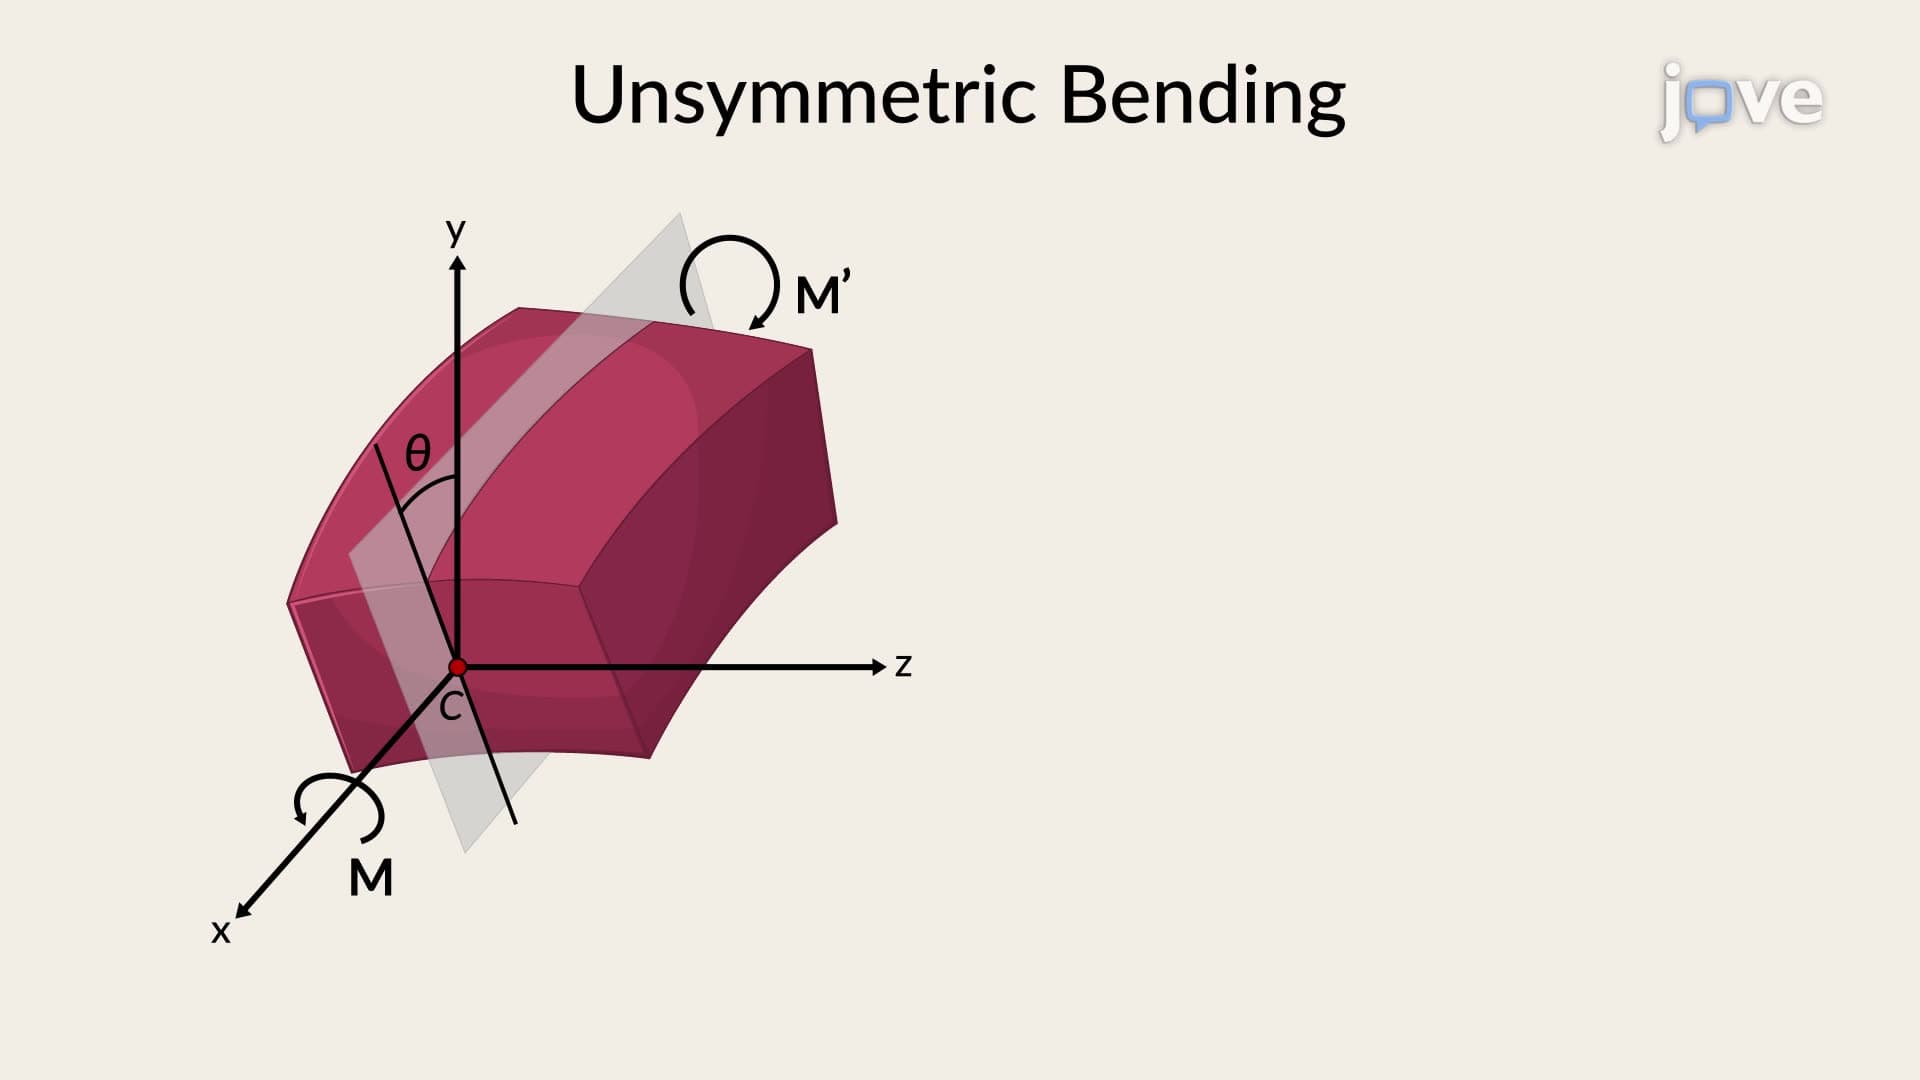
Unsymmetric Bending - Angle of Neutral Axis
When a bending moment is applied at an angle θ concerning the vertical axis of a symmetrical member, it can be resolved into components along the member's principal centroidal axes. The...