Related Experiment Video
Updated: Jan 15, 2026
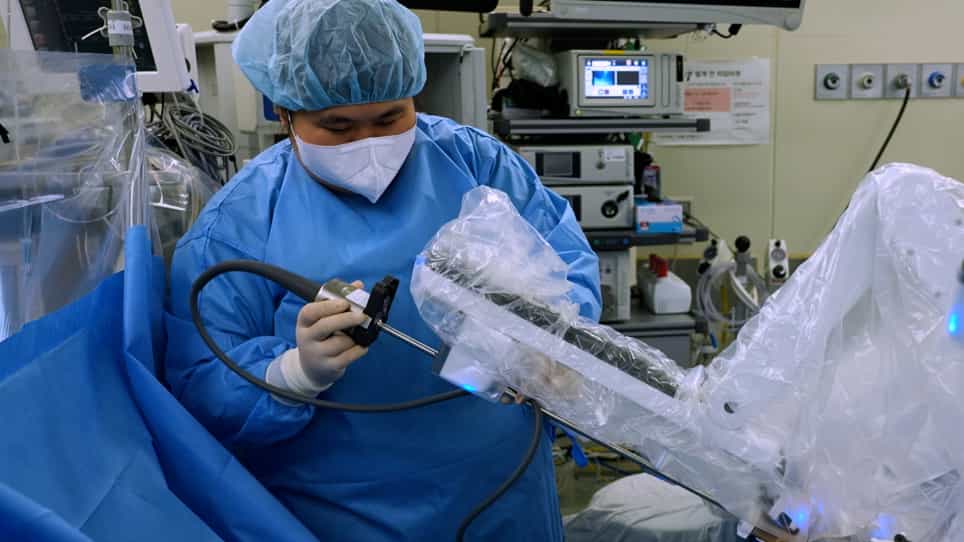

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Kidney Transplant Outcomes With Non-Depleting Antibody Induction Therapy in Human Leucocyte Antigen Sensitised
Ria Nagpal1, Katie Butler2, Nicola Thal2
1Department of Renal Medicine and Transplantation, Royal Free Hospital NHS Foundation Trust, London, United Kingdom.

Lymphocyte depleting induction is recommended for kidney transplant recipients (KTRs) at high immunological risk, which traditionally includes those with detectable anti-human leucocyte antigen antibodies. Data to support this approach in the modern era of histocompatibility testing are limited. We investigated outcomes in KTRs who underwent Basiliximab induction between 2012-2023 in the UK. We stratified outcomes by levels of sensitisation and T cell epitope mismatch (PIRCHE-II) scores. 1348 KTRs were included; 859 (63.7%) were unsensitised, 351 (26.0%) sensitised (calculated reaction frequency [cRF] 1%-84%), and 138 (10.3%) highly sensitised (cRF 85%-100%). Patient survival, allograft survival, and death-censored graft survival (DCGS) were 97%, 94%, and 97% at 1 year, and 88%, 78%, and 84% at 5 years respectively. There were no differences in outcomes between unsensitised and sensitised recipients; graft survival was lower in highly sensitised patients. T cell epitope mismatch scores were higher in those with rejection at 1 year (ln[PIRCHE+1] 3.94 ± 1.01 no rejection vs. 4.25 ± 0.58 rejection, p = 0.02) and epitope mismatch was associated with early rejection in multivariable analyses (Odds Ratio 1.58, 95% CI 1.01-2.62). Hence, non-depleting induction provides good outcomes in unsensitised and sensitised KTRs. T cell epitope mismatches inform rejection risk in the first post-transplant year.
Lymphocyte depleting induction is recommended for kidney transplant recipients (KTRs) at high immunological risk, which traditionally includes those with detectable anti-human leucocyte antigen antibodies. Data to support this approach in the modern era of histocompatibility testing are limited. We investigated outcomes in KTRs who underwent Basiliximab induction between 2012-2023 in the UK. We stratified outcomes by levels of sensitisation and T cell epitope mismatch (PIRCHE-II) scores. 1348 KTRs were included; 859 (63.7%) were unsensitised, 351 (26.0%) sensitised (calculated reaction frequency [cRF] 1%-84%), and 138 (10.3%) highly sensitised (cRF 85%-100%). Patient survival, allograft survival, and death-censored graft survival (DCGS) were 97%, 94%, and 97% at 1 year, and 88%, 78%, and 84% at 5 years respectively. There were no differences in outcomes between unsensitised and sensitised recipients; graft survival was lower in highly sensitised patients. T cell epitope mismatch scores were higher in those with rejection at 1 year (ln[PIRCHE+1] 3.94 ± 1.01 no rejection vs. 4.25 ± 0.58 rejection, p = 0.02) and epitope mismatch was associated with early rejection in multivariable analyses (Odds Ratio 1.58, 95% CI 1.01-2.62). Hence, non-depleting induction provides good outcomes in unsensitised and sensitised KTRs. T cell epitope mismatches inform rejection risk in the first post-transplant year.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:40
Cell-mediated Immune Responses