Related Experiment Video
Updated: Jan 14, 2026
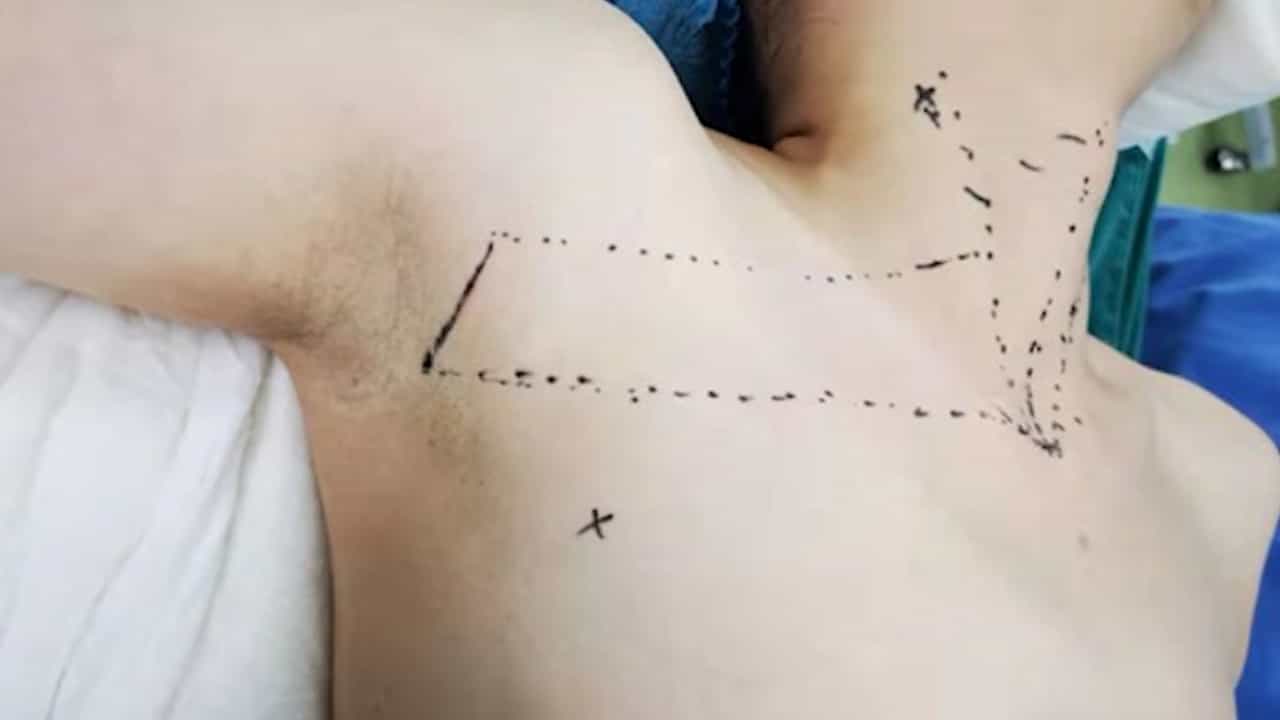

Gasless Endoscopic Thyroidectomy via the Trans-Axillary Approach
Published on: September 15, 2023
Plasmapheresis as a Bridge to Urgent Thyroidectomy in Severe Amiodarone-Induced Thyrotoxicosis
Roneil N Parikh1,2, Emma Verner3,2, Avinash Suryawanshi4,2
1Breast and Endocrine Surgery, Concord Repatriation General Hospital, Sydney, AUS.

Abstract:
Amiodarone-induced thyrotoxicosis (AIT) is a challenging condition to manage due to the drug's long half-life and frequent resistance to conventional medical therapy. Plasmapheresis has emerged as a therapeutic option in patients requiring urgent thyroidectomy. We present the case of a 68-year-old male with a history of atrial fibrillation treated with amiodarone for two years, who presented with diarrhea, weight loss, and fever. Clinical examination revealed tachycardia and pyrexia, without goitre or ophthalmopathy. Laboratory tests showed thyrotoxicosis (free T4 >100 pmol/L), deranged liver function tests, and negative thyroid-stimulating hormone (TSH)-receptor antibodies. Imaging with abdominal CT revealed a 10.7 cm lesion in the left hepatic lobe, suspicious for ruptured hepatocellular carcinoma (HCC), warranting a planned left hemi-hepatectomy. Thyroid ultrasound demonstrated mild glandular enlargement without nodules, consistent with type 2 AIT. Despite medical therapy, the patient's thyrotoxic symptoms worsened, with persistent fever, tachycardia, and tremors. He underwent three sessions of plasmapheresis, which served as a bridge to total thyroidectomy, to reduce the risk of intraoperative thyroid storm. The postoperative course was uncomplicated, and histology confirmed type 2 AIT. Two weeks later, the patient underwent successful left hemi-hepatectomy, with pathology confirming moderately differentiated HCC. AIT can exacerbate pre-existing cardiac conditions and is associated with increased morbidity and mortality. While initial management typically involves conventional therapy, patients with severe disease or those requiring urgent surgical interventions may benefit from timely plasmapheresis as a bridging strategy to definitive thyroidectomy. The optimal timing, number of exchanges, and choice of replacement fluid remain areas for further research.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias