Related Experiment Video
Updated: Aug 1, 2026

Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Long-term outcome of the initial cases with recipient-side minimal invasive liver transplantation: Single-center
Jinsoo Rhu1, Jongman Kim1, Namkee Oh1
1Department of Surgery, Samsung Medical Center, Sungkyunkwan University School of Medicine, Seoul, Korea.

Abstract:
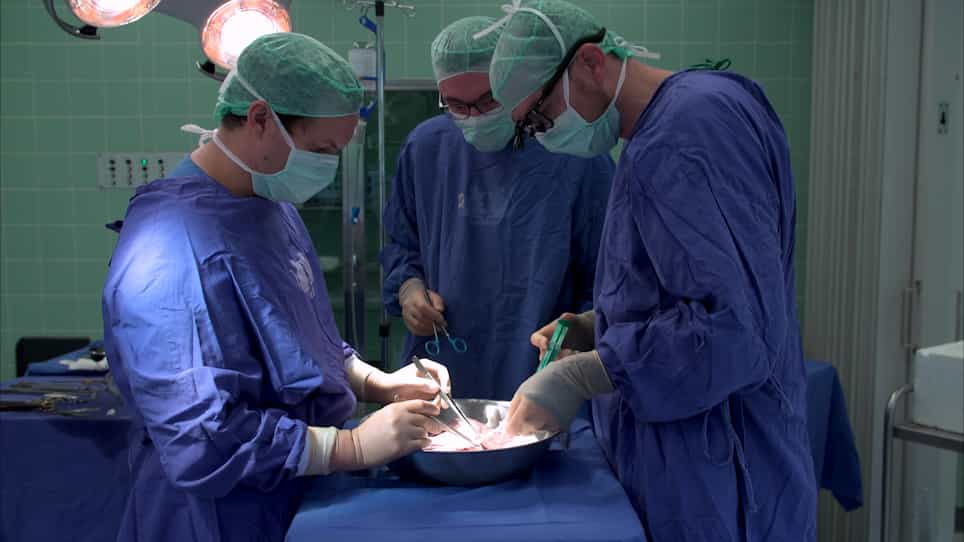
Living donor liver transplantation has evolved with minimal invasive donor hepatectomy, now widely adopted at leading centers. The next frontier is a recipient-side minimally invasive approach, yet data remains scarce. We report our center's experience with totally laparoscopic living-donor liver transplantation (TLLT) compared with conventional open techniques. We conducted a retrospective analysis of adult living donor liver transplantations performed at Samsung Medical Center between January 2022 and June 2024. Open approaches were compared with minimal invasive approaches. Further analysis was performed by comparing open anastomosis to laparoscopic anastomosis. The minimal invasive approach (n=16) comprised 5 hybrid procedures and 11 intended TLLTs; 2 TLLTs required open conversion. Baseline characteristics were similar, except for a lower median MELD score in the minimal invasive group (9 vs. 13; p =0.01). Minimal invasive approach yielded longer cold ischemic time (148 vs. 77 min; p <0.001), warm ischemic time (45 vs. 33 min; p =0.03), and total operation time (411 vs. 343 min; p =0.01), with no significant differences in hepatic artery complications (12.5% vs. 4.5%; p =0.18), graft failure (12.5% vs. 4.8%; p =0.20), mortality (6.3% vs. 10.2%; p =0.99), or hospital stay (15.5 vs. 18 d; p =0.10). Within TLLT, 2 cases of hepatic artery thrombosis and 3 biliary complications were managed successfully. Long-term graft and patient survival were comparable to open liver transplantation. TLLT in adults is feasible and safe, achieving outcomes equivalent to open recipient surgery despite longer ischemic and operative times. Careful patient selection and technical refinements-potentially augmented by robotic assistance-may further optimize minimal invasive surgery for the recipient.