Related Experiment Video
Updated: Jan 14, 2026
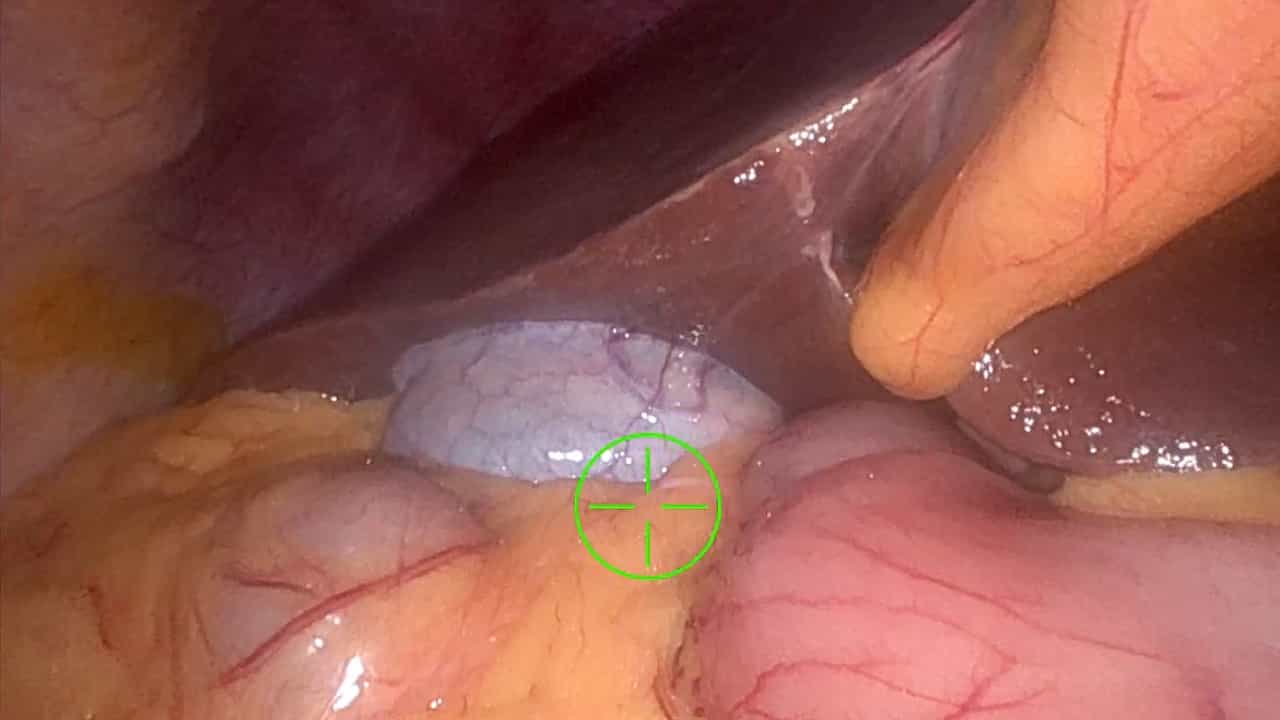
Application of Robot-assisted Pancreaticobiliary Junction Resection in Benign Duodenal Tumors
Published on: December 20, 2024
Identifying occult high-risk features and stratified management strategies following curative resection for ampullary
Xiaoqing Ma1, Chenyang Meng1, Xuejing Shi1
1Pancreas Center, Tianjin Medical University Cancer Institute & Hospital, National Clinical Research Center for Cancer, State Key Laboratory of Druggability Evaluation and Systematic Translational Medicine, Tianjin Key Laboratory of Digestive Cancer, Key Laboratory of Cancer Prevention and Therapy, Tianjin, Tianjin's Clinical Research Center for Cancer, Tianjin 300060, China.

Objective:
The aim of the current study was to identify independent prognostic factors, evaluate differential adjuvant chemotherapy efficacy across clinicopathologic subgroups, and define adjuvant chemotherapy-sensitive populations.
Methods:
A retrospective analysis of 168 AAC patients undergoing curative pancreaticoduodenectomy (2011-2020) was performed. Cases were classified into intestinal (28.0%), pancreatobiliary (30.4%), and mixed subtypes (18.5%) per NCCN (v2.2025) criteria. Independent prognostic factors for AAC patients were identified through uni- and multi-variable Cox proportional hazards modeling and subgroup analyses were stratified by age range, gender, differentiation, T stage, N stage, BVI, TDs, and PNI.
Results:
The pancreatobiliary signature (HR = 2.884, P < 0.001) and BVI (HR = 2.330, P = 0.001) were independent poor prognostic factors. Adjuvant chemotherapy improved overall survival (OS) in the following AAC patients: T3-T4 stage (HR = 0.485, P = 0.050); N1-N2 stage (HR = 0.365, P = 0.008); and TD-positive (HR = 0.401, P = 0.026). The median OS increased from 22.3-51.3 months with adjuvant chemotherapy in TD-positive patients (P = 0.019). TD positivity conferred a worse prognosis in BVI-negative subgroups (OS: HR = 3.840, 95% CI: 2.058-7.166, P < 0.001; and progression-free survival (PFS): HR = 2.950, 95% CI: 1.550-5.617, P = 0.002).
Conclusions:
The pancreatobiliary signature and BVI constitute critical high-risk pathologic features in AAC. TD status identified high-risk cohorts, thus enabling postoperative risk-stratified treatment strategies. In patients negative for pancreatobiliary signature or BVI, TD positivity predicted significantly worse survival.
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: