Related Experiment Video
Updated: Jan 14, 2026
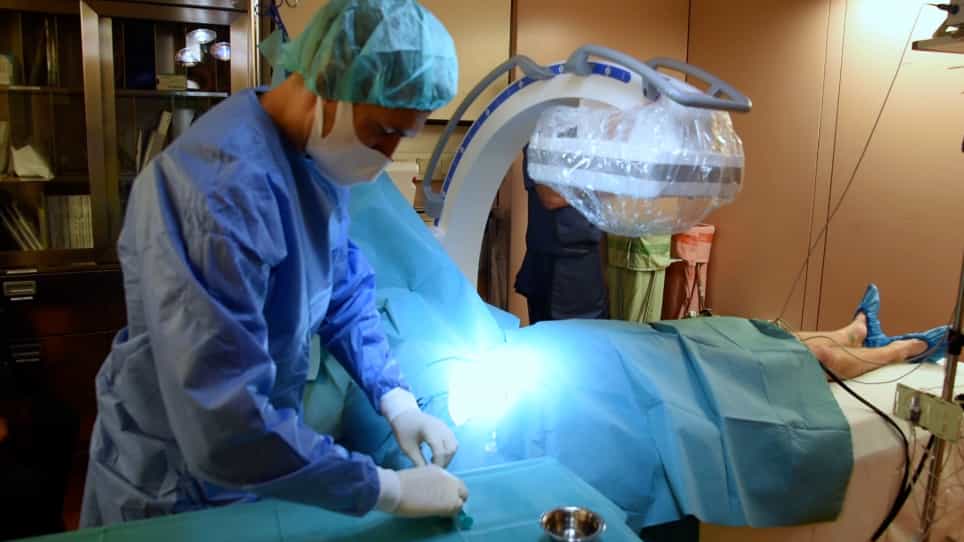
Measurement of the Hepatic Venous Pressure Gradient and Transjugular Liver Biopsy
Published on: June 18, 2020
Comparative Risk of Recurrent Esophageal Variceal Hemorrhage and Other Decompensation Events with Carvedilol Versus
Abdellatif Ismail1, Mohammed Abusuliman2, Mohammad Kloub3
1Division of Gastroenterology and Hepatology, Digestive Disease and Surgery Institute, Cleveland Clinic-Florida, 2950 Cleveland Clinic Blvd., Weston, FL, 33311, USA. IsmailA4@ccf.org.

Background & Aims:
Non-selective beta-blockers (NSBBs) have become a cornerstone treatment to prevent complications of cirrhosis and portal hypertension. Data supporting the use of a specific beta-blocker are scarce. In this retrospective study, we aimed to compare the effectiveness of carvedilol versus propranolol in: 1) preventing recurrent esophageal hemorrhage (EVH) in patients with prior history of EVH 2) reducing the occurrence of further decompensation episodes in these patients including hepatic encephalopathy (HE), ascites, spontaneous bacterial peritonitis (SBP), hepatorenal syndrome (HRS), and hepatocellular carcinoma (HCC), and 3) reducing all-cause mortality.
Approach & Results:
This was a retrospective propensity-matched study using the multi-institutional database TriNetX. We included patients with cirrhosis who had an episode of EVH and were prescribed carvedilol or propranolol between December 2004 and December 2024. The primary outcome was the rate of hospitalization with recurrent EVH within the first 5 years of starting the index NSBB. The secondary outcomes were hospitalization with the principal diagnoses of ascites, SBP, HE, HRS, new diagnosis of HCC, undergoing liver transplant (LT), and all-cause mortality within the observation period of 5 years of NSBB prescription. Kaplan-Meier survival analysis was also performed. Compared to propranolol use, carvedilol use was associated with lower risk of EVH (RR, 0.898, P < 0.001), ascites (RR, 0.757, P < 0.001), SBP (RR, 0.680, P < 0.001), HRS (RR, 0.734, P < 0.001), HCC (RR, 0.701, P < 0.001), undergoing LT (RR, 0.825, P = 0.028) and mortality (RR, 0.640, P < 0.001). No difference in HE rates (RR, 0.899, P = 0.071) was found between the two groups.
Conclusions:
Compared to propranolol, the use of carvedilol in patients with history of cirrhosis and EVH was associated with lower risk of recurrent EVH, further decompensation episodes, undergoing LT, and mortality.
Related Concept Videos
 01:24
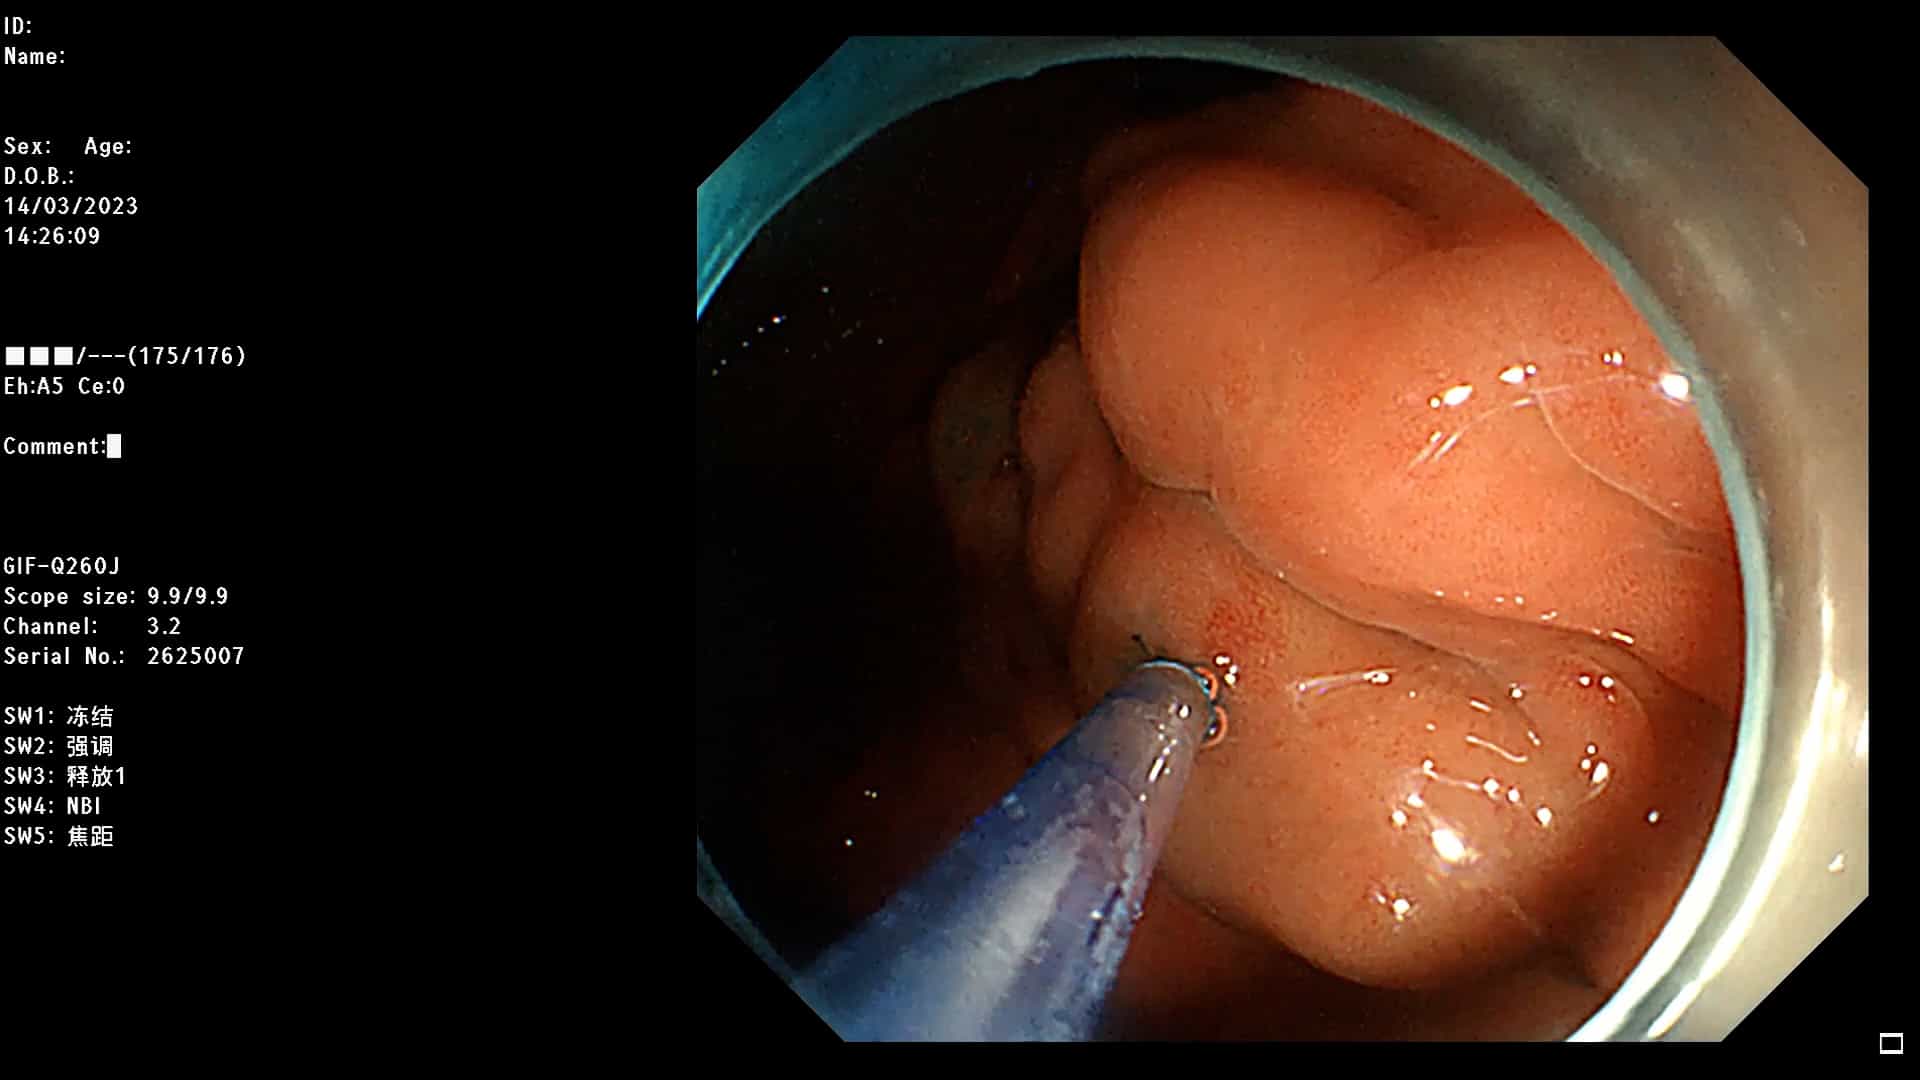
Esophageal Varices-I: Introduction
 01:28
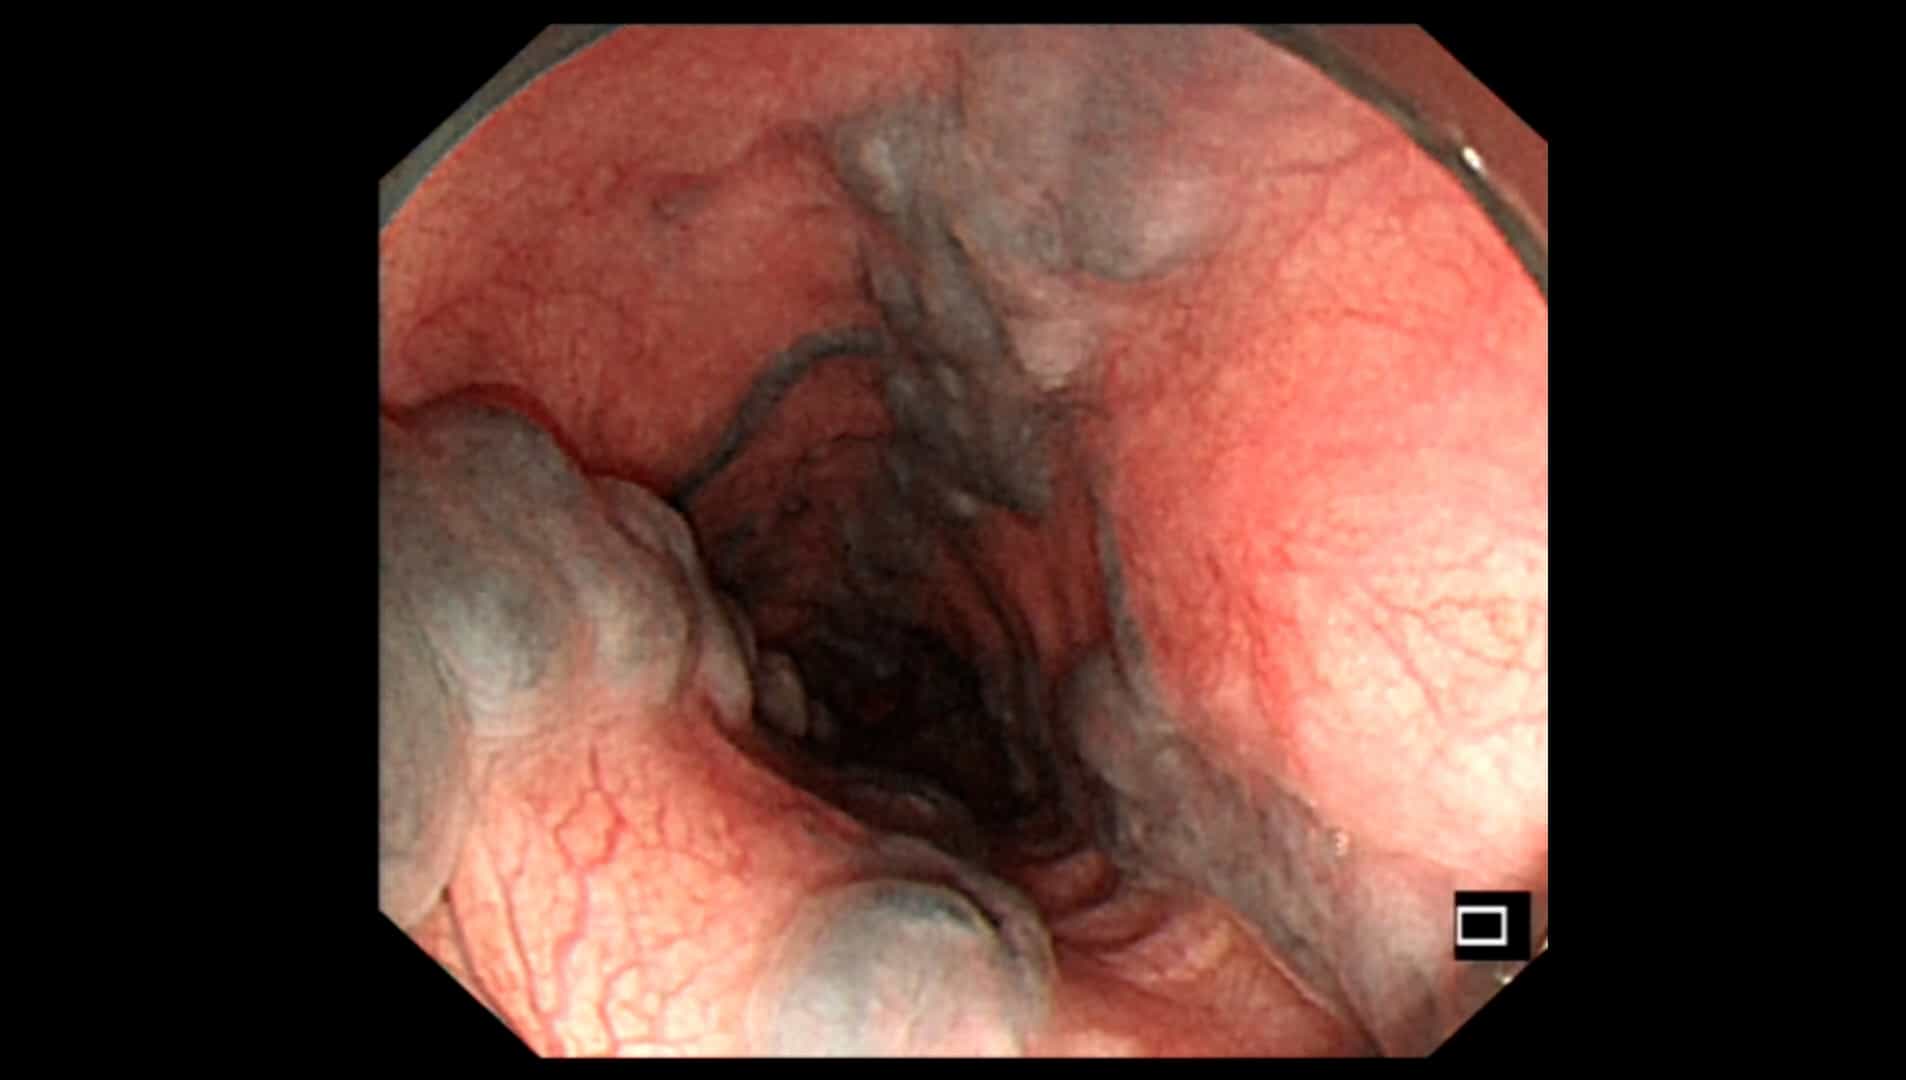
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...