Related Experiment Video
Updated: Jan 14, 2026


Irradiator Commissioning and Dosimetry for Assessment of LQ α and β Parameters, Radiation Dosing Schema, and in vivo Dose Deposition
Published on: March 11, 2021
Compensated biological effective dose in extended radiotherapy course via a time-modified linear quadratic model for
Takuya Wada1, Daisuke Kawahara2, Akito S Koganezawa3
1Radiation Therapy Section, Department of Clinical Practice and Support, Hiroshima University Hospital, Hiroshima 734-8551, Japan; Department of Radiation Oncology, Graduate School of Biomedical and Health Sciences, Hiroshima University, Hiroshima 734-8551, Japan.

Purpose:
Interruptions during radiotherapy, such as holidays or equipment issues, can decrease the biological effective dose (BED) and compromise treatment outcomes. Although the decrease in BED has been previously investigated, a detailed evaluation of three-dimensional (3D) BED distribution and a direct compensation method integrated with treatment planning systems is missing. We aimed to address the decrease in BED due to unexpected interruptions during radiotherapy by developing a workflow to generate deliverable treatment plans based on a modified linear-quadratic (mLQ) model.
Methods:
We analyzed 81 head-and-neck cases treated with volumetric-modulated arc therapy, including 25 single prescription (SRx) and 56 simultaneous integrated boost (SIB) cases. The decrease in BED was calculated using the mLQ model based on treatment duration (TD) from the record & verify system. A base plan was generated using compensating factors (CFs) derived from the mLQ model, and a composite plan was created using existing optimization settings. Compensated and original plans were compared using biological dose-volume histogram (BDVH) parameters and homogeneity index (HI).
Results:
The relative BED was 95.3% ± 2.9% and 93.9% ± 2.2% of the OP with TD from the R&V system. The standard deviation (SD) of the difference in the BED covering 98%, 50%, and 2% of the PTV of OP and CCP was approximately 2%. The difference in the HI was 0.6% ± 1.5%.
Conclusion:
We developed a workflow to generate clinically deliverable plans that compensate for the decrease in BED due to treatment interruptions using the mLQ model. This approach may facilitate rapid compensation planning in clinical radiotherapy settings.


Related Concept Videos
 02:59
Biological Effects of Radiation
 01:12
Two-Compartment Open Model: Extravascular Administration
The absorption exponent (ka) indicates the speed at which the drug...
 01:14
Compartment Models: Single-Compartment Model
 01:21
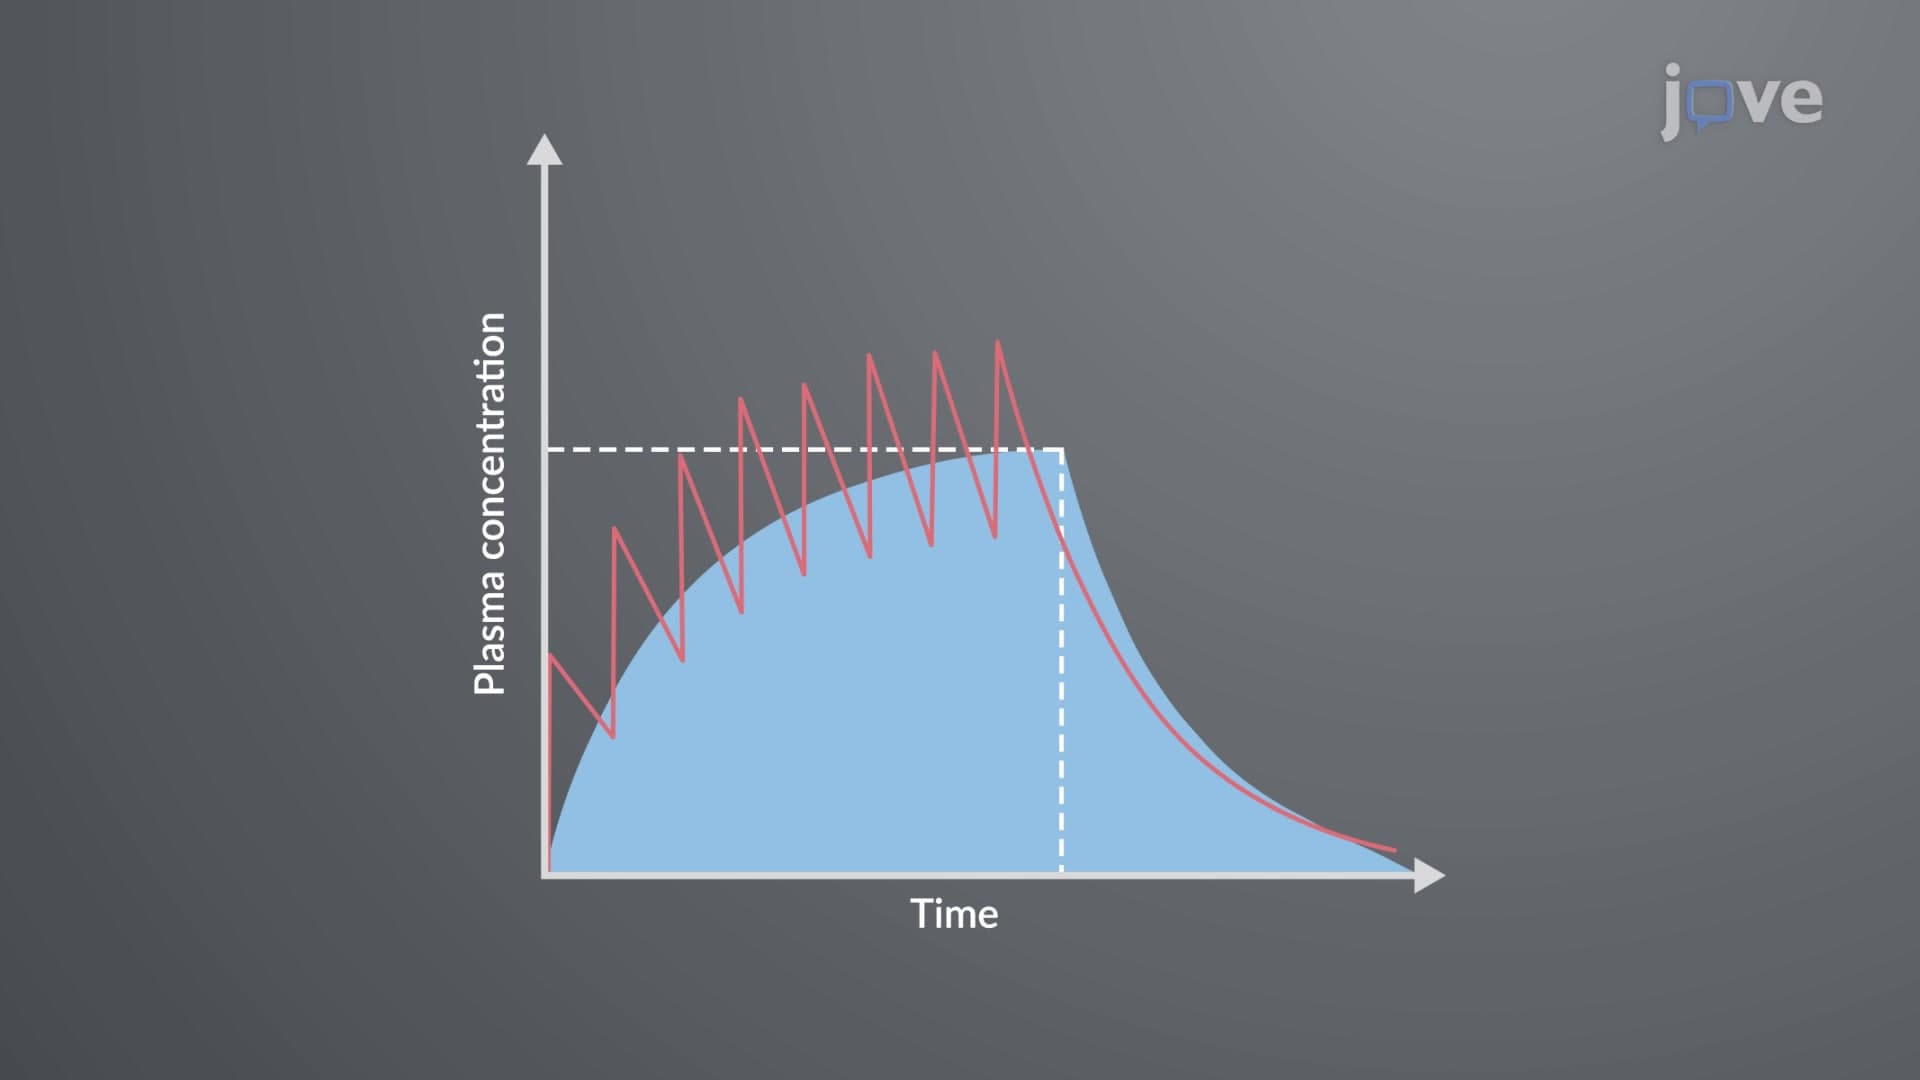
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:06
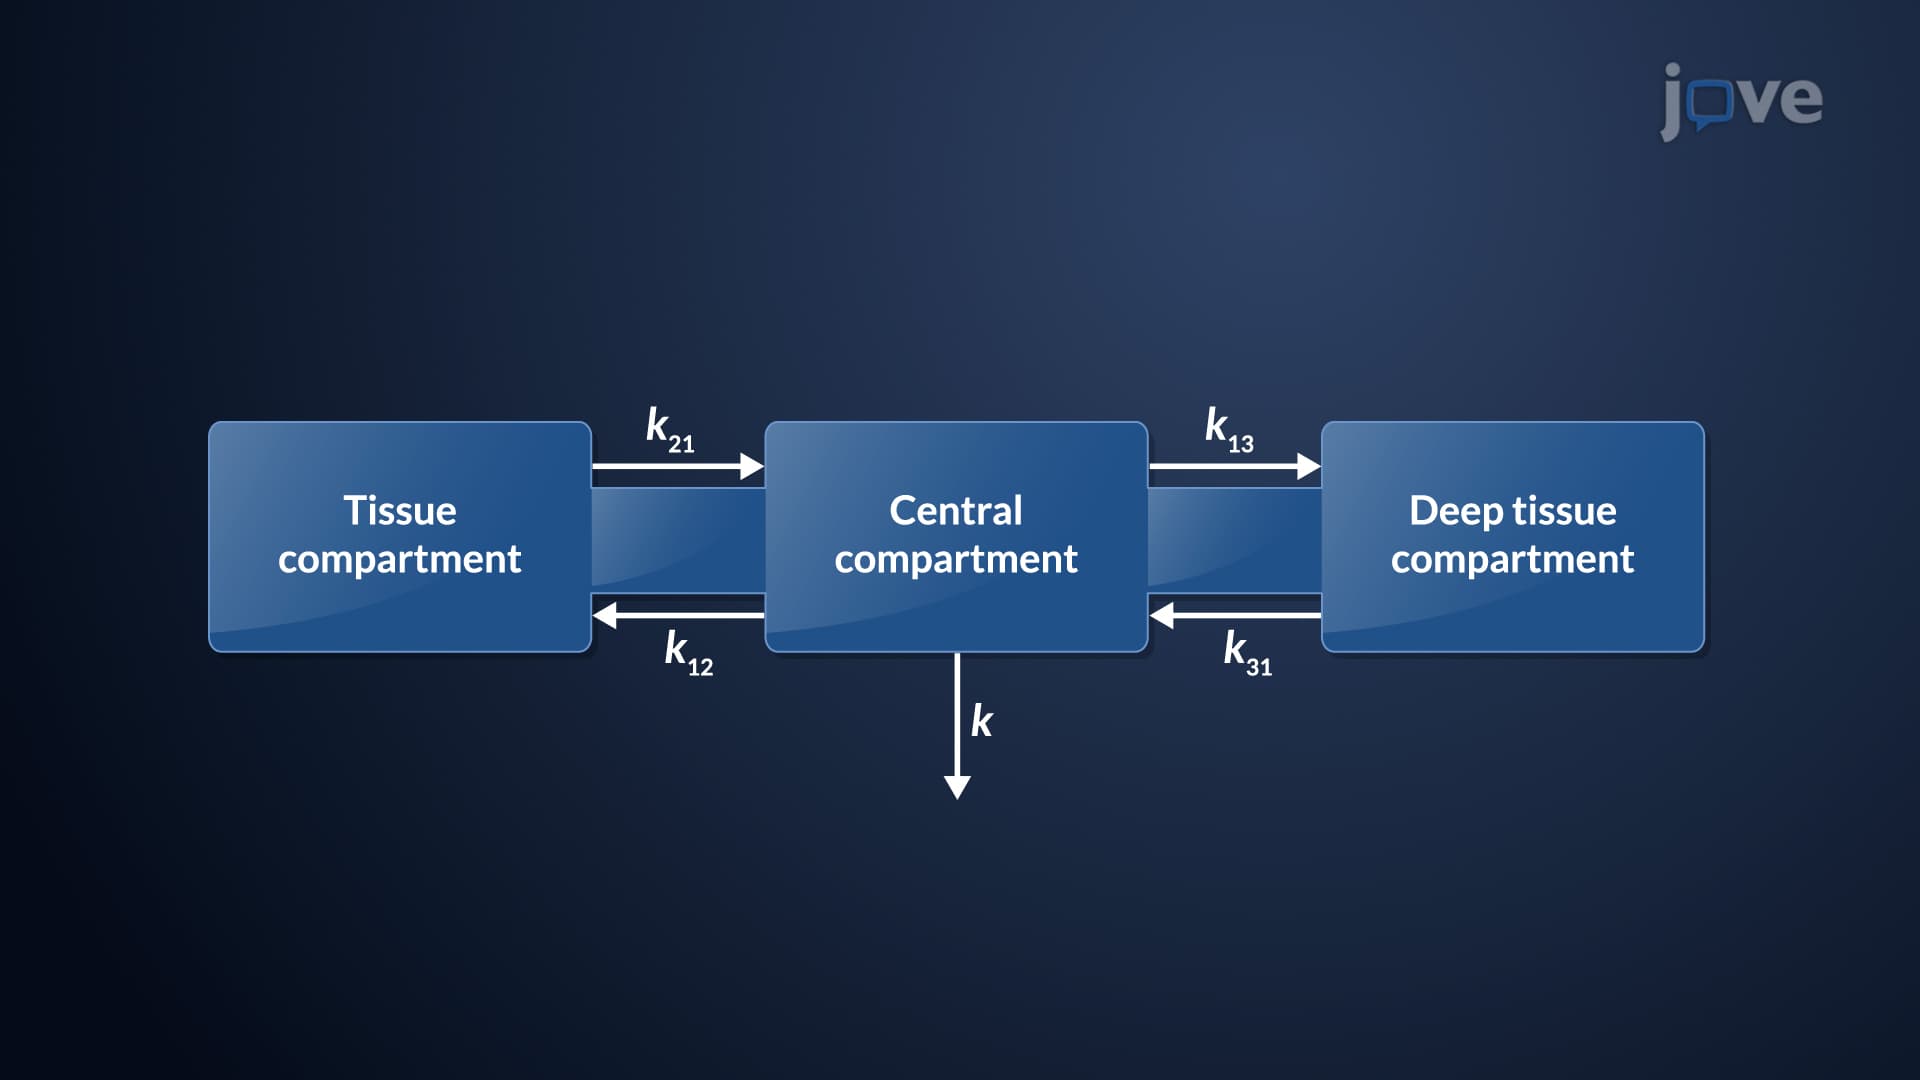
Three-Compartment Open Model
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...