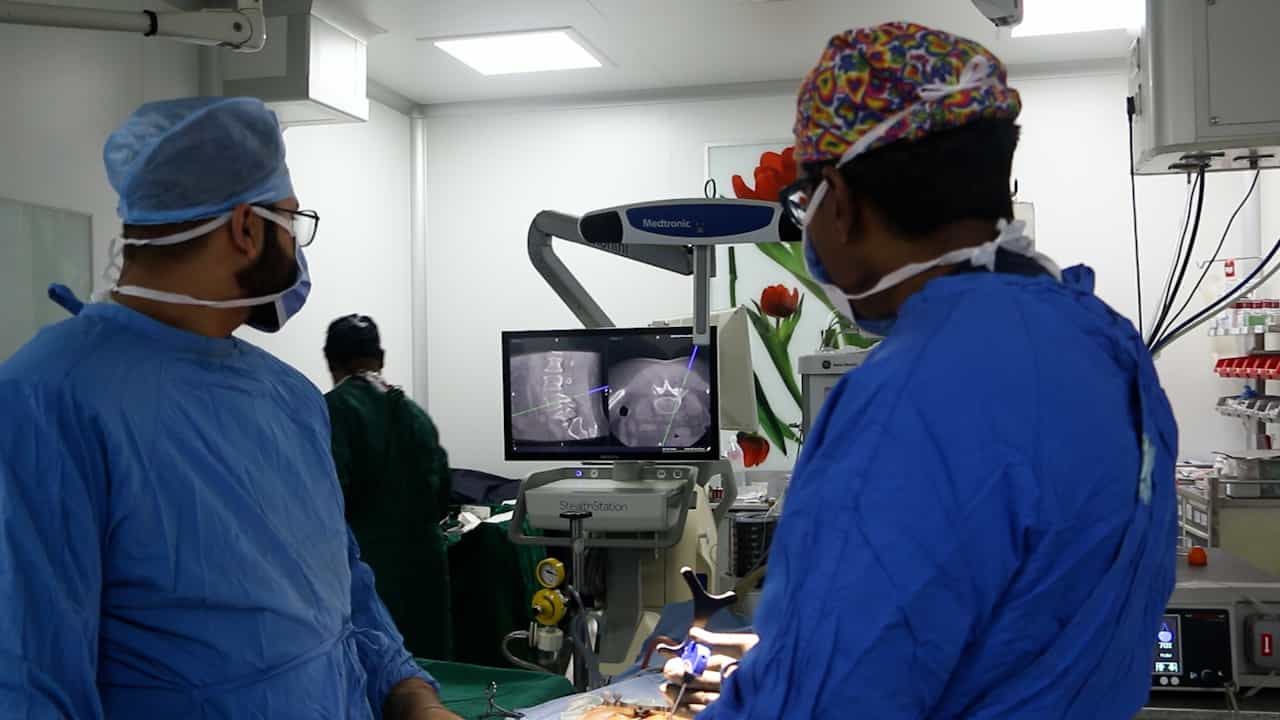
Related Experiment Video
Updated: Jan 14, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Navigation-assisted reduction and fusion for 3 cases of high-grade pediatric dysplastic spondylolisthesis - A
Shailesh Hadgaonkar1, Sameer Nagpal1, Abhinav Ramesh Bhute1
1Department of Spine Surgery, Sancheti Institute for Orthopedics and Rehabilitation, Pune, Maharashtra, India.

Background:
High-grade dysplastic spondylolisthesis in the pediatric population presents significant anatomical and biomechanical challenges due to sacral doming, dysplastic pedicles, and altered spinopelvic parameters. There are high rates of non-union and instrumentation failure, especially without anterior column support. Intraoperative navigation improves accuracy in placing instrumentation and deformity correction.
Methods:
Three pediatric patients with high-grade dysplastic L5-S1 spondylolisthesis underwent reduction and circumferential spinopelvic fixation utilizing intraoperative 3D navigation. Key technical steps included insertion of convergent bi-cortical pedicle screws, sacral dome osteotomy, inter-body cage placement at L5-S1, and controlled reduction maneuvers. One patient's fusion failed and warranted transcorporeal transdiscal screw fixation.
Results:
All 3 patients showed notable correction in deformity (i.e., a mean lumbosacral kyphosis reduction of 20° and slip angle correction of 13.3°). Sagittal balance improved from 6.3 cm to 3.3 cm anterior to the sacral promontory. Two of three patients achieved solid mono-block fusion, while one exhibited loss of reduction following a fall, requiring re-instrumentation and a transcorporeal transdiscal screw fixation.
Conclusion:
Intraoperative navigation facilitates accurate screw placement, safe reduction, and successful fusion for 3 pediatric patients with high-grade pediatric dysplastic spondylolisthesis.