Related Experiment Video
Updated: Jan 14, 2026


A Clinical Trial Assessing the Safety, Efficacy, and Delivery of Olive-Oil-Based Three-Chamber Bags for Parenteral Nutrition
Published on: September 20, 2019
Full exclusively enteral fluids from day 1 versus gradual feeding in preterm infants (FEED1): a open-label,
Shalini Ojha1, Eleanor J Mitchell1, Mark J Johnson2
1School of Medicine, University of Nottingham, Nottingham, UK.

Insights
Starting full milk feeds on day 1 for preterm infants (30-32 weeks gestation) did not shorten hospital stays. This feeding strategy also did not increase risks of necrotising enterocolitis or hypoglycaemia.
Area of Science:
- Neonatal Medicine
- Pediatric Gastroenterology
- Clinical Nutrition
Background:
- Preterm infants typically receive gradual milk feeds alongside intravenous fluids or parenteral nutrition.
- Early milk feeding may reduce hospital stay and infection risk but could increase necrotising enterocolitis risk.
Purpose of the Study:
- To investigate if exclusively enteral fluids (full milk feeds) from day 1, compared to gradual milk feeding, reduces hospital stay in preterm infants (30-32 weeks gestation).
Main Methods:
- An open-label, multicentre, randomised superiority trial involving 2088 infants born between 30+0 and 32+6 weeks gestation.
- Infants were randomly assigned within 3 hours of birth to either full milk feeds (60-80 mL/kg/day) or gradual milk feeding (max 30 mL/kg/day on day 1) with IV support.
- Primary outcome was length of hospital stay; safety outcomes included necrotising enterocolitis and hypoglycaemia. Intention-to-treat analysis was performed.
Main Results:
- No significant difference in the length of hospital stay between the full milk feeds group (32.4 days) and the gradual feeding group (32.1 days).
- Similar rates of survival to discharge, necrotising enterocolitis, and hypoglycaemia events were observed in both groups.
- Serious adverse events were infrequent and similar between the groups, with no reported relation to the trial intervention.
Conclusions:
- Initiating full milk feeds from day 1 in preterm infants (30-32 weeks gestation) does not alter hospital length of stay.
- This early feeding strategy does not increase the risk of necrotising enterocolitis or hypoglycaemia.
- Current feeding guidelines for this preterm infant population can be maintained without increasing adverse outcomes.
Background:
Preterm infants typically receive intravenous fluids or parenteral nutrition while milk feeds are gradually increased. Feeding with milk sooner could reduce length of hospital stay and risk of invasive infections but might increase the risk of necrotising enterocolitis. We aimed to investigate if exclusively enteral fluids (ie, full milk feeds) from day 1 compared with gradual feeding supplemented with intravenous fluids or parenteral nutrition reduces the length of hospital stay in infants born at 30 weeks and 0 days (30+0weeks) to 32+6 weeks of gestation.
Methods:
This open-label, parallel-group, multicentre, randomised, superiority trial recruited mothers of infants born at 30+0 weeks to 32+6 weeks of gestation, in 46 neonatal units in UK hospitals. Infants younger than 3 h were included if they were clinically stable; those with congenital anomalies that make enteral feeding unsafe and who were small for gestational age with reversed end-diastolic flow on umbilical doppler were excluded. Parents and the clinical team could not be masked, but investigators and data analysts were masked until after database lock. The mother was randomly assigned to either full milk feeds (60-80 mL/kg per day) or gradual milk feeding (maximum of 30 mL/kg per day on day 1) with intravenous fluids or parenteral nutrition for their infant within 3 h of birth using a web-based minimisation algorithm with a random element to ensure balance on important prognostic factors. The primary outcome was length of hospital stay; events of hypoglycaemia and necrotising enterocolitis were safety outcomes and analysis was performed by intention-to-treat. This trial was prospectively registered (ISRCTN89654042) and follow-up to 24 months is ongoing.
Findings:
Between Oct 15, 2019, and July 14, 2024, we recruited and randomly assigned 1761 mothers, enrolling 2088 infants (1047 full milk feeds, 1041 gradual feeding). Mean gestational age was 31·7 weeks (SD 0·8), which was the same in both groups, and mean birthweight was 1626·0 g (301·8) in the full milk feeds group and 1617·1 (295·2) in the gradual feeding group. Of 1047 infants in the full milk group, 494 (47·2%) were female and 552 (52·7%) were male and in 1041 infants in the gradual feeding group, 500 (48·0%) were female and 540 (51·9%) were male. Primary outcome data were missing for 18 infants in each group. We found no difference in the length of hospital stay (32·4 days [SD 13·3] in the full milk group vs 32·1 days [13·5] in the gradual feeding group; adjusted difference between means -0·02 days [95% CI -1·07 to 1·03]; p=0·97). Survival to discharge (1030 [99·6%] of 1034 vs 1027 [99·6%] of 1031; -0·004 [95% CI -0·54 to 0·53]), presence of necrotising enterocolitis (4 [0·4%] of 1030 vs 6 [0·6%] of 1027; -0·19 [-0·80 to 0·41]), and mean number of blood glucose tests <2·2 mmol/L (0·6 [SD 1·0] vs 0·5 [0·7]) were similar. Serious adverse events were similar in both groups (eight [0·8%] of 1047 infants in the full milk group vs ten [1·0%] of 1041 infants in the gradual feeding group), all were unrelated to trial intervention.
Interpretation:
In infants born at 30+0 weeks to 32+6 weeks of gestation, full milk feeds from day 1 does not alter length of hospital stay. It does not increase the risk of necrotising enterocolitis or hypoglycaemia.
Funding:
UK National Institute of Health and Care Research.


Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:27
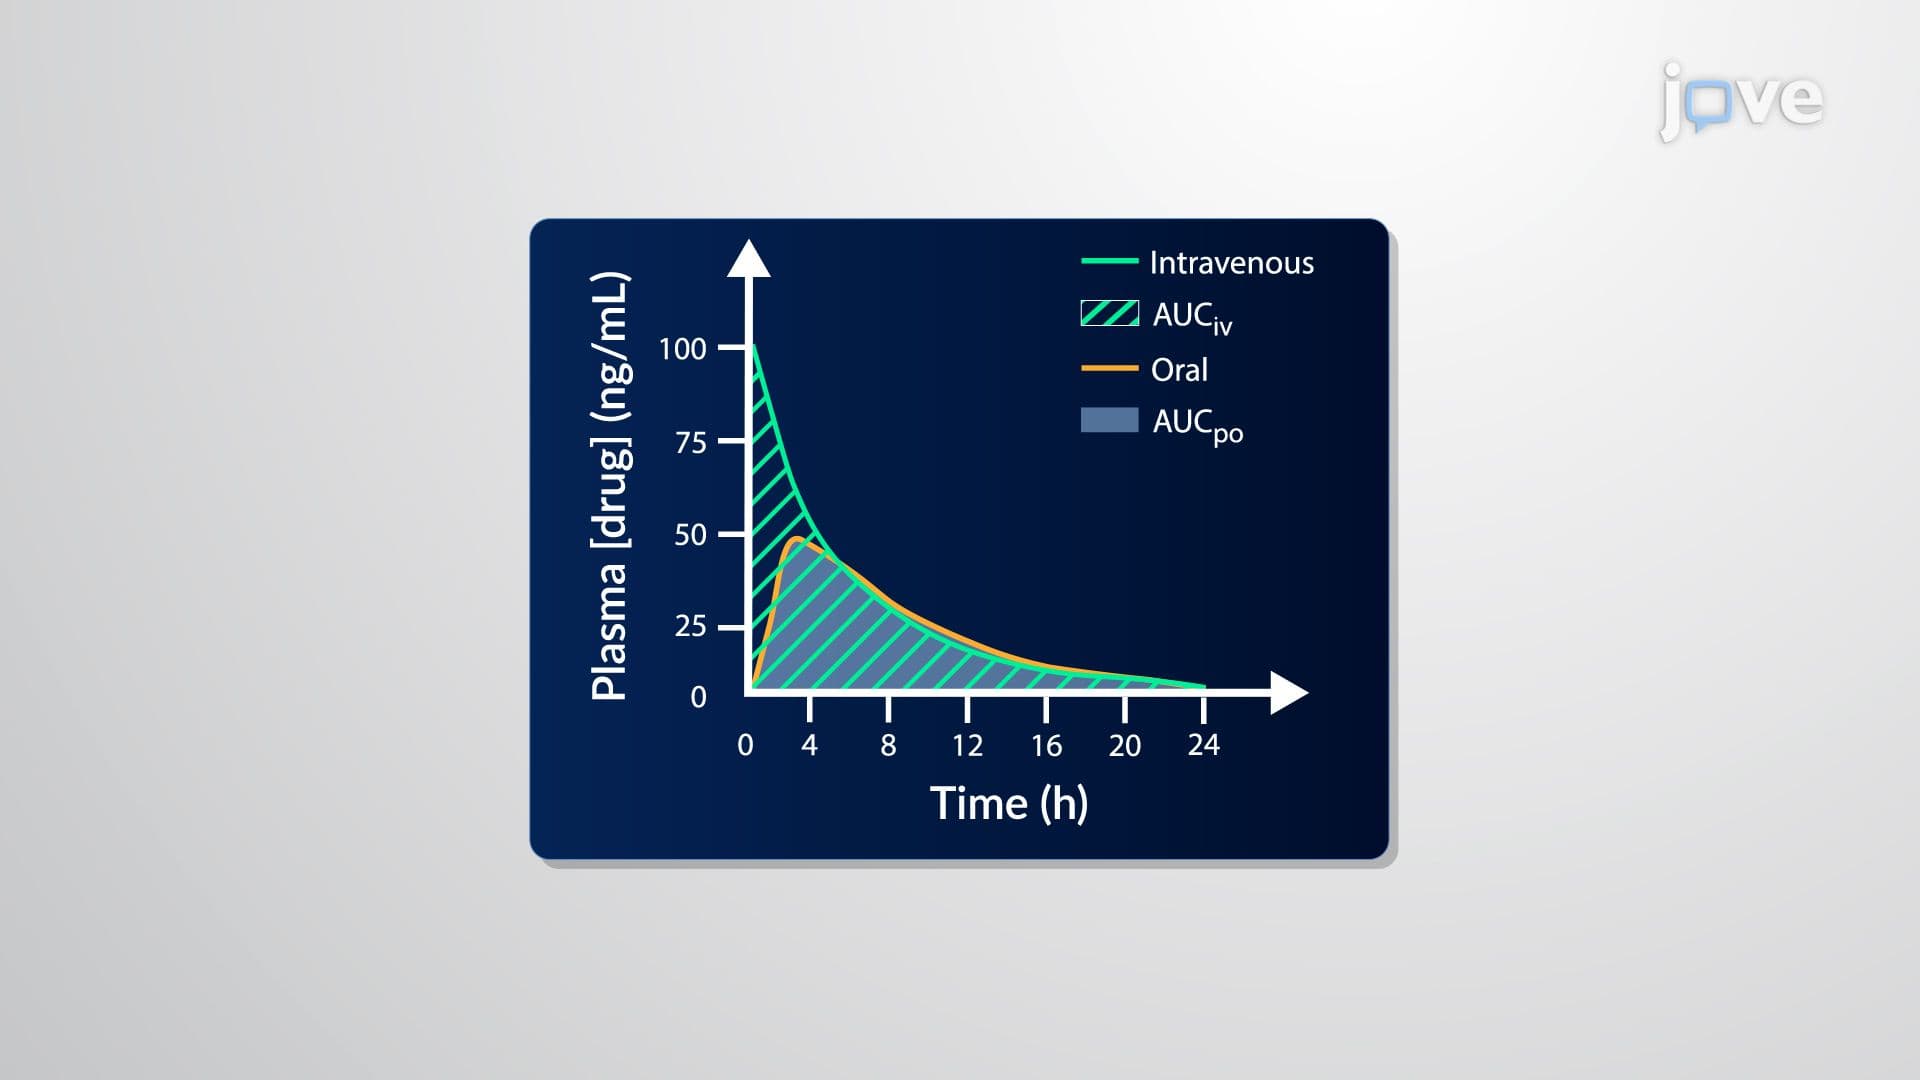
Bioavailability Study Design: Absolute Versus Relative Bioavailability
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies