Related Experiment Video
Updated: Jan 14, 2026
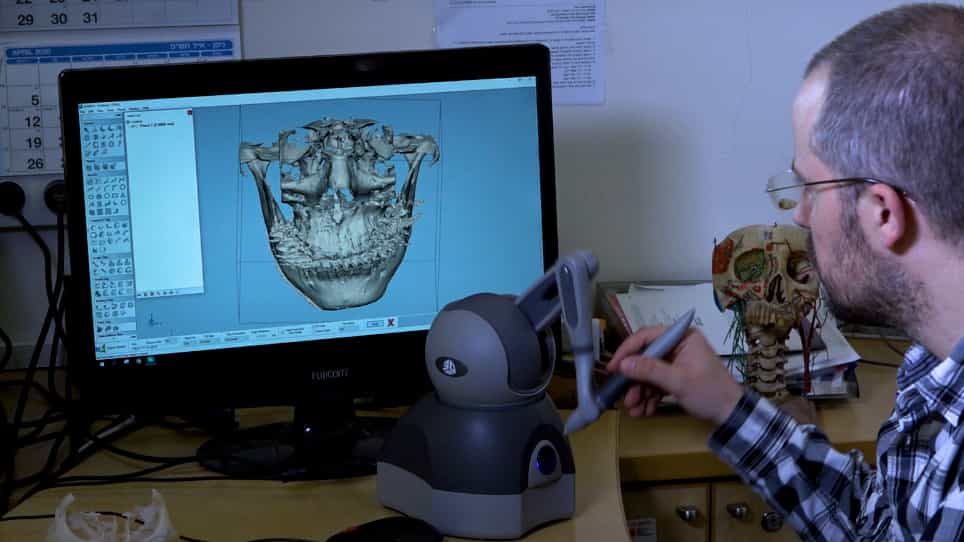
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
The effectiveness of novel 3D printed customized facemask appliance for treatment of class III malocclusion: a
Ghassan B Abdulkareem1,2, Martyn T Cobourne3,4, Mushriq Abid2
1College of Dentistry, Al-Bayan University, Baghdad 10070, Iraq.

Background:
Utilizing 3D facial scans with the aid of digital modeling tools and additive manufacturing is a promising technique for customization of facemask (FM) appliance for correction of Class III malocclusion.
Objectives:
To evaluate the efficacy of a modified 3D-printed maxillary protraction FM compared with a commercially available adjustable FM for the correction of Class III malocclusion due to maxillary retrognathism.
Methods:
This prospective randomized controlled clinical trial enrolled a total of 34 patients aged 7-12 years with skeletal Class III malocclusion requiring maxillary protraction therapy, and were randomly allocated into two groups with a 1:1 ratio. Group 1 was allocated a 3D customized protraction facemask (3DFM), while Group 2 was allocated to a commercially available conventional Petit-type facemask (CFM). The 3DFM was individually designed using a 3D scan of the face obtained using a Revopoint scanner (Revopoint 3D Technologies Inc., China). The FM was modeled using SolidWorks software and manufactured from Acrylonitrile Butadiene Styrene polymer using a Creality K1 Max 3D printer (Creality 3D Technology Co., Ltd., Shenzhen, China). Lateral cephalograms were taken at pretreatment (T1) and post-treatment (T2) after 9 months for analysis.
Results:
Both groups showed significant forward movement of point A (A point to SN perp, P < .000 for both groups) over the period of evaluation, with no significant differences between groups (mean difference (MD) = 0.32 mm, 95% CI: -0.11 to 0.43, P = .240). Both groups showed a significant posterior displacement of SNB (P < .000), with no significant difference between groups (MD = 0.14°, 95% CI: -0.46 to 0.71, P = .671). The ANB angle significantly improved in both groups (P < .000) with no statistically significant differences (MD = 0.21°, 95% CI: -0.51 to 0.96, P = .542). The 3DFM group reported less soft tissue irritation compared with the CFM group. Sleep disturbances were significantly more common in the CFM group compared with the 3DFM group (P = .032, 95% CI: 0.028 to 0.625).
Conclusions:
Both 3DFM and CFM produced significant advancement of the maxilla, as demonstrated by increases in SN-nasion perpendicular and SNA angle. Slightly greater maxillary protraction in the 3DFM group suggests a potential biomechanical advantage although this is unlikely to be clinically significant over the long-term.
Registration:
ClinicalTrials.gov on 12 April 2021 (registration number: NCT06250127).

