Related Experiment Video
Updated: Jan 14, 2026
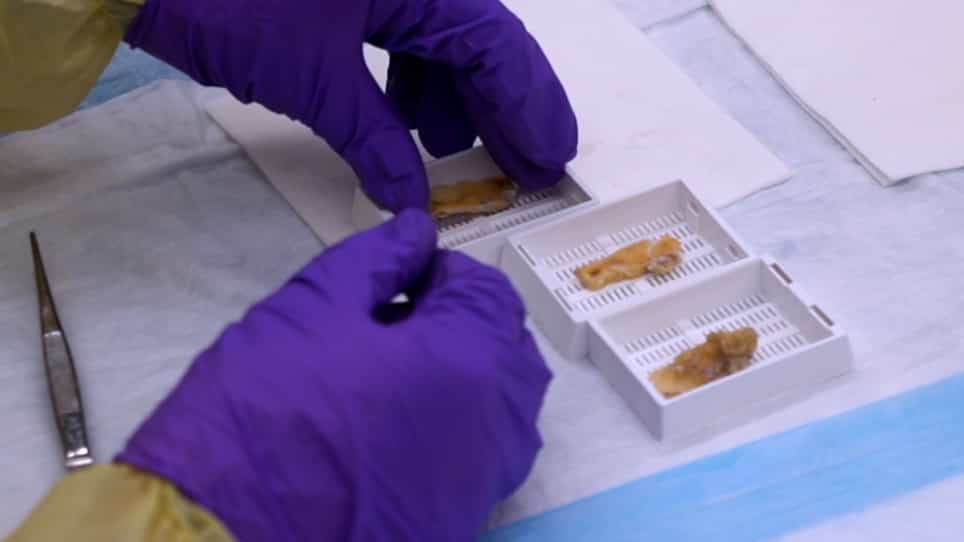

High-Speed Human Temporal Bone Sectioning for the Assessment of COVID-19-Associated Middle Ear Pathology
Published on: May 18, 2022
Hospital and Temporal Variations in Limitations of Care Among Hospitalized Patients with COVID-19: A VIRUS Registry
Nathan Mesfin1, Nitesh Kumar Jain2, Anwar Khedr2
1Division of Pulmonary, Allergy, Critical Care, and Sleep Medicine, Department of Internal Medicine, University of Minnesota, Minneapolis, Minnesota, USA.

Introduction:
Life-support limits (i.e., code status), the first step in the continuum of palliation and end-of-life (EoL) care, stem from decisions made by patients and their providers to align care near the EoL with patients' wishes. The pandemic created health care strain that may have influenced life-support limitation practices among patients with serious COVID-19. In this study, we examine variations in life-support limitations (do-not-resuscitate, DNR; do-not-intubate, DNI) depending on the hospital and period of hospitalization.
Methods:
We included all adults admitted to a hospital in the United States with COVID-19 from January 2020 to December 2021 using the VIRUS registry. Our outcome was any life-support limitation on admission (DNR, DNI, or both) using regression modeling. Main exposures were hospital and period of hospitalization (early vs. late pandemic). Covariates included age, sex, race/ethnicity, comorbidities, and hospitalization diagnoses.
Results:
There were 42,383 patients from 75 hospitals in the US. The median age was 63 (interquartile range: 50-75), 46.5% were female, and 37.5% were non-Hispanic White. The life-support limitation rate was 7.9%, and the palliative care consultation rate was 2.3%. The odds of life-support limitation were 1.86 (95% CI: 1.6-2.1) depending on the hospital, but the period of hospitalization was not associated with odds of life-support limitation. Older age was associated with the greatest increased odds (4.1 per standard deviation ∼ 17.9 years, 95% CI: 3.9-4.4), followed by comorbidities including paralysis (2.4, 95% CI: 1.8-3.0) and dementia (2.3, 95% CI: 2.0-2.6).
Conclusions:
After adjusting for patient-level factors, we report significant inter-hospital but no temporal variation in life-support limitation upon admission with COVID-19. Future studies should investigate specific practices that led to health care resilience to temporal practice variations in life-support limitation during the pandemic.

Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III
 01:30
Pneumonia III: Complications and Assessment
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities