Related Experiment Video
Updated: Jan 14, 2026
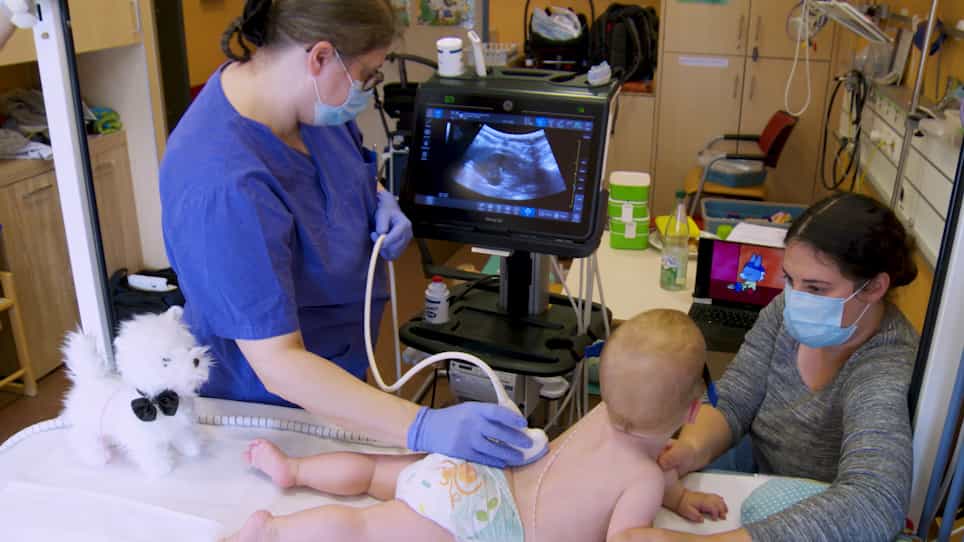
How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Car seat tolerance screen failure in the neonatal intensive care unit: clinical, oxygen saturation and heart rate
Britney He1, Paige Howard1, Sherry Kausch2
1School of Medicine, University of Virginia, Charlottesville, VA, USA.

Insights
Infants failing car seat tolerance screens (CSTS) experienced more desaturations prior. Most premature infants passed a repeat screen shortly after, indicating successful adaptation.
Area of Science:
- Neonatal care
- Pediatric safety
- Cardiorespiratory monitoring
Background:
- American Academy of Pediatrics (AAP) guidelines recommend car seat tolerance screening (CSTS) for high-risk infants before hospital discharge.
- Understanding factors associated with CSTS failure is crucial for refining screening protocols.
Purpose of the Study:
- To compare clinical, oxygen saturation (SpO₂), and heart rate (HR) characteristics between infants who passed and failed their initial CSTS.
- To identify predictors of CSTS failure in a neonatal intensive care unit (NICU) population.
Main Methods:
- Retrospective analysis of 2861 CSTSs from 2523 infants at a single Level IV NICU (2018-2024).
- Comparison of clinical data between infants who passed versus failed their first CSTS.
- Analysis of SpO₂ and HR data, including hypoxemia and bradycardia events, for a subset of infants before and during CSTS.
Main Results:
- First-time CSTS failure occurred in 4.4% of infants, primarily due to oxygen desaturation (85%).
- Infants who failed their initial CSTS exhibited more desaturation events in the 24 hours preceding the screen and experienced deeper, longer desaturations during the test.
- 77% of infants who failed their first CSTS passed a subsequent screen within an average of 1.9 days, with no significant difference in overall length of stay.
Conclusions:
- CSTS failure in high-risk infants is linked to increased pre-screening oxygen desaturations.
- Most infants who initially fail CSTS successfully pass a repeat screen within a short period.
- Continuous physiologic monitoring during CSTS reveals significant differences in desaturation severity between infants who pass and fail.
Background:
The AAP recommends that infants born <37 weeks gestation or with risk factors for positional cardiorespiratory instability undergo a car seat tolerance screen (CSTS) before discharge. Understanding characteristics of CSTS failure may inform screening practices.
Objective:
Compare clinical, oxygen saturation, and heart rate features in infants who failed vs. passed CSTS.
Methods:
We retrospectively reviewed CSTS data from a single level IV NICU (2018-2024). Clinical characteristics of infants who failed vs. passed their first CSTS were compared. For a subset with SpO₂ and HR data, we analyzed hypoxemia and bradycardia events the day before and during CSTS.
Results:
We analyzed 2861 CSTSs from 2523 infants. First CSTS failure occurred in 111 infants (4.4%), most commonly due to oxygen desaturation in 85%. Of 111 infants who failed, 77% passed a second screen a mean of 1.9 days later, and overall length of stay was not significantly different based on CSTS result. Among 1136 infants with physiologic data, those who failed had more desaturation events the day before CSTS, and deeper and longer desaturations during the CSTS.
Conclusions:
CSTS failure was associated with more oxygen desaturations the day prior. Most infants passed a subsequent screen within a short time.
Impact:
This is the largest analysis of NICU car seat tolerance screens (CSTS) using continuous physiologic data. Hypoxemia and bradycardia events occurred in some CSTS designated as "passed" but events were deeper and longer in screens designated as "failed". Infants that failed their first CSTS had lower mean SpO2 and more desaturation events in the 24 hours before the screen.
Related Concept Videos
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:24
Pulse Oximetry
Purpose
Average SpO2 values are greater than 95%. If the readings fall below 90%, it indicates that...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: