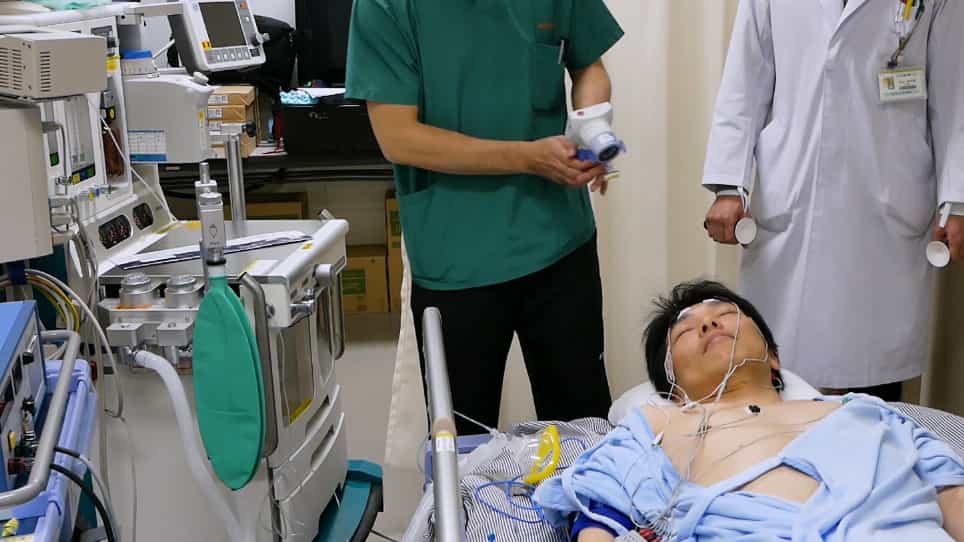
Related Experiment Video
Updated: Jan 13, 2026


Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
The effectiveness of a pupillary dilation reflex as an analgesia indicator: A protocol for a randomised multicentre
Yolanda López de Audícana Jimenez de Aberasturi1,2,3, Ana Vallejo De la Cueva2,3, Naiara Parraza Diez2,4,5
1Vitoria-Gasteiz School of Nursing, University of the Basque Country (UPV/EHU), Jose Atxotegi, 01009 Vitoria-Gasteiz, Spain.

Background:
Effective pain management in sedated, mechanically ventilated patients is essential in intensive care, particularly before invasive procedures. The relationship between pain and biological stress is well established, but its manifestation depends on the patient's clinical state, calling for individualised and effective interventions. The Pupillary Dilation Reflex (PDR) has emerged as a potential objective tool for assessing nociceptive responses and guiding preemptive analgesia (Pre-A) before interventions.
Objective:
To evaluate the PDR as a physiological indicator of pain and its utility in guiding Pre-A before endotracheal aspiration (ETA) in sedated and ventilated ICU patients. We compare the incidence of pain, measured using PDR by video pupillometry, the Behavioural Pain Scale (BPS), and the Pain Indicator Behavioural Scale (ESCID), as well as the proportion of patients receiving Pre-A, between a pupillometry-guided group and a control group receiving standard care.
Methods:
In this multicenter, randomised controlled study, 82 critically ill, sedated patients with an estimated 10% oversampling to compensate for possible attrition will be enrolled and randomised (1:1) into intervention or control groups. In the intervention group, PDR will be measured after a 20 mA stimulus. Patients exhibiting a PDR ≥ 11.5%, a threshold indicating insufficient analgesia, as determined in precursor study (López de Audícana-Jimenez de Aberasturi Y et al., 2024a), will receive Pre-A according to established ICU protocols. The control group will receive Pre-A based on routine clinical assessment. Pain will be assessed using PDR by video pupillometry and behavioural pain scales (BPS and ESCID) after ETA by blinded researchers. Only the pupillometry researcher will be aware of the Pre-A decision. Group differences will be analysed using Chi-square and bivariate statistical methods to explore associations between pain and related clinical variables.
Results:
The primary outcome will be post-intervention pain, assessed by pupillometry as well as BPS and ESCID scale scores. The second outcome will be the proportion of patients requiring Pre-A in the groups.
Conclusion:
Pupillometry-guided analgesia may offer a simple and effective bedside method for individualised pain management in sedated, mechanically ventilated ICU patients, potentially reducing pain-related complications.
Clinical Trial Registration Number:
Phase 2 of the project PUPIPAIN ClinicalTrials.gov Identifier: NCT04078113.